3-Methylglutaconic Aciduria Type 9: Disease-Characteristics Research Report
Scope and evidence standard. This entry describes the TIMM50-associated disorder, not all conditions that produce urinary 3-methylglutaconic acid (3-MGA). Evidence comes primarily from published families, individual case reports, patient-derived cells, and experimental models—not an individual electronic health record or a population registry. The small, selectively ascertained clinical series do not support population prevalence estimates or reliable phenotype percentages. DOI links and publication years are provided below; PMIDs were not verifiable in the retrieved primary texts and are therefore not supplied rather than guessed. Ontology labels below are suggestions for curator verification, not asserted database mappings. (shahrour2017mitochondrialepilepticencephalopathy pages 1-2, crameri2024reducedproteinimport pages 3-4, paz2024biochemicalandneurophysiological pages 1-2)
1. Disease information and identifiers
3-Methylglutaconic aciduria type IX (MGCA9, MGCA type 9) is an early-onset, autosomal-recessive mitochondrial protein-import disorder caused by biallelic TIMM50 variants. Common descriptive names are TIMM50-related mitochondrial disease, TIMM50 deficiency, and mitochondrial epileptic encephalopathy with 3-methylglutaconic aciduria. Seizures, neurodevelopmental impairment, and variably abnormal mitochondrial respiration are more informative than the name alone: a genetically affected person in a 2024 study did not have detectable urinary 3-MGA. The primary article explicitly identifies OMIM/MIM 617698 for MGCA9; TIMM50 is associated with MIM 607381. MONDO:0044724 is the identifier supplied for this entry, but an independent MONDO cross-reference was not verified. A distinct Orphanet disease number, disease-specific ICD-10/ICD-11 code, and MeSH descriptor were not established by the reviewed evidence; do not substitute a general organic-aciduria code for a verified MGCA9-specific identifier. (crameri2024reducedproteinimport pages 1-3, crameri2024reducedproteinimport pages 3-4, tort2019mutationsintimm50 pages 2-3)
2. Etiology, risks, protection, and environment
The demonstrated causal factor is inherited biallelic germline dysfunction of nuclear-encoded TIMM50, which encodes a core component of the mitochondrial inner-membrane TIM23 protein-import system. Reported affected genotypes include homozygous missense variants and compound-heterozygous missense/nonsense variants; segregation in families and restoration of cellular phenotypes by wild-type TIMM50 strengthen causality. Consanguinity increased the likelihood of homozygosity in several reported families, whereas an affected Spanish patient had non-consanguineous parents and compound-heterozygous variants. These observations establish an inheritance mechanism, not a population-specific risk rate. (shahrour2017mitochondrialepilepticencephalopathy pages 1-2, shahrour2017mitochondrialepilepticencephalopathy pages 2-4, tort2019mutationsintimm50 pages 1-2, reyes2018mutationsintimm50 pages 2-3, crameri2024reducedproteinimport pages 4-5)
No independently causal toxin, pathogen, dietary exposure, lifestyle habit, susceptibility locus, protective allele, or validated protective environmental factor was established for MGCA9. The experimentally imposed switch to galactose-dependent oxidative metabolism increased apoptosis in affected fibroblasts despite improving some biochemical measurements; this cell-culture gene–environment interaction is not a recommendation to avoid or consume a particular food. Illness-related deterioration and prevention of metabolic crises have not been quantified specifically for this disorder. (reyes2018mutationsintimm50 pages 3-6, reyes2018mutationsintimm50 pages 2-3)
3. Phenotypes and suggested HPO annotations
The following frequencies are within explicitly defined reports only. The original series comprised four affected individuals from two families. A 2020 comparison of those four plus one new patient records developmental delay, seizure presentations, and urinary 3-MGA in 5/5 selected patients; that is not a disease-wide frequency, especially because a subsequent genetically affected patient lacked 3-MGA. Seizures began at approximately 2–4 months in the five-person comparison. Severity and progression vary: some children achieved walking and seizure control but had severe persistent communication deficits; another patient developed progressive motor disability and wheelchair dependence by age 17. (mir2020completeresolutionof pages 1-2, shahrour2017mitochondrialepilepticencephalopathy pages 2-4, tort2019mutationsintimm50 pages 2-3, crameri2024reducedproteinimport pages 3-4)
Table (click to expand)
| Manifestation and type | Reported pattern; impact on functioning | Suggested HPO concept, subject to ID verification |
|---|---|---|
| Infantile spasms, myoclonic or tonic seizures; clinical symptom | Often early infancy; hypsarrhythmia in children with spasms. Seizures may respond to antiseizure treatment, but neurological disability can persist. | Infantile spasms; seizures; myoclonus; hypsarrhythmia |
| Global developmental delay and intellectual disability; developmental/behavioral | Prominent in original families; later speech and self-care can be severely limited. Hyperactivity or aggression when frightened was described in individual older children, not established as universal. | Global developmental delay; intellectual disability; delayed speech and language development; aggressive behavior |
| Hypotonia, subsequently spasticity/dystonia; clinical signs | Head lag or reduced tone in infancy; progressive spastic tetraparesis and dystonia in the 17-year-old Spanish patient. May impair ambulation and require a wheelchair. | Muscular hypotonia; spastic tetraparesis; dystonia |
| Microcephaly/failure to thrive; physical manifestations | Microcephaly was tabulated in the five selected patients; individual children had marked growth impairment or cachexia. Frequency beyond this selected comparison is unknown. | Microcephaly; failure to thrive |
| Optic atrophy, strabismus, visual impairment; clinical signs | Optic atrophy sometimes emerged years after initially normal fundus examinations. Severe impairment affected one long-term survivor. | Optic atrophy; strabismus; visual impairment |
| Brain atrophy, white-matter loss, bilateral basal-ganglia/brainstem abnormalities; imaging signs | Variable and sometimes progressive. One patient's lesions arose after vigabatrin and substantially resolved, so they must not automatically be attributed to MGCA9. | Cerebral atrophy; abnormality of cerebral white matter; abnormal basal-ganglia MRI signal |
| Cardiomyopathy or cardiac findings; clinical signs | Dilated cardiomyopathy occurred in one patient and improved with digoxin; another had mild left-ventricular hypertrophy and patent ductus arteriosus. These do not establish a cardiac frequency. | Dilated cardiomyopathy; left-ventricular hypertrophy; patent ductus arteriosus |
| Urinary 3-MGA/3-methylglutaric acid, increased lactate, variable OXPHOS deficiency; laboratory abnormalities | The Spanish patient's urine 3-MGA was 53–308 mmol/mol creatinine versus laboratory control <20; blood/CSF lactate were 3/5 mmol/L. Another patient had no detected urinary 3-MGA. Complex-V activity was 54% of control in one muscle sample; normal enzyme tests in another did not exclude disease. | Increased urinary 3-methylglutaconic acid; increased circulating lactate; increased CSF lactate; abnormal mitochondrial respiratory-chain activity |
These are candidate phenotype labels, not validated HPO accession assignments. No disease-specific EQ-5D, SF-36, PROMIS, or per-phenotype quality-of-life scores were identified. Walking, vision, communication, feeding, seizure burden, and reliance on caregivers provide the documented functional outcomes. (mir2020completeresolutionof pages 1-2, shahrour2017mitochondrialepilepticencephalopathy pages 2-4, shahrour2017mitochondrialepilepticencephalopathy pages 4-5, tort2019mutationsintimm50 pages 2-3, crameri2024reducedproteinimport pages 3-4)
4. Genetic and molecular characteristics
Gene: TIMM50, chromosome 19q13.2, gene MIM 607381. Its protein is part of the mitochondrial TIM23 core, alongside TIMM23 and TIMM17A/B. An HGNC numeric ID was not independently verified. Importantly, older reports used a longer TIMM50 isoform: their amino-acid and coding-DNA coordinates should not be combined indiscriminately with current mitochondrial-isoform annotations. The 2024 studies use canonical NM_001001563.5 / NP_001001563.2; transcript-aware reinterpretation is essential in ClinVar and laboratory reports. (mir2020completeresolutionof pages 1-2, crameri2024reducedproteinimport pages 1-3, crameri2024reducedproteinimport pages 3-4, jain2024hotspotsfordiseasecausing pages 4-5)
The table below preserves clinically important source-to-current variant mappings, classification caveats, and the biochemical exception to the disease name. It is a case-report comparison, not a carrier-screening dataset. (jain2024hotspotsfordiseasecausing pages 4-5, crameri2024reducedproteinimport pages 3-4)
Table (click to expand)
| Study | Reported genotype / original notation | NM_001001563.5 normalized notation | Key clinical or functional evidence | Evidence limits |
|---|---|---|---|---|
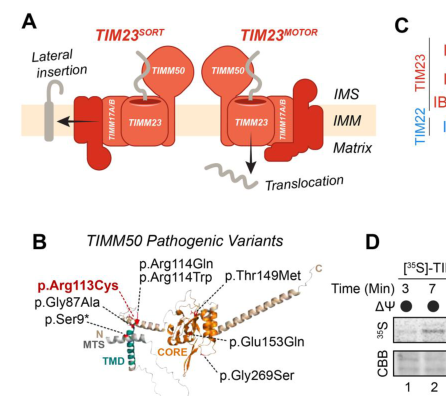
| Shahrour et al., 2017 | Homozygous legacy p.Arg217Trp or p.Thr252Met in four individuals from two consanguineous families | c.340C>T, p.Arg114Trp or c.446C>T, p.Thr149Met | Infantile-onset seizures, severe developmental impairment, 3-methylglutaconic aciduria, mildly elevated lactate, brain atrophy/basal-ganglia abnormalities, and variable complex-V deficiency; one tested patient had complex-V activity at 54% of control (shahrour2017mitochondrialepilepticencephalopathy pages 1-2, shahrour2017mitochondrialepilepticencephalopathy pages 2-4, shahrour2017mitochondrialepilepticencephalopathy pages 4-5, jain2024hotspotsfordiseasecausing pages 4-5) | Only four affected individuals; frequencies are not population estimates. Earlier protein numbering used a longer transcript/isoform and must not be mixed with current canonical numbering. |
| Reyes et al., 2018 | Compound heterozygous c.335C>A, p.Ser112Ter and c.569G>C, p.Gly190Ala on the legacy transcript; one variant inherited from each parent | c.26C>A, p.Ser9Ter and c.260G>C, p.Gly87Ala | Rapidly progressive severe encephalopathy with epilepsy and lactic acidosis; fibroblasts had reduced TIMM50/TIM23 components, impaired TIM23-dependent import, lower membrane potential and respiration, and rescue after wild-type TIMM50 expression. The legacy missense allele was reported once among >200,000 alleles; the nonsense allele was absent from ExAC (reyes2018mutationsintimm50 pages 3-6, reyes2018mutationsintimm50 pages 2-3) | Single proband; historical and current HGVS coordinates are transcript-specific. Functional rescue supports causality but does not establish clinical treatment efficacy. |
| Tort et al., 2019 | Compound heterozygous c.341G>A and c.805G>A | p.Arg114Gln and p.Gly269Ser | One boy had onset at 2.5–3.5 months, West syndrome, Leigh-like lesions, optic atrophy, persistent 3-MGA/3-methylglutaric aciduria, lactic acidosis, neutropenia and dilated cardiomyopathy; at 17 years he had severe encephalopathy, dystonia and wheelchair dependence. Patient cells showed TIMM50 protein loss, abnormal cristae, reduced OXPHOS assembly and respiration; wild-type TIMM50 rescued the cellular defect (tort2019mutationsintimm50 pages 2-3, tort2019mutationsintimm50 pages 1-2, tort2019mutationsintimm50 pages 3-5) | Single-patient case study; complex activities varied by tissue and normalization method, limiting genotype–phenotype generalization. |
| Mir et al., 2020 | Apparent homozygous c.755C>T, p.Thr252Met under the report’s legacy transcript numbering | Corresponding current canonical notation: c.446C>T, p.Thr149Met | One girl developed epileptic spasms at two months with hypsarrhythmia, hypotonia, global developmental delay, microcephaly, marked urinary 3-MGA and lactate of 3 mmol/L. Vigabatrin 150 mg/kg/day produced seizure cessation and EEG normalization; she remained seizure-free after withdrawal at 16 months (mir2020completeresolutionof pages 1-2) | Single case without a comparator. c.755C>T/p.Thr252Met and c.446C>T/p.Thr149Met are transcript-specific representations of the same reported substitution and must not be treated as separate variants. MRI abnormalities were considered vigabatrin-associated and largely resolved. |
| Crameri et al., 2024 | Homozygous NM_001001563.5:c.337C>T, p.Arg113Cys | Same: c.337C>T, p.Arg113Cys | One patient had infantile spasms, developmental delay, optic atrophy and generalized white-matter loss, but urinary 3-MGA was not detected. The allele had gnomAD v4.0 frequency 0.00001053 with no homozygotes. Fibroblasts showed near-complete TIMM50 loss, impaired TIM23 import, combined OXPHOS and cristae defects, and improvement with wild-type TIMM50 re-expression (crameri2024reducedproteinimport pages 3-4, crameri2024reducedproteinimport pages 4-5, crameri2024reducedproteinimport pages 6-9) | Initially classified as a VUS with potential clinical relevance; rarity, phenotype, functional impairment and rescue add pathogenic evidence, but the report concerns one patient. Absence of 3-MGA shows that this biomarker is not obligatory. |
Table: Transcript-aware comparison of key TIMM50-associated MGCA9 reports, emphasizing the very small samples, functional evidence, and the need not to conflate legacy and current HGVS numbering. No PMID or population prevalence is inferred where it was not verified.
Interpretation cautions. The 2024 p.Arg113Cys allele was reported at 0.00001053 in gnomAD v4.0, with zero homozygotes, but was initially designated a variant of uncertain significance with potential clinical relevance; abnormal patient-cell import and wild-type rescue provide functional evidence, not an automatic retrospective ACMG/AMP reclassification. The older Reyes missense allele was observed in one of >200,000 ExAC alleles in that report. The reviewed literature does not establish a complete list of validated modifier genes, pathogenic structural variants, somatic contributions, repeat expansions, or an MGCA9-specific methylation signature. Copy-number analysis may be appropriate for an unresolved recessive genotype, but no recurrent chromosomal syndrome is established. (crameri2024reducedproteinimport pages 3-4, reyes2018mutationsintimm50 pages 2-3, crameri2024reducedproteinimport pages 4-5)
5. Environmental information
MGCA9 is not an infection or toxic-exposure disorder and has no demonstrated zoonotic transmission. Smoking, exercise, alcohol, occupation, pollutants, vaccination, and specific diets have not been shown to cause or protect against the TIMM50 lesion. Galactose-for-glucose substitution is an in vitro energy-stress experiment, not a clinical dietary intervention. No MGCA9-specific infectious trigger or environmental intervention can presently be annotated as established. (shahrour2017mitochondrialepilepticencephalopathy pages 1-2, reyes2018mutationsintimm50 pages 3-6)
6. Mechanism and pathophysiology
Ordered causal chain; evidence level stated at each branch. The accompanying published TIM23 diagram distinguishes lateral insertion (TIM23SORT) from matrix translocation (TIM23MOTOR); it is a pathway schematic, not proof that every substrate is affected. (crameri2024reducedproteinimport media d6c9828b, crameri2024reducedproteinimport pages 1-3)
- Biallelic TIMM50 variants lead to reduced functional TIMM50 protein in examined patient fibroblasts; missense changes can destabilize the protein despite near-normal transcript, whereas a nonsense-containing genotype has reduced transcript consistent with nonsense-mediated decay. Demonstrated in cells; effects vary by allele. (tort2019mutationsintimm50 pages 1-2, crameri2024reducedproteinimport pages 4-5, reyes2018mutationsintimm50 pages 2-3)
- Reduced TIMM50 leads to loss or destabilization of TIM23 core subunits and assembled TIM23, which leads to impaired import of selected nuclear-encoded mitochondrial precursors. Direct import assays showed deficient TIM23-dependent TFAM or NDUFV3 import, with substantially spared TIM22-pathway control substrates; wild-type TIMM50 improved import. Demonstrated in patient-derived cells. (reyes2018mutationsintimm50 pages 3-6, crameri2024reducedproteinimport pages 4-5)
- Import dysfunction branches. Branch A: TIM23SORT-sensitive inner-membrane substrates lead to reduced proteins involved in OXPHOS assembly and membrane organization; comparative 2024 proteomics identifies this pathway as disproportionately affected. Branch B: deficits in selected mitochondrial-ribosomal and respiratory proteins lead to impaired mitochondrial bioenergetics; most assayed mitochondrial inner-membrane and matrix protein levels remain near normal, so this is not complete shutdown of protein import. Demonstrated proteomic changes; assignment of individual clinical features to each substrate remains inferred. (crameri2024reducedproteinimport pages 1-3, crameri2024reducedproteinimport pages 4-5, paz2024biochemicalandneurophysiological pages 4-6, paz2024biochemicalandneurophysiological pages 9-11)
- Altered OXPHOS assembly and cristae-organizing complexes lead to lower oxygen consumption and disturbed inner-membrane architecture. Crameri and colleagues observed reductions in complexes I, II and IV, whereas complex III was comparatively spared in their patient fibroblasts; complex-V dimerization and MICOS-associated organization were disturbed. Complex-V defects in other patients vary with tissue and assay. Demonstrated in cells and some biopsies; which membrane change is upstream of which remains unresolved. (crameri2024reducedproteinimport pages 4-5, crameri2024reducedproteinimport pages 5-6, crameri2024reducedproteinimport pages 6-9, shahrour2017mitochondrialepilepticencephalopathy pages 4-5)
- Reduced respiratory capacity leads to reduced ATP availability and, in one cellular study, increased reactive oxygen species. In TIMM50-knockdown mouse neuronal cultures, approximately 25% lower cellular ATP coincided with a roughly twofold reduction in the fraction of mobile neuritic mitochondria. The interpretation that ATP shortage causes impaired trafficking is plausible but not isolated experimentally. (reyes2018mutationsintimm50 pages 3-6, paz2024biochemicalandneurophysiological pages 9-11, paz2024biochemicalandneurophysiological pages 11-13)
- A parallel neuronal branch links TIMM50 knockdown to reduced KCNA2 and KCNJ10 potassium-channel abundance and increased action-potential firing. The channels fell approximately 2.5-fold in the mouse neuronal system; pharmacological KCNA2 inhibition helped investigate its contribution. The complete chain from TIM23 substrate sorting to channel depletion, and from mouse-neuron excitability to seizures in individual patients, remains inferred. (paz2024biochemicalandneurophysiological pages 13-14, paz2024biochemicalandneurophysiological pages 1-2, paz2024biochemicalandneurophysiological pages 11-13)
- Together, impaired energetic support and altered neuronal excitability plausibly lead to infantile epileptic encephalopathy, developmental and motor deficits, with variable involvement of optic pathways and cardiac muscle. The proximal route to urinary 3-MGA is unresolved: this condition is not established as primary deficiency of leucine-pathway 3-methylglutaconyl-CoA hydratase (AUH), and the biomarker can be absent. Clinical association is demonstrated; complete metabolite-to-phenotype causality is not. (shahrour2017mitochondrialepilepticencephalopathy pages 1-2, crameri2024reducedproteinimport pages 3-4, paz2024biochemicalandneurophysiological pages 1-2, mir2020completeresolutionof pages 1-2)
Suggested mechanism annotations: mitochondrial protein import (GO biological-process concept), mitochondrial inner-membrane protein insertion, mitochondrial respiratory-chain complex assembly, oxidative phosphorylation, ATP biosynthesis, mitochondrial organization and mitochondrial transport along neuronal projections. Suggested GO cellular components are mitochondrial inner membrane, mitochondrial intermembrane space, mitochondrial matrix, and respiratory-chain complex. Candidate cellular concepts include neuron (Cell Ontology CL:0000540, verify before ingestion), fibroblast, cardiomyocyte, skeletal-muscle cell, and retinal ganglion cell; the latter two neural/cardiac assignments reflect affected tissues, not single-cell disease profiling. Candidate chemical annotations are 3-methylglutaconic acid, 3-methylglutaric acid, lactate and ATP; check their ChEBI identifiers against the intended protonation state rather than assigning unverified numbers. (crameri2024reducedproteinimport pages 1-3, paz2024biochemicalandneurophysiological pages 1-2, tort2019mutationsintimm50 pages 2-3)
Omics and limitations: 2024 patient-fibroblast and HEK293 proteomics identified altered OXPHOS, import and cristae-associated proteins; patient-fibroblast and mouse-neuron proteomics identified selected mitochondrial-ribosome and channel changes. In one study 83/127 (~65%) detected inner-membrane proteins and 135/190 (~71%) detected matrix proteins were unchanged in both patient fibroblast samples. Neither study demonstrated an MGCA9-specific clinical transcriptomic, lipidomic, epigenomic, single-cell, spatial-transcriptomic, or multi-omics diagnostic signature. The published experiments are bulk proteomics and cultured-cell physiology, not a CRISPR therapeutic screen. Immune activation, apoptosis, and oxidative stress should not be recorded as universal patient tissue lesions merely because particular cultured-cell conditions produced ROS or apoptosis. (paz2024biochemicalandneurophysiological pages 4-6, reyes2018mutationsintimm50 pages 3-6, crameri2024reducedproteinimport pages 6-9, paz2024biochemicalandneurophysiological pages 13-14)
7. Affected anatomy
The central nervous system is the most consistently described organ system: cerebral cortex and white matter, basal ganglia (including bilateral lentiform nuclei/globus pallidus), brainstem and cerebellar connections can show abnormalities. The optic nerves/visual pathway and heart are affected in selected individuals; skeletal muscle supplied biopsy evidence and later motor abnormalities. Suggested Uberon labels for verification are brain, cerebral white matter, basal ganglion, brainstem, cerebellar peduncle, optic nerve, heart, skeletal muscle, and mitochondrion as the relevant subcellular, rather than organ-level, site. Lesions in published MRIs may be bilateral and symmetric, but unilateral-versus-bilateral status is not a defining diagnostic criterion. Abnormal mitochondrial cristae and swelling were seen in patient cells or muscle. Normal muscle histological architecture or an initially normal eye examination does not exclude disease. (shahrour2017mitochondrialepilepticencephalopathy pages 2-4, shahrour2017mitochondrialepilepticencephalopathy pages 4-5, tort2019mutationsintimm50 pages 2-3, tort2019mutationsintimm50 pages 3-5, crameri2024reducedproteinimport pages 6-9)
8. Temporal development
Reported symptom onset is predominantly early infancy, commonly approximately 2–4 months for seizures. Some cases evolve from apparently unremarkable early development to spasms, developmental delay and later visual or motor deterioration; another survived to 17 years with severe progressive disability. Seizures can remit under treatment without remission of the underlying mitochondrial disease. No validated stages, mean progression rate, critical treatment window specific to TIMM50, spontaneous-remission frequency, or standardized lifelong natural-history curve has been established. Early recognition and treatment of infantile spasms are clinically important but should not be equated with curing MGCA9. (mir2020completeresolutionof pages 1-2, shahrour2017mitochondrialepilepticencephalopathy pages 2-4, tort2019mutationsintimm50 pages 2-3)
9. Inheritance and population
Inheritance is autosomal recessive: homozygous variants segregate in consanguineous families, and a compound-heterozygous genotype was shown to carry one variant from each parent. Under conventional Mendelian assumptions, two carriers have a 25% affected-pregnancy risk; this is a counseling calculation, not an observed disease incidence. The 2024 Paz article described seven distinct mutations among children from ten unrelated families known to its authors at that time; later inclusion criteria and variant remapping may change a count. Those numbers are published-case counts, not carrier frequency or prevalence. There are no defensible disease-specific incidence or prevalence figures per 100,000, sex ratio, founder-allele estimate, quantified penetrance, or established anticipation/germline-mosaicism rates from these sources. Affected individuals have been described in several geographic/ancestral settings, but no ethnic group can be assigned a population risk from the case reports alone. Expressivity is demonstrably variable; penetrance cannot be computed. (paz2024biochemicalandneurophysiological pages 2-4, shahrour2017mitochondrialepilepticencephalopathy pages 1-2, reyes2018mutationsintimm50 pages 2-3, tort2019mutationsintimm50 pages 2-3, crameri2024reducedproteinimport pages 3-4)
10. Diagnostics and differential diagnosis
A practical clinical workflow is: (1) assess infantile seizures, developmental course, eye and cardiac findings; (2) obtain urine organic-acid profiling for 3-MGA and 3-methylglutaric acid, plasma/CSF lactate when clinically indicated, and general metabolic tests; (3) evaluate EEG, brain MRI, ophthalmology and ECG/echocardiography as indicated; (4) perform a mitochondrial-disease/3-MGA multigene panel including TIMM50 or trio whole-exome/genome sequencing, with segregation testing; and (5) use fibroblast protein/import/OXPHOS studies, when available, to investigate uncertain genotypes. Sequencing confirms a molecular diagnosis; abnormal urine is supportive but neither pathognomonic nor obligatory. A pathogenic TIMM50 genotype can occur when urine 3-MGA is undetected, and muscle respiratory-chain enzyme activities can appear normal even when other measures are abnormal. (shahrour2017mitochondrialepilepticencephalopathy pages 1-2, shahrour2017mitochondrialepilepticencephalopathy pages 4-5, tort2019mutationsintimm50 pages 2-3, crameri2024reducedproteinimport pages 3-4, crameri2024reducedproteinimport pages 4-5)
Tests and caveats. EEG can establish spasms/hypsarrhythmia; MRI may show atrophy or Leigh-like bilateral abnormalities. Interpret new basal-ganglia/brainstem lesions after vigabatrin cautiously: the Mir patient’s lesions were considered drug-associated and near-resolved on follow-up, not proof of progressive primary brain injury. Muscle biopsy can show mitochondrial lipid/cristae abnormalities or reduced respiratory-complex activity after normalization to citrate synthase; it is not obligatory when genetics is definitive. In cells, TIM23-versus-TIM22 substrate-import assays and wild-type complementation are research-level functional confirmation, not routine validated screening assays. No disease-specific diagnostic cutoff, validated GDF15/FGF21 threshold, LOINC-based test algorithm, RNA-seq classifier, liquid-biopsy test, or formal society diagnostic criteria were verified. (mir2020completeresolutionof pages 1-2, tort2019mutationsintimm50 pages 2-3, tort2019mutationsintimm50 pages 3-5, reyes2018mutationsintimm50 pages 3-6)
Differential: other genetic conditions with 3-MGA and mitochondrial disease, including AUH-related primary 3-MGA metabolism defects and TAZ, DNAJC19, TMEM70, SERAC1, AGK, CLPB and other mitochondrial-membrane or respiratory disorders. Urinary 3-MGA alone cannot distinguish them; sequencing the appropriate disease-gene set is central. A normal result on standard mtDNA testing does not rule out this nuclear-gene condition. Chromosomal microarray, karyotyping, FISH and repeat-expansion testing are not established specific first-line tests for MGCA9, though broader evaluation may be appropriate for unresolved cases. No validated MGCA9-specific routine newborn-screening marker or population program was established in the retrieved evidence. (tort2019mutationsintimm50 pages 2-3, crameri2024reducedproteinimport pages 1-3, crameri2024reducedproteinimport pages 3-4)
11. Outcome and prognosis
The principal documented morbidity is persistent neurodevelopmental impairment, epilepsy, visual dysfunction and, in some patients, progressive motor disability and cardiomyopathy. Clinical course ranges from ambulatory childhood despite marked intellectual disability to wheelchair dependence at 17 years; reports of rapidly progressive severe encephalopathy also exist. Consequently no credible five-/ten-year survival rate, median life expectancy, treatment-adjusted mortality rate, validated prognostic score, or quantitative quality-of-life measure can be reported for MGCA9. Seizure control is not evidence that mitochondrial protein import has normalized. Genotype, respiratory-complex activities and urinary 3-MGA are not validated prognostic biomarkers. (shahrour2017mitochondrialepilepticencephalopathy pages 2-4, tort2019mutationsintimm50 pages 2-3, reyes2018mutationsintimm50 pages 3-6, mir2020completeresolutionof pages 1-2, crameri2024reducedproteinimport pages 3-4)
12. Treatment and current implementation
There is no demonstrated disease-modifying treatment or approved TIMM50-specific drug, gene therapy, cell therapy, RNA therapy or immunotherapy in the reviewed literature. Actual reported care is supportive and symptom-directed:
- Epileptic spasms: one girl with homozygous reported p.Thr252Met had cessation of spasms and EEG normalization after vigabatrin titrated to 150 mg/kg/day; treatment was withdrawn at 16 months, with seizure freedom reported thereafter. Original-family patients received ACTH, followed in some by vigabatrin, valproate or topiramate; other individuals received valproate and lamotrigine. These are individual treatment histories, not MGCA9-specific response rates or a comparative efficacy trial. Suggested NCIT concepts to verify: Vigabatrin, Adrenocorticotropic Hormone, Valproic Acid, Topiramate, Lamotrigine, Antiepileptic Therapy. (mir2020completeresolutionof pages 1-2, shahrour2017mitochondrialepilepticencephalopathy pages 2-4, shahrour2017mitochondrialepilepticencephalopathy pages 4-5)
- Cardiac care: digoxin was associated with improvement in one patient's dilated cardiomyopathy. Echocardiographic surveillance and specialist-directed treatment are reasonable clinical extrapolations from reported heart disease, not proven MGCA9-specific protocols. Suggested NCIT concepts to verify: Digoxin, Echocardiography. (tort2019mutationsintimm50 pages 2-3)
- Functional support: developmental, physical, occupational, speech/feeding, vision and nutritional assessment follows from documented disability and growth failure, but no MGCA9-specific trial has established its magnitude of benefit. Suggested NCIT concepts to verify: Physical Therapy, Occupational Therapy, Speech Therapy, Nutritional Support, Genetic Counseling. (tort2019mutationsintimm50 pages 2-3, shahrour2017mitochondrialepilepticencephalopathy pages 2-4, mir2020completeresolutionof pages 1-2)
Safety and experimental status: MRI findings considered transiently vigabatrin-associated were reported in one treated child; this does not provide an MGCA9-specific adverse-event rate. Wild-type TIMM50 rescued defects in cultured cells only and should not be described as an available patient gene therapy. Searches of the accessible clinical-trial records did not identify a clearly MGCA9/TIMM50-specific interventional NCT study; absence from those search results does not prove that none can exist in every registry. No validated pharmacogenomic dosing rule or combination-therapy algorithm is established. (mir2020completeresolutionof pages 1-2, crameri2024reducedproteinimport pages 4-5, crameri2024reducedproteinimport pages 9-11)
13. Prevention and counseling
Because pathogenic TIMM50 alleles are inherited, primary prevention by avoiding infection, changing diet, vaccination against MGCA9, or toxin removal is not established. Genetic counseling, reproductive carrier testing in an affected family, variant-specific prenatal testing or preimplantation genetic testing when familial pathogenic variants are known, and cascade testing of relatives are applicable Mendelian options; their clinical implementation requires local laboratory confirmation and counseling, especially for VUSs. Secondary prevention is early recognition of infantile spasms and associated organ involvement, not proven population newborn screening for MGCA9. Tertiary prevention addresses seizures, nutrition, mobility, vision and cardiac complications. Ordinary recommended immunizations may remain important as general health care; there is no MGCA9-specific vaccine or prophylactic medication demonstrated here. (shahrour2017mitochondrialepilepticencephalopathy pages 1-2, reyes2018mutationsintimm50 pages 2-3, crameri2024reducedproteinimport pages 3-4, mir2020completeresolutionof pages 1-2)
14. Natural disease in other species
The disorder defined by OMIM 617698 is documented in humans (Homo sapiens, NCBI Taxon 9606). Orthologous Tim50 proteins occur in yeast and mouse and enable comparative experiments, but an independently diagnosed, naturally occurring MGCA9 syndrome in companion animals, livestock or wildlife—and hence a breed/VBO identifier—was not established by the sources assessed. There is no infectious agent and no zoonotic route. Ortholog-specific NCBI Gene IDs should be checked directly rather than inferred from a human symbol; the Shahrour yeast study explicitly gives Saccharomyces cerevisiae Tim50 Gene ID 856042. The structural differences between yeast and human proteins limit simple cross-species variant interpretation. (shahrour2017mitochondrialepilepticencephalopathy pages 4-5, shahrour2017mitochondrialepilepticencephalopathy pages 5-6, jain2024hotspotsfordiseasecausing pages 4-5)
15. Model organisms and experimental systems
- Patient-derived human skin fibroblasts, cellular model: reduced TIMM50/TIM23, impaired import and respiration, variable OXPHOS assembly, abnormal cristae; wild-type TIMM50 re-expression improved several defects. These cells support variant causality but cannot reproduce human cognition, seizures or survival. (crameri2024reducedproteinimport pages 4-5, reyes2018mutationsintimm50 pages 3-6, crameri2024reducedproteinimport pages 6-9)
- Human HEK293/HEK293T CRISPR-perturbed cell lines: partial/mutant TIMM50 disruption recapitulated TIM23 and respiratory defects, with improvement on gene re-expression. A 2024 group could not obtain a complete knockout in its HEK293 system, an important essential-gene/model limitation. Cell-line rescue is a research application, not established treatment. (crameri2024reducedproteinimport pages 6-9, crameri2024reducedproteinimport pages 9-11, tort2019mutationsintimm50 pages 1-2)
- Primary mouse cortical-neuron cultures, induced knockdown: about 80% reduction of TIMM50 with the selected shRNA; reduced respiration and ATP, impaired neuritic mitochondrial movement, and increased electrical excitability associated with lower KCNA2/KCNJ10. This is not a naturally affected mouse and not evidence that a whole-body engineered mouse reproduces all human features. Candidate cell type: neuron, CL:0000540 (verify). (paz2024biochemicalandneurophysiological pages 4-6, paz2024biochemicalandneurophysiological pages 11-13, paz2024biochemicalandneurophysiological pages 13-14)
- Yeast (Saccharomyces cerevisiae, NCBI Taxon 4932), allele-model experiment: the equivalent of human legacy p.Arg217Trp was introduced as yeast Tim50 p.Arg159Trp. Unexpectedly, tested yeast grew normally on glucose/glycerol and showed no clear Hsp60-import defect. Thus a negative yeast assay did not overturn the human genetic/clinical evidence; human and yeast Tim50 domains differ. (shahrour2017mitochondrialepilepticencephalopathy pages 5-6, jain2024hotspotsfordiseasecausing pages 4-5)
No validated whole-animal Timm50 knock-in that recapitulates the complete MGCA9 phenotype, breed-specific spontaneous model, or disease-specific iPSC/organoid resource was verified. The model's evidentiary category should always be stored separately from the corresponding human clinical observation. (paz2024biochemicalandneurophysiological pages 1-2, shahrour2017mitochondrialepilepticencephalopathy pages 5-6)
Selected primary sources and exact abstract evidence
- Shahrour et al., Clinical Genetics, 2017, https://doi.org/10.1111/cge.12855. Abstract: “We now report on four patients from two unrelated families who presented with severe intellectual disability and seizure disorder, accompanied by slightly elevated lactate level, 3-methylglutaconic aciduria and variable deficiency of mitochondrial complex V.” Human familial clinical/genetic evidence. (shahrour2017mitochondrialepilepticencephalopathy pages 1-2)
- Reyes et al., EMBO Molecular Medicine, published online 6 September 2018, https://doi.org/10.15252/emmm.201708698. Abstract: “Patient fibroblasts presented low levels of TIMM50 and other components of the TIM23 complex, lower mitochondrial membrane potential, and impaired TIM23-dependent protein import.” One affected child plus cellular functional experiments. (reyes2018mutationsintimm50 pages 3-6)
- Tort et al., Human Mutation, 2019, https://doi.org/10.1002/humu.23779. Abstract: “TIMM50 protein was severely reduced in the patient fibroblasts, regardless of the normal mRNA levels, suggesting that the mutated residues might be important for TIMM50 protein stability.” Single-patient clinical and cell-rescue evidence. (tort2019mutationsintimm50 pages 1-2)
- Mir et al., Clinical Genetics, 2020, https://doi.org/10.1111/cge.13763. Authors' letter: “We describe a very rare case of 3-MGA caused by a mutation in TIMM50 gene presenting with ES who had complete resolution of ES and hypsarrhythmia with vigabatrin (VGB).” Single-patient treatment observation; not a controlled efficacy estimate. (mir2020completeresolutionof pages 1-2)
- Crameri et al., Molecular and Cellular Biology, 2024, https://doi.org/10.1080/10985549.2024.2353652. Abstract: “laterally released substrates imported via the TIM23SORT complex pathway are most sensitive to loss of TIMM50.” One new clinical case, human-cell/HEK293 proteomics and import experiments. The same report explicitly records absent urinary 3-MGA in its patient. (crameri2024reducedproteinimport pages 1-3, crameri2024reducedproteinimport pages 3-4)
- Paz et al., eLife, version of record 16 December 2024, https://doi.org/10.7554/eLife.99914. Abstract: “increased electrical activity was observed in TIMM50 deficient mice neuronal cells, which correlated with reduced levels of KCNJ10 and KCNA2 plasma membrane potassium channels.” Patient-fibroblast and cultured mouse-neuron evidence; causal relevance of specific channel changes to human epilepsy is not yet established. (paz2024biochemicalandneurophysiological pages 1-2, paz2024biochemicalandneurophysiological pages 13-14)
Knowledge-base priority: record the TIMM50–MGCA9 causal association and transcript-aware alleles as strong human genetic evidence; record patient-specific manifestations, treatment responses and model-derived downstream mechanisms with their actual evidence types and uncertainty; leave unverified prevalence, HPO/GO/UBERON/ChEBI/NCIT accession numbers, PMIDs and unsupported disease-specific therapies unpopulated pending direct database validation. (shahrour2017mitochondrialepilepticencephalopathy pages 1-2, crameri2024reducedproteinimport pages 3-4, paz2024biochemicalandneurophysiological pages 1-2)
References
-
(shahrour2017mitochondrialepilepticencephalopathy pages 1-2): M.A. Shahrour, O. Staretz‐Chacham, D. Dayan, J. Stephen, A. Weech, N. Damseh, H. Pri Chen, S. Edvardson, S. Mazaheri, A. Saada, E. Hershkovitz, A. Shaag, M. Huizing, B. Abu‐Libdeh, W.A Gahl, A. Azem, Y. Anikster, T. Vilboux, O. Elpeleg, and M.C. Malicdan. Mitochondrial epileptic encephalopathy, 3‐methylglutaconic aciduria and variable complex v deficiency associated with timm50 mutations. Clinical Genetics, 91:690-696, May 2017. URL: https://doi.org/10.1111/cge.12855, doi:10.1111/cge.12855. This article has 49 citations and is from a peer-reviewed journal.
-
(crameri2024reducedproteinimport pages 3-4): Jordan J. Crameri, Catherine S. Palmer, Tegan Stait, Thomas D. Jackson, Matthew Lynch, Adriane Sinclair, Leah E. Frajman, Alison G. Compton, David Coman, David R. Thorburn, Ann E. Frazier, and Diana Stojanovski. Reduced protein import via tim23 sort drives disease pathology in timm50-associated mitochondrial disease. Molecular and Cellular Biology, 44:226-244, Jun 2024. URL: https://doi.org/10.1080/10985549.2024.2353652, doi:10.1080/10985549.2024.2353652. This article has 12 citations and is from a domain leading peer-reviewed journal.
-
(paz2024biochemicalandneurophysiological pages 1-2): Eyal Paz, Sahil Jain, Irit Gottfried, Orna Staretz-Chacham, Muhammad Mahajnah, Pritha Bagchi, Nicholas T Seyfried, Uri Ashery, and Abdussalam Azem. Biochemical and neurophysiological effects of deficiency of the mitochondrial import protein timm50. eLife, Dec 2024. URL: https://doi.org/10.7554/elife.99914, doi:10.7554/elife.99914. This article has 6 citations and is from a domain leading peer-reviewed journal.
-
(crameri2024reducedproteinimport pages 1-3): Jordan J. Crameri, Catherine S. Palmer, Tegan Stait, Thomas D. Jackson, Matthew Lynch, Adriane Sinclair, Leah E. Frajman, Alison G. Compton, David Coman, David R. Thorburn, Ann E. Frazier, and Diana Stojanovski. Reduced protein import via tim23 sort drives disease pathology in timm50-associated mitochondrial disease. Molecular and Cellular Biology, 44:226-244, Jun 2024. URL: https://doi.org/10.1080/10985549.2024.2353652, doi:10.1080/10985549.2024.2353652. This article has 12 citations and is from a domain leading peer-reviewed journal.
-
(tort2019mutationsintimm50 pages 2-3): Frederic Tort, Olatz Ugarteburu, Laura Texidó, Sabrina Gea‐Sorlí, Judit García‐Villoria, Xènia Ferrer‐Cortès, Ángela Arias, Leslie Matalonga, Laura Gort, Isidre Ferrer, Mariona Guitart‐Mampel, Glòria Garrabou, Frederick M Vaz, Ana Pristoupilova, María Isabel Esteban Rodríguez, Sergi Beltran, Francesc Cardellach, Ronald JA Wanders, Cristina Fillat, María Teresa García‐Silva, and Antonia Ribes. Mutations in timm50 cause severe mitochondrial dysfunction by targeting key aspects of mitochondrial physiology. Human Mutation, 40:1700-1712, May 2019. URL: https://doi.org/10.1002/humu.23779, doi:10.1002/humu.23779. This article has 30 citations and is from a domain leading peer-reviewed journal.
-
(shahrour2017mitochondrialepilepticencephalopathy pages 2-4): M.A. Shahrour, O. Staretz‐Chacham, D. Dayan, J. Stephen, A. Weech, N. Damseh, H. Pri Chen, S. Edvardson, S. Mazaheri, A. Saada, E. Hershkovitz, A. Shaag, M. Huizing, B. Abu‐Libdeh, W.A Gahl, A. Azem, Y. Anikster, T. Vilboux, O. Elpeleg, and M.C. Malicdan. Mitochondrial epileptic encephalopathy, 3‐methylglutaconic aciduria and variable complex v deficiency associated with timm50 mutations. Clinical Genetics, 91:690-696, May 2017. URL: https://doi.org/10.1111/cge.12855, doi:10.1111/cge.12855. This article has 49 citations and is from a peer-reviewed journal.
-
(tort2019mutationsintimm50 pages 1-2): Frederic Tort, Olatz Ugarteburu, Laura Texidó, Sabrina Gea‐Sorlí, Judit García‐Villoria, Xènia Ferrer‐Cortès, Ángela Arias, Leslie Matalonga, Laura Gort, Isidre Ferrer, Mariona Guitart‐Mampel, Glòria Garrabou, Frederick M Vaz, Ana Pristoupilova, María Isabel Esteban Rodríguez, Sergi Beltran, Francesc Cardellach, Ronald JA Wanders, Cristina Fillat, María Teresa García‐Silva, and Antonia Ribes. Mutations in timm50 cause severe mitochondrial dysfunction by targeting key aspects of mitochondrial physiology. Human Mutation, 40:1700-1712, May 2019. URL: https://doi.org/10.1002/humu.23779, doi:10.1002/humu.23779. This article has 30 citations and is from a domain leading peer-reviewed journal.
-
(reyes2018mutationsintimm50 pages 2-3): Aurelio Reyes, Laura Melchionda, Alberto Burlina, Alan J Robinson, Daniele Ghezzi, and Massimo Zeviani. Mutations in timm50 compromise cell survival in oxphos‐dependent metabolic conditions. EMBO Molecular Medicine, Sep 2018. URL: https://doi.org/10.15252/emmm.201708698, doi:10.15252/emmm.201708698. This article has 40 citations and is from a highest quality peer-reviewed journal.
-
(crameri2024reducedproteinimport pages 4-5): Jordan J. Crameri, Catherine S. Palmer, Tegan Stait, Thomas D. Jackson, Matthew Lynch, Adriane Sinclair, Leah E. Frajman, Alison G. Compton, David Coman, David R. Thorburn, Ann E. Frazier, and Diana Stojanovski. Reduced protein import via tim23 sort drives disease pathology in timm50-associated mitochondrial disease. Molecular and Cellular Biology, 44:226-244, Jun 2024. URL: https://doi.org/10.1080/10985549.2024.2353652, doi:10.1080/10985549.2024.2353652. This article has 12 citations and is from a domain leading peer-reviewed journal.
-
(reyes2018mutationsintimm50 pages 3-6): Aurelio Reyes, Laura Melchionda, Alberto Burlina, Alan J Robinson, Daniele Ghezzi, and Massimo Zeviani. Mutations in timm50 compromise cell survival in oxphos‐dependent metabolic conditions. EMBO Molecular Medicine, Sep 2018. URL: https://doi.org/10.15252/emmm.201708698, doi:10.15252/emmm.201708698. This article has 40 citations and is from a highest quality peer-reviewed journal.
-
(mir2020completeresolutionof pages 1-2): Ali Mir, Safeya Hadab, Mohammed Sammak, Rami Alhazmi, Yousef Housawi, and Shahid Bashir. Complete resolution of epileptic spasms with vigabatrin in a patient with 3‐methylglutaconic aciduria caused by timm50 gene mutation. Clinical Genetics, 98:102-103, May 2020. URL: https://doi.org/10.1111/cge.13763, doi:10.1111/cge.13763. This article has 10 citations and is from a peer-reviewed journal.
-
(shahrour2017mitochondrialepilepticencephalopathy pages 4-5): M.A. Shahrour, O. Staretz‐Chacham, D. Dayan, J. Stephen, A. Weech, N. Damseh, H. Pri Chen, S. Edvardson, S. Mazaheri, A. Saada, E. Hershkovitz, A. Shaag, M. Huizing, B. Abu‐Libdeh, W.A Gahl, A. Azem, Y. Anikster, T. Vilboux, O. Elpeleg, and M.C. Malicdan. Mitochondrial epileptic encephalopathy, 3‐methylglutaconic aciduria and variable complex v deficiency associated with timm50 mutations. Clinical Genetics, 91:690-696, May 2017. URL: https://doi.org/10.1111/cge.12855, doi:10.1111/cge.12855. This article has 49 citations and is from a peer-reviewed journal.
-
(jain2024hotspotsfordiseasecausing pages 4-5): Sahil Jain, Eyal Paz, and Abdussalam Azem. Hotspots for disease-causing mutations in the mitochondrial tim23 import complex. Genes, 15:1534, Nov 2024. URL: https://doi.org/10.3390/genes15121534, doi:10.3390/genes15121534. This article has 1 citations.
-
(tort2019mutationsintimm50 pages 3-5): Frederic Tort, Olatz Ugarteburu, Laura Texidó, Sabrina Gea‐Sorlí, Judit García‐Villoria, Xènia Ferrer‐Cortès, Ángela Arias, Leslie Matalonga, Laura Gort, Isidre Ferrer, Mariona Guitart‐Mampel, Glòria Garrabou, Frederick M Vaz, Ana Pristoupilova, María Isabel Esteban Rodríguez, Sergi Beltran, Francesc Cardellach, Ronald JA Wanders, Cristina Fillat, María Teresa García‐Silva, and Antonia Ribes. Mutations in timm50 cause severe mitochondrial dysfunction by targeting key aspects of mitochondrial physiology. Human Mutation, 40:1700-1712, May 2019. URL: https://doi.org/10.1002/humu.23779, doi:10.1002/humu.23779. This article has 30 citations and is from a domain leading peer-reviewed journal.
-
(crameri2024reducedproteinimport pages 6-9): Jordan J. Crameri, Catherine S. Palmer, Tegan Stait, Thomas D. Jackson, Matthew Lynch, Adriane Sinclair, Leah E. Frajman, Alison G. Compton, David Coman, David R. Thorburn, Ann E. Frazier, and Diana Stojanovski. Reduced protein import via tim23 sort drives disease pathology in timm50-associated mitochondrial disease. Molecular and Cellular Biology, 44:226-244, Jun 2024. URL: https://doi.org/10.1080/10985549.2024.2353652, doi:10.1080/10985549.2024.2353652. This article has 12 citations and is from a domain leading peer-reviewed journal.
-
(crameri2024reducedproteinimport media d6c9828b): Jordan J. Crameri, Catherine S. Palmer, Tegan Stait, Thomas D. Jackson, Matthew Lynch, Adriane Sinclair, Leah E. Frajman, Alison G. Compton, David Coman, David R. Thorburn, Ann E. Frazier, and Diana Stojanovski. Reduced protein import via tim23 sort drives disease pathology in timm50-associated mitochondrial disease. Molecular and Cellular Biology, 44:226-244, Jun 2024. URL: https://doi.org/10.1080/10985549.2024.2353652, doi:10.1080/10985549.2024.2353652. This article has 12 citations and is from a domain leading peer-reviewed journal.
-
(paz2024biochemicalandneurophysiological pages 4-6): Eyal Paz, Sahil Jain, Irit Gottfried, Orna Staretz-Chacham, Muhammad Mahajnah, Pritha Bagchi, Nicholas T Seyfried, Uri Ashery, and Abdussalam Azem. Biochemical and neurophysiological effects of deficiency of the mitochondrial import protein timm50. eLife, Dec 2024. URL: https://doi.org/10.7554/elife.99914, doi:10.7554/elife.99914. This article has 6 citations and is from a domain leading peer-reviewed journal.
-
(paz2024biochemicalandneurophysiological pages 9-11): Eyal Paz, Sahil Jain, Irit Gottfried, Orna Staretz-Chacham, Muhammad Mahajnah, Pritha Bagchi, Nicholas T Seyfried, Uri Ashery, and Abdussalam Azem. Biochemical and neurophysiological effects of deficiency of the mitochondrial import protein timm50. eLife, Dec 2024. URL: https://doi.org/10.7554/elife.99914, doi:10.7554/elife.99914. This article has 6 citations and is from a domain leading peer-reviewed journal.
-
(crameri2024reducedproteinimport pages 5-6): Jordan J. Crameri, Catherine S. Palmer, Tegan Stait, Thomas D. Jackson, Matthew Lynch, Adriane Sinclair, Leah E. Frajman, Alison G. Compton, David Coman, David R. Thorburn, Ann E. Frazier, and Diana Stojanovski. Reduced protein import via tim23 sort drives disease pathology in timm50-associated mitochondrial disease. Molecular and Cellular Biology, 44:226-244, Jun 2024. URL: https://doi.org/10.1080/10985549.2024.2353652, doi:10.1080/10985549.2024.2353652. This article has 12 citations and is from a domain leading peer-reviewed journal.
-
(paz2024biochemicalandneurophysiological pages 11-13): Eyal Paz, Sahil Jain, Irit Gottfried, Orna Staretz-Chacham, Muhammad Mahajnah, Pritha Bagchi, Nicholas T Seyfried, Uri Ashery, and Abdussalam Azem. Biochemical and neurophysiological effects of deficiency of the mitochondrial import protein timm50. eLife, Dec 2024. URL: https://doi.org/10.7554/elife.99914, doi:10.7554/elife.99914. This article has 6 citations and is from a domain leading peer-reviewed journal.
-
(paz2024biochemicalandneurophysiological pages 13-14): Eyal Paz, Sahil Jain, Irit Gottfried, Orna Staretz-Chacham, Muhammad Mahajnah, Pritha Bagchi, Nicholas T Seyfried, Uri Ashery, and Abdussalam Azem. Biochemical and neurophysiological effects of deficiency of the mitochondrial import protein timm50. eLife, Dec 2024. URL: https://doi.org/10.7554/elife.99914, doi:10.7554/elife.99914. This article has 6 citations and is from a domain leading peer-reviewed journal.
-
(paz2024biochemicalandneurophysiological pages 2-4): Eyal Paz, Sahil Jain, Irit Gottfried, Orna Staretz-Chacham, Muhammad Mahajnah, Pritha Bagchi, Nicholas T Seyfried, Uri Ashery, and Abdussalam Azem. Biochemical and neurophysiological effects of deficiency of the mitochondrial import protein timm50. eLife, Dec 2024. URL: https://doi.org/10.7554/elife.99914, doi:10.7554/elife.99914. This article has 6 citations and is from a domain leading peer-reviewed journal.
-
(crameri2024reducedproteinimport pages 9-11): Jordan J. Crameri, Catherine S. Palmer, Tegan Stait, Thomas D. Jackson, Matthew Lynch, Adriane Sinclair, Leah E. Frajman, Alison G. Compton, David Coman, David R. Thorburn, Ann E. Frazier, and Diana Stojanovski. Reduced protein import via tim23 sort drives disease pathology in timm50-associated mitochondrial disease. Molecular and Cellular Biology, 44:226-244, Jun 2024. URL: https://doi.org/10.1080/10985549.2024.2353652, doi:10.1080/10985549.2024.2353652. This article has 12 citations and is from a domain leading peer-reviewed journal.
-
(shahrour2017mitochondrialepilepticencephalopathy pages 5-6): M.A. Shahrour, O. Staretz‐Chacham, D. Dayan, J. Stephen, A. Weech, N. Damseh, H. Pri Chen, S. Edvardson, S. Mazaheri, A. Saada, E. Hershkovitz, A. Shaag, M. Huizing, B. Abu‐Libdeh, W.A Gahl, A. Azem, Y. Anikster, T. Vilboux, O. Elpeleg, and M.C. Malicdan. Mitochondrial epileptic encephalopathy, 3‐methylglutaconic aciduria and variable complex v deficiency associated with timm50 mutations. Clinical Genetics, 91:690-696, May 2017. URL: https://doi.org/10.1111/cge.12855, doi:10.1111/cge.12855. This article has 49 citations and is from a peer-reviewed journal.
Artifacts
Reference Validation
Checked with linkml-reference-validator 0.3.0.
Table (click to expand)
| Outcome | Count |
|---|---|
| References checked | 8 |
| Resolved | 8 |
| Unresolved (possible confabulation) | 0 |
| Unverifiable | 0 |
| References weighed for topical relevance | 8 |
| On topic | 3 |
| Off topic | 0 |
All extracted references resolved successfully.
Term Validation
Checked with linkml-term-validator 0.4.5, through the ols: adapter.
Table (click to expand)
| Outcome | Count |
|---|---|
| Terms checked | 2 |
| Resolved | 2 |
| Unresolved (possible confabulation) | 0 |
| Obsolete | 0 |
| Unverifiable | 0 |
| Terms whose name was checked | 2 |
| Terms named correctly | 0 |
| Terms named as a different term | 2 |
Terms the report names something else
These identifiers resolve, so nothing about them looks wrong, and the ontology calls them something unrelated to what the report calls them. That usually means the identifier is not the one the sentence needs:
MONDO:0044724(2 mentions) - the report calls it "if available"; MONDO calls it 3-methylglutaconic aciduria type 9CL:0000540(2 mentions) - the report calls it "verify"; CL calls it neuron