STK4 Deficiency
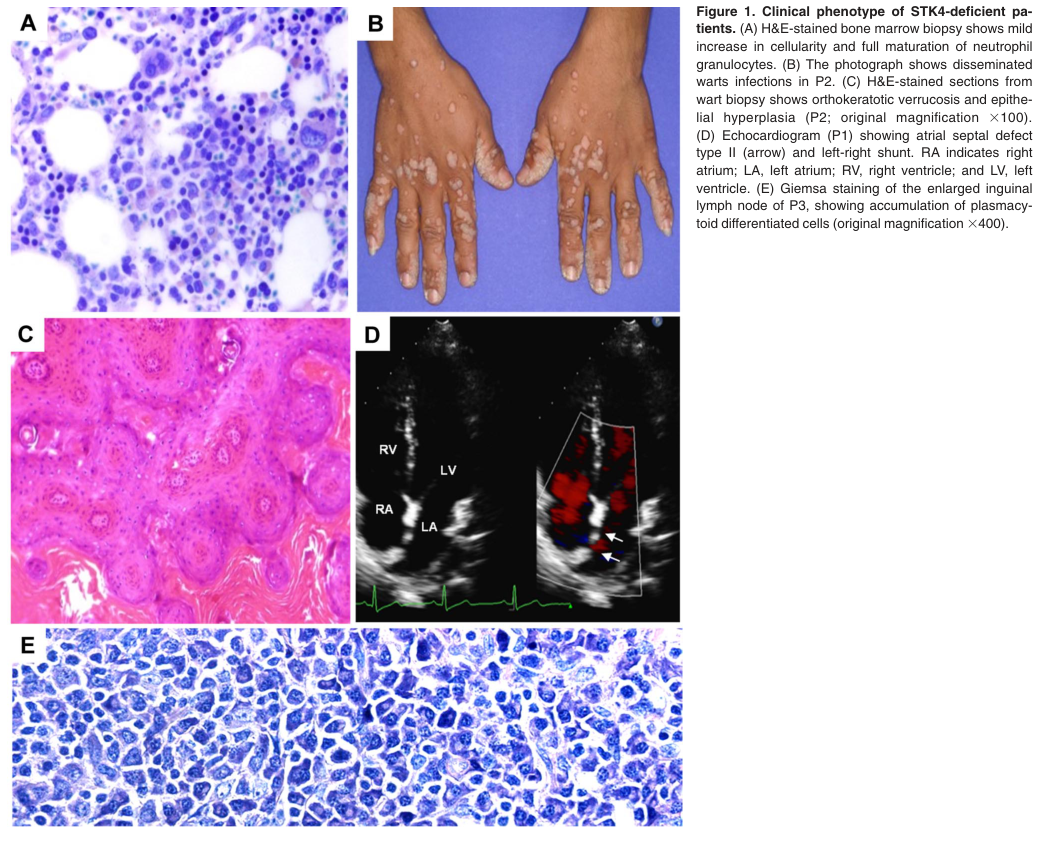
STK4 (MST1) deficiency is an autosomal recessive combined immunodeficiency caused by biallelic loss-of-function variants in STK4, the human ortholog of Drosophila Hippo. Loss of the MST1 kinase impairs naive T-cell survival via defective FOXO1 expression, reduced IL-7 receptor and BCL2, and increased FAS-mediated apoptosis, and additionally impairs lymphocyte adhesion and chemotaxis. The disorder is characterized by progressive T- and B-cell lymphopenia (especially CD4 lymphopenia), intermittent neutropenia, hypergammaglobulinemia and elevated IgE, recurrent bacterial and viral infections, cutaneous viral warts (HPV) and molluscum contagiosum, mucocutaneous candidiasis, autoimmunity, EBV-associated (and EBV-negative) lymphoproliferation and lymphoma, and congenital heart defects such as atrial septal defects.
Ask OpenScientist
Ask a research question about STK4 Deficiency. OpenScientist will conduct autonomous deep research using the Disorder Mechanisms Knowledge Base and PubMed literature (typically 10-30 minutes).
Do not include personal health information in your question. Questions and results are cached in your browser's local storage.
Classifications
Inheritance
1Show evidence (2 references)
Pathophysiology
4Show evidence (3 references)
Show evidence (1 reference)
Show evidence (3 references)
Show evidence (3 references)
Pathograph
Phenotypes
32Blood 16
Show evidence (2 references)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (2 references)
Show evidence (4 references)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (2 references)
Show evidence (2 references)
Show evidence (1 reference)
Cardiovascular 2
Show evidence (1 reference)
Show evidence (1 reference)
Endocrine 1
Show evidence (1 reference)
Immune 11
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Integument 1
Show evidence (2 references)
Growth 1
Show evidence (1 reference)
Genetic Associations
1Show evidence (3 references)
Medical Actions
4Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (2 references)
Show evidence (1 reference)
Progression
2Show evidence (2 references)
Show evidence (1 reference)
Differential Diagnoses
2Conditions with similar clinical presentations that must be differentiated from STK4 Deficiency:
- Progressive T- and B-cell lymphopenia with intermittent neutropenia favours STK4 deficiency.
- Congenital heart defects such as atrial septal defect are reported in STK4 deficiency.
- EBV-driven lymphoproliferation and lymphoma are characteristic of STK4 deficiency.
- Identification of a biallelic loss-of-function STK4 variant is confirmatory.
Show evidence (1 reference)
- ALPS-associated FAS-pathway mutations were absent in the STK4-deficient patients.
- FAS-mediated apoptosis was intact, unlike in genuine ALPS.
- Recurrent infections and CD4 lymphopenia point away from ALPS toward a combined immunodeficiency.
Show evidence (2 references)
Source YAML
click to showname: STK4 Deficiency
creation_date: '2026-06-04T00:00:00Z'
category: Mendelian
synonyms:
- MST1 deficiency
- Combined immunodeficiency due to STK4 deficiency
- T-cell immunodeficiency, recurrent infections, autoimmunity, and cardiac malformations
- TIIAC
description: >-
STK4 (MST1) deficiency is an autosomal recessive combined immunodeficiency
caused by biallelic loss-of-function variants in STK4, the human ortholog of
Drosophila Hippo. Loss of the MST1 kinase impairs naive T-cell survival via
defective FOXO1 expression, reduced IL-7 receptor and BCL2, and increased
FAS-mediated apoptosis, and additionally impairs lymphocyte adhesion and
chemotaxis. The disorder is characterized by progressive T- and B-cell
lymphopenia (especially CD4 lymphopenia), intermittent neutropenia,
hypergammaglobulinemia and elevated IgE, recurrent bacterial and viral
infections, cutaneous viral warts (HPV) and molluscum contagiosum,
mucocutaneous candidiasis, autoimmunity, EBV-associated (and EBV-negative)
lymphoproliferation and lymphoma, and congenital heart defects such as atrial
septal defects.
disease_term:
preferred_term: STK4 deficiency
term:
id: MONDO:0013934
label: combined immunodeficiency due to STK4 deficiency
parents:
- Combined immunodeficiency
- Primary immunodeficiency
classifications:
harrisons_chapter:
- classification_value: IMMUNE_RHEUMATOLOGIC
notes: >-
STK4 deficiency is an inborn error of immunity (primary immunodeficiency),
best classified under disorders of the immune system.
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Serine/threonine kinase 4 (STK4) deficiency is an autosomal recessive
genetic condition that leads to primary immunodeficiency (PID)
explanation: >-
Establishes STK4 deficiency as a primary immunodeficiency, an immune
system disorder under the immunology/rheumatology grouping.
iuis_category:
classification_value: combined immunodeficiency
notes: >-
STK4 (MST1) deficiency is classified by IUIS as a combined immunodeficiency
affecting cellular and humoral immunity (Table 1). The quoted IUIS table
row comes from the classification tables in the cached full text rather
than from the abstract.
evidence:
- reference: PMID:35748970
reference_title: "Human Inborn Errors of Immunity: 2022 Update on the Classification from the International Union of Immunological Societies Expert Committee."
supports: SUPPORT
evidence_source: OTHER
snippet: "STK4 deficiency STK4 AR 614868"
explanation: >-
Table 1 disease-row text listing STK4 deficiency (autosomal recessive)
among the immunodeficiencies affecting cellular and humoral immunity.
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Serine/threonine kinase-4 (STK4) deficiency is an autosomal
recessive combined immunodeficiency.
explanation: >-
Establishes STK4 deficiency as a combined immunodeficiency, consistent
with the IUIS combined-immunodeficiency category.
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
description: >-
STK4 deficiency is inherited in an autosomal recessive pattern and is caused
by biallelic loss-of-function variants in STK4 (MST1).
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Serine/threonine kinase-4 (STK4) deficiency is an autosomal
recessive combined immunodeficiency.
explanation: Supports autosomal recessive inheritance of STK4 deficiency.
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
The patient was born to consanguineous parents living in the United States.
Exome sequencing identified a previously unknown biallelic STK4 stop-gain
mutation (p.Trp425X).
explanation: >-
Documents the autosomal recessive, biallelic nature of STK4 deficiency in a
consanguineous family.
pathophysiology:
- name: Impaired naive T-cell survival
description: >-
Loss of STK4/MST1 kinase reduces survival of naive T cells. MST1-deficient
T cells poorly express the transcription factor FOXO1, the IL-7 receptor,
and BCL2, while FAS expression and FAS-mediated apoptosis are up-regulated,
causing increased death of naive and proliferating T cells. This is the main
mechanism underlying the progressive T-cell lymphopenia.
cell_types:
- preferred_term: naive T cell
term:
id: CL:0000898
label: naive T cell
biological_processes:
- preferred_term: lymphocyte apoptotic process
term:
id: GO:0070227
label: lymphocyte apoptotic process
modifier: INCREASED
- preferred_term: T cell homeostasis
term:
id: GO:0043029
label: T cell homeostasis
modifier: DECREASED
evidence:
- reference: PMID:22174160
reference_title: "MST1 mutations in autosomal recessive primary immunodeficiency characterized by defective naive T-cell survival."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
MST1-deficient T cells poorly expressed the transcription factor FOXO1,
the IL-7 receptor, and BCL2. Conversely, FAS expression and the
FAS-mediating apoptotic pathway were up-regulated.
explanation: >-
Documents the molecular basis of impaired naive T-cell survival: loss of
FOXO1/IL-7R/BCL2 and increased FAS-mediated apoptosis.
- reference: PMID:22174160
reference_title: "MST1 mutations in autosomal recessive primary immunodeficiency characterized by defective naive T-cell survival."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
These abnormalities suggest that increased cell death of naive and
proliferating T cells is the main mechanism underlying this novel
immunodeficiency.
explanation: >-
Identifies increased T-cell death as the central mechanism of the disorder.
- reference: PMID:34427831
reference_title: "A Novel STK4 Mutation Impairs T Cell Immunity Through Dysregulation of Cytokine-Induced Adhesion and Chemotaxis Genes."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
dysregulated interferon signaling, impaired T cell immunity, and increased
T cell apoptosis
explanation: >-
Independent transcriptomic confirmation of impaired T-cell immunity and
increased T-cell apoptosis in an STK4-deficient patient.
downstream:
- target: T-cell lymphopenia
causal_link_type: DIRECT
description: >-
Increased death of naive and proliferating T cells produces the
progressive T-cell (especially CD4) lymphopenia that is a hallmark of the
disorder.
evidence:
- reference: PMID:22174160
reference_title: "MST1 mutations in autosomal recessive primary immunodeficiency characterized by defective naive T-cell survival."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
These abnormalities suggest that increased cell death of naive and
proliferating T cells is the main mechanism underlying this novel
immunodeficiency.
explanation: >-
Links increased T-cell death to the progressive T-cell lymphopenia
characteristic of STK4 deficiency.
- target: B-cell lymphopenia
causal_link_type: INDIRECT_UNKNOWN_INTERMEDIATES
description: >-
The combined T- and B-cell lymphopenia seen in patients accompanies the
naive-T-cell survival defect, with B-cell lymphopenia developing as part
of the same lymphopenic phenotype.
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
We describe a novel clinical phenotype associating T- and B-cell
lymphopenia, intermittent neutropenia, and atrial septal defects in 3
members of a consanguineous kindred.
explanation: >-
Documents B-cell lymphopenia co-occurring with the T-cell defect in
STK4 deficiency.
- target: Increased gamma-delta T cell proportion
causal_link_type: INDIRECT_UNKNOWN_INTERMEDIATES
description: >-
As the conventional alpha-beta CD4+ compartment fails, gamma-delta T cells expand into the
space it leaves. The expansion is read as compensatory rather than as a second lesion, but
it is incomplete compensation - the expanded cells proliferate poorly on activation - and
clinically it is a trap, because it can hold the total CD3+ count in the normal range while
CD4+ cells are profoundly depleted.
evidence:
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
In conclusion, γδ T-cell expansion may act as a compensatory mechanism to combat viral infection, providing immune protection in immunocompromised individuals.
explanation: >-
The authors' interpretation of the expansion as compensatory, which is the claim this edge
records.
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
their ability to proliferate in response to T-cell activation was impaired, as was that of CD4+ T cells.
explanation: >-
Qualifies the compensation: the expanded gamma-delta cells share the proliferative defect
of the CD4+ cells they are standing in for.
- name: Increased lymphocyte and neutrophil apoptosis
description: >-
STK4 is the human ortholog of Drosophila Hippo, the central constituent of a
conserved pathway controlling cell growth and apoptosis. STK4-deficient
lymphocytes and neutrophils show enhanced loss of mitochondrial membrane
potential and increased susceptibility to apoptosis, contributing to
lymphopenia and intermittent neutropenia.
cell_types:
- preferred_term: neutrophil
term:
id: CL:0000775
label: neutrophil
- preferred_term: T cell
term:
id: CL:0000084
label: T cell
biological_processes:
- preferred_term: apoptotic process
term:
id: GO:0006915
label: apoptotic process
modifier: INCREASED
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
STK4-deficient lymphocytes and neutrophils exhibit enhanced loss of
mitochondrial membrane potential and increased susceptibility to
apoptosis.
explanation: >-
Supports increased apoptosis of lymphocytes and neutrophils as a
mechanism of cytopenias in STK4 deficiency.
downstream:
- target: Intermittent neutropenia
causal_link_type: DIRECT
description: >-
Enhanced loss of mitochondrial membrane potential and increased
neutrophil apoptosis produce the intermittent neutropenia observed in
STK4-deficient patients.
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
STK4-deficient lymphocytes and neutrophils exhibit enhanced loss of
mitochondrial membrane potential and increased susceptibility to
apoptosis.
explanation: >-
Connects increased neutrophil apoptosis to the intermittent neutropenia
phenotype.
- name: Defective lymphocyte adhesion and chemotaxis
description: >-
MST1 is required for leukocyte trafficking. STK4-deficient leukocytes show
deficient chemotaxis after chemokine stimulation despite preserved chemokine
receptor expression, and fail to bind effectively to ICAM-1 under flow,
indicating a failure to develop high-affinity integrin binding. This
trafficking defect impairs thymic egress and immune synapse formation,
contributing to immunodeficiency.
cell_types:
- preferred_term: T cell
term:
id: CL:0000084
label: T cell
biological_processes:
- preferred_term: leukocyte chemotaxis
term:
id: GO:0030595
label: leukocyte chemotaxis
modifier: DECREASED
- preferred_term: cell adhesion
term:
id: GO:0007155
label: cell adhesion
modifier: DECREASED
evidence:
- reference: PMID:26801501
reference_title: "Defective Leukocyte Adhesion and Chemotaxis Contributes to Combined Immunodeficiency in Humans with Autosomal Recessive MST1 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Patient leukocytes exhibited deficient chemotaxis after stimulation with
CXCL11, despite preserved expression of CXCR3. Patient lymphocytes were
also unable to bind effectively to immobilised ICAM-1 under flow
conditions, in keeping with a failure to develop high affinity binding.
explanation: >-
Documents the adhesion and chemotaxis defect in MST1-deficient leukocytes.
- reference: PMID:26801501
reference_title: "Defective Leukocyte Adhesion and Chemotaxis Contributes to Combined Immunodeficiency in Humans with Autosomal Recessive MST1 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
The observed abnormalities of adhesion and migration imply a profound
trafficking defect among human MST1-deficient lymphocytes.
explanation: >-
Connects the adhesion/chemotaxis defect to a global lymphocyte trafficking
defect contributing to immunodeficiency.
- reference: PMID:34427831
reference_title: "A Novel STK4 Mutation Impairs T Cell Immunity Through Dysregulation of Cytokine-Induced Adhesion and Chemotaxis Genes."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
impaired regulation of cytokine-induced adhesion and leukocyte chemotaxis
genes.
explanation: >-
Transcriptomic analysis of an STK4-deficient patient shows dysregulation of
cytokine-induced adhesion and chemotaxis gene programs, corroborating the
trafficking defect.
downstream:
- target: Recurrent bacterial infections
causal_link_type: INDIRECT_UNKNOWN_INTERMEDIATES
description: >-
The profound lymphocyte trafficking defect impairs leukocyte recruitment
to sites of infection, contributing to the recurrent bacterial infections
seen in STK4 deficiency.
evidence:
- reference: PMID:26801501
reference_title: "Defective Leukocyte Adhesion and Chemotaxis Contributes to Combined Immunodeficiency in Humans with Autosomal Recessive MST1 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
The observed abnormalities of adhesion and migration imply a profound
trafficking defect among human MST1-deficient lymphocytes.
explanation: >-
Links the leukocyte trafficking defect to the combined immunodeficiency
underlying recurrent bacterial infections.
- target: Recurrent pneumonia
causal_link_type: INDIRECT_UNKNOWN_INTERMEDIATES
description: >-
Defective leukocyte trafficking to the lungs, together with impaired
cellular immunity, predisposes to the recurrent pneumonia that is a
frequent complication of STK4 deficiency.
evidence:
- reference: PMID:26801501
reference_title: "Defective Leukocyte Adhesion and Chemotaxis Contributes to Combined Immunodeficiency in Humans with Autosomal Recessive MST1 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
The observed abnormalities of adhesion and migration imply a profound
trafficking defect among human MST1-deficient lymphocytes.
explanation: >-
Links the lymphocyte trafficking defect to impaired pulmonary host
defense and recurrent pneumonia.
- name: Impaired innate antiviral interferon signaling
description: >-
Beyond its role in lymphocyte survival, STK4/MST1 is required for innate
antiviral immunity. STK4-deficient cells show significantly impaired type I,
II, and III interferon responses and reduced proinflammatory cytokine
responses to TLR3, TLR9, and cytosolic nucleic-acid sensor ligands. The
interferon defect is attributable to reduced phosphorylation of TBK1 and
IRF3, and virus infection induces enhanced apoptotic cell death. This innate
antiviral defect contributes to the prominent susceptibility to herpesviruses
(EBV, VZV) and papillomaviruses.
cell_types:
- preferred_term: plasmacytoid dendritic cell
term:
id: CL:0000784
label: plasmacytoid dendritic cell
- preferred_term: macrophage
term:
id: CL:0000235
label: macrophage
biological_processes:
- preferred_term: type I interferon-mediated signaling pathway
term:
id: GO:0060337
label: type I interferon-mediated signaling pathway
modifier: DECREASED
- preferred_term: defense response to virus
term:
id: GO:0051607
label: defense response to virus
modifier: DECREASED
evidence:
- reference: PMID:33078349
reference_title: "STK4 Deficiency Impairs Innate Immunity and Interferon Production Through Negative Regulation of TBK1-IRF3 Signaling."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
We show significantly impaired type I, II, and III interferon (IFN)
responses and partly reduced proinflammatory cytokine responses to ligands
of Toll-like receptor (TLR)3, TLR9, and the cytosolic RNA and DNA sensors
explanation: >-
Documents the impaired type I, II, and III interferon responses in STK4
deficiency.
- reference: PMID:33078349
reference_title: "STK4 Deficiency Impairs Innate Immunity and Interferon Production Through Negative Regulation of TBK1-IRF3 Signaling."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Impaired IFN responses could be attributed to reduced phosphorylation of
TBK1 and IRF3. Moreover, virus infection induced enhanced cell death by
apoptosis.
explanation: >-
Identifies the TBK1-IRF3 axis as the molecular basis of the interferon
defect and links viral infection to enhanced apoptosis.
- reference: PMID:34427831
reference_title: "A Novel STK4 Mutation Impairs T Cell Immunity Through Dysregulation of Cytokine-Induced Adhesion and Chemotaxis Genes."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
abnormal fractions of T cell subsets, plasmacytoid dendritic cells, and
NK cells
explanation: >-
Documents abnormal plasmacytoid dendritic cell fractions in an
STK4-deficient patient, supporting involvement of this type I
interferon-producing cell type.
downstream:
- target: Recurrent viral infections
causal_link_type: DIRECT
description: >-
The impaired type I/II/III interferon response and enhanced
virus-induced apoptosis impair antiviral defense, producing the prominent
susceptibility to viral infections.
evidence:
- reference: PMID:33078349
reference_title: "STK4 Deficiency Impairs Innate Immunity and Interferon Production Through Negative Regulation of TBK1-IRF3 Signaling."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Impaired IFN responses could be attributed to reduced phosphorylation of
TBK1 and IRF3. Moreover, virus infection induced enhanced cell death by
apoptosis.
explanation: >-
Links the interferon defect and virus-induced apoptosis to impaired
antiviral defense underlying recurrent viral infections.
- target: Recurrent herpes zoster
causal_link_type: DIRECT
description: >-
The innate antiviral interferon defect underlies the severe recurrent
herpesvirus infections, including herpes zoster.
evidence:
- reference: PMID:33078349
reference_title: "STK4 Deficiency Impairs Innate Immunity and Interferon Production Through Negative Regulation of TBK1-IRF3 Signaling."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
a clinical presentation consisting of severe recurrent herpes zoster,
chronic warts, and recurrent pneumonias
explanation: >-
Connects the interferon-signaling defect to the severe recurrent herpes
zoster phenotype.
- target: Persistent EBV viremia
causal_link_type: INDIRECT_UNKNOWN_INTERMEDIATES
description: >-
Impaired antiviral immunity contributes to failure to control
Epstein-Barr virus, manifesting as persistent EBV viremia.
evidence:
- reference: PMID:34427831
reference_title: "A Novel STK4 Mutation Impairs T Cell Immunity Through Dysregulation of Cytokine-Induced Adhesion and Chemotaxis Genes."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
recurrent viral and bacterial infections, notably persistent Epstein-Barr
virus viremia and pulmonary tuberculosis.
explanation: >-
Documents persistent EBV viremia as a consequence of impaired antiviral
immunity in an STK4-deficient patient.
- target: Persistent human papillomavirus infection
causal_link_type: INDIRECT_UNKNOWN_INTERMEDIATES
description: >-
Failure of the interferon-dependent antiviral response permits infection by
beta-papillomaviruses that are not virulent in immunocompetent hosts, producing
epidermodysplasia verruciformis at the severe end of the cutaneous viral spectrum.
evidence:
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
We describe here a patient in his thirties who presented with epidermodysplasia verruciformis (EV) due to infection with a weakly virulent beta-papillomavirus (HPV38) and CD4+ T-cell lymphopenia.
explanation: >-
Links the STK4-deficient immune defect to disease from a papillomavirus that is
specifically noted as weakly virulent.
phenotypes:
- name: Recurrent bacterial infections
description: >-
Patients have a history of recurrent bacterial infections including
respiratory infections, skin abscesses, and septicemia.
phenotype_term:
preferred_term: Recurrent bacterial infections
term:
id: HP:0002718
label: Recurrent bacterial infections
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Their clinical histories included recurrent bacterial infections, viral
infections, mucocutaneous candidiasis, cutaneous warts, and skin
abscesses.
explanation: Documents recurrent bacterial infections and skin abscesses.
- name: Recurrent pneumonia
description: >-
Recurrent pneumonia is a frequent complication, reported in 18 of 24
reviewed patients, reflecting impaired cellular immunity and defective
leukocyte trafficking to the lungs.
phenotype_term:
preferred_term: Recurrent pneumonia
term:
id: HP:0006532
label: Recurrent pneumonia
frequency: FREQUENT
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "recurrent pneumonia (n = 18)"
explanation: >-
In a combined cohort of 24 patients, recurrent pneumonia was reported in
18 (75%), supporting frequent occurrence (30-79% band).
- name: Recurrent viral infections
description: >-
Patients experience recurrent viral infections, particularly cutaneous viral
infections (HPV warts, molluscum contagiosum) and EBV.
phenotype_term:
preferred_term: Recurrent viral infections
term:
id: HP:0004429
label: Recurrent viral infections
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Their clinical histories included recurrent bacterial infections, viral
infections, mucocutaneous candidiasis, cutaneous warts, and skin
abscesses.
explanation: Documents recurrent viral infections in STK4 deficiency.
- name: Persistent EBV viremia
description: >-
Persistent Epstein-Barr virus viremia is a characteristic feature reflecting
impaired antiviral T-cell immunity and predisposes to EBV-associated
lymphoproliferation and lymphoma.
phenotype_term:
preferred_term: Persistent EBV viremia
term:
id: HP:0020072
label: Persistent EBV viremia
temporality: CHRONIC
evidence:
- reference: PMID:34427831
reference_title: "A Novel STK4 Mutation Impairs T Cell Immunity Through Dysregulation of Cytokine-Induced Adhesion and Chemotaxis Genes."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
recurrent viral and bacterial infections, notably persistent Epstein-Barr
virus viremia and pulmonary tuberculosis.
explanation: Documents persistent EBV viremia in an STK4-deficient patient.
- name: Recurrent herpes zoster
description: >-
Severe recurrent herpesvirus infections, including herpes zoster, occur and
reflect the impaired innate antiviral interferon response and defective
T-cell immunity.
phenotype_term:
preferred_term: Recurrent herpes
term:
id: HP:0005353
label: Recurrent herpes
evidence:
- reference: PMID:33078349
reference_title: "STK4 Deficiency Impairs Innate Immunity and Interferon Production Through Negative Regulation of TBK1-IRF3 Signaling."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
a clinical presentation consisting of severe recurrent herpes zoster,
chronic warts, and recurrent pneumonias
explanation: >-
Documents severe recurrent herpes zoster in an STK4-deficient patient.
- name: Cutaneous viral warts
description: >-
Cutaneous viral (HPV) warts are a characteristic feature; cutaneous viral
infections were present in the large majority of reviewed patients.
phenotype_term:
preferred_term: Cutaneous warts
term:
id: HP:0032215
label: Disseminated cutaneous warts
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Their clinical histories included recurrent bacterial infections, viral
infections, mucocutaneous candidiasis, cutaneous warts, and skin
abscesses.
explanation: Documents cutaneous warts as a clinical feature.
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "cutaneous viral infections (n = 20)"
explanation: >-
In a combined cohort of 24 patients, cutaneous viral infections were the
most common infection, supporting the prominence of cutaneous viral warts.
- name: Mucocutaneous candidiasis
description: >-
Chronic mucocutaneous candidiasis reflects impaired antifungal T-cell
immunity.
phenotype_term:
preferred_term: Mucocutaneous candidiasis
term:
id: HP:0002728
label: Chronic mucocutaneous candidiasis
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Their clinical histories included recurrent bacterial infections, viral
infections, mucocutaneous candidiasis, cutaneous warts, and skin
abscesses.
explanation: Documents mucocutaneous candidiasis as a clinical feature.
- name: T-cell lymphopenia
description: >-
Progressive loss of naive T cells with CD4 lymphopenia is a hallmark of STK4
deficiency; CD4 lymphopenia was present in all patients in a clinical cohort.
phenotype_term:
preferred_term: Decreased total T cell count
term:
id: HP:0005403
label: Decreased total T cell count
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
We describe a novel clinical phenotype associating T- and B-cell
lymphopenia, intermittent neutropenia, and atrial septal defects in 3
members of a consanguineous kindred.
explanation: Documents T-cell lymphopenia.
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "CD4 lymphopenia (9 out 9)"
explanation: CD4 lymphopenia was universal in the clinical cohort.
- name: B-cell lymphopenia
description: >-
B-cell lymphopenia accompanies the T-cell defect, with abnormal B-cell
subsets (increased plasmablasts, decreased switched memory B cells).
phenotype_term:
preferred_term: Decreased total B cell count
term:
id: HP:0010976
label: Decreased total B cell count
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
We describe a novel clinical phenotype associating T- and B-cell
lymphopenia, intermittent neutropenia, and atrial septal defects in 3
members of a consanguineous kindred.
explanation: Documents B-cell lymphopenia.
- name: Intermittent neutropenia
description: >-
Intermittent (transient) neutropenia occurs and reflects increased
neutrophil apoptosis.
phenotype_term:
preferred_term: Neutropenia
term:
id: HP:0001875
label: Decreased total neutrophil count
temporality: TRANSIENT
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
We describe a novel clinical phenotype associating T- and B-cell
lymphopenia, intermittent neutropenia, and atrial septal defects in 3
members of a consanguineous kindred.
explanation: Documents intermittent neutropenia.
- name: Hypergammaglobulinemia
description: >-
Dysregulated immunoglobulin levels are common, including
hypergammaglobulinemia and elevated IgE, alongside low IgM in some patients.
phenotype_term:
preferred_term: Hypergammaglobulinemia
term:
id: HP:0010702
label: Increased circulating immunoglobulin concentration
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
elevated DNT cell number, non-malignant lymphadenopathy and
hepatosplenomegaly, hematolytic anemia, hypergammaglobulinemia.
explanation: Documents hypergammaglobulinemia in an STK4-deficient patient.
- name: Elevated IgE
description: >-
Elevated serum IgE is common and contributes to the differential diagnosis
with autosomal recessive hyper-IgE syndrome.
phenotype_term:
preferred_term: Elevated circulating IgE concentration
term:
id: HP:0003212
label: Increased circulating IgE concentration
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "high IgE (4 out 9)"
explanation: Elevated IgE was a common laboratory finding in the clinical cohort.
- name: Autoimmunity
description: >-
Autoimmune and inflammatory manifestations are common, including autoimmune
hemolytic anemia and other autoimmune phenomena.
phenotype_term:
preferred_term: Autoimmunity
term:
id: HP:0002960
label: Autoimmunity
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "autoimmune or inflammatory diseases (7 of 9)"
explanation: Autoimmune/inflammatory disease was frequent in the clinical cohort.
frequency: FREQUENT
- name: Autoimmune cytopenia
description: >-
Immune-mediated destruction of blood cells - most often haemolytic anaemia - is the commonest
single autoimmune manifestation, and is distinct from the intermittent neutropenia that arises
from increased neutrophil apoptosis.
phenotype_term:
preferred_term: Autoimmune cytopenia
term:
id: HP:5210419
label: Autoimmune cytopenia
frequency: OCCASIONAL
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
When 24 patients are analyzed, cutaneous viral infections (n = 20), recurrent pneumonia (n = 18), Epstein Barr virus-associated lymphoproliferation (n = 11), atopic dermatitis (n = 10), autoimmune cytopenia (n = 7), and lymphoma (n = 6) were frequent.
explanation: Autoimmune cytopenia in 7 of 24 reviewed patients (29%), supporting the occasional band.
- name: Autoimmune hemolytic anemia
description: >-
Autoimmune hemolytic anemia is reported among the autoimmune manifestations
of STK4 deficiency.
phenotype_term:
preferred_term: Autoimmune hemolytic anemia
term:
id: HP:0001890
label: Autoimmune hemolytic anemia
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
elevated DNT cell number, non-malignant lymphadenopathy and
hepatosplenomegaly, hematolytic anemia, hypergammaglobulinemia.
explanation: >-
Documents hemolytic (autoimmune) anemia in an STK4-deficient patient with
ALPS-like features.
- name: Lymphoproliferative disorder
description: >-
EBV-associated lymphoproliferation is characteristic; patients can present
with non-malignant lymphadenopathy, hepatosplenomegaly, and ALPS-like
features.
phenotype_term:
preferred_term: Lymphoproliferative disorder
term:
id: HP:0005523
label: Lymphoproliferative disorder
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Serine/threonine kinase 4 (STK4) deficiency is an autosomal recessive
genetic condition that leads to primary immunodeficiency (PID) typically
characterized by lymphopenia, recurrent infections and Epstein Barr Virus
(EBV) induced lymphoproliferation and -lymphoma.
explanation: >-
Documents EBV-induced lymphoproliferation as a typical feature of STK4
deficiency.
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
When 24 patients are analyzed, cutaneous viral infections (n = 20), recurrent pneumonia (n = 18), Epstein Barr virus-associated lymphoproliferation (n = 11), atopic dermatitis (n = 10), autoimmune cytopenia (n = 7), and lymphoma (n = 6) were frequent.
explanation: >-
EBV-associated lymphoproliferation in 11 of 24 reviewed patients (46%), supporting the
frequent band.
frequency: FREQUENT
- name: Hepatosplenomegaly
description: >-
Hepatosplenomegaly occurs as part of the ALPS-like lymphoproliferative
presentation alongside non-malignant lymphadenopathy.
phenotype_term:
preferred_term: Hepatosplenomegaly
term:
id: HP:0001433
label: Hepatosplenomegaly
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
elevated DNT cell number, non-malignant lymphadenopathy and
hepatosplenomegaly, hematolytic anemia, hypergammaglobulinemia.
explanation: >-
Documents hepatosplenomegaly as part of the ALPS-like presentation in an
STK4-deficient patient.
- name: Lymphoma
description: >-
Patients are prone to lymphoma, including EBV-associated and EBV-negative
B-cell lymphoma, diffuse large B-cell lymphoma, and Hodgkin lymphoma. The
authors who reported the first EBV-negative case proposed either loss of the
tumour-suppressive function of STK4 or perturbed immune surveillance from the
CD4+ T-cell deficit as the explanation; neither has been established over the
other, so both are recorded as candidate mechanisms rather than as the cause.
phenotype_term:
preferred_term: Lymphoma
term:
id: HP:0002665
label: Lymphoma
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Patient P1 developed a highly malignant B cell lymphoma at the age of 10
years and a second, independent Hodgkin lymphoma 5 years later.
explanation: Documents lymphoma development in an STK4-deficient patient.
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Lymphoma development may be due to the lacking tumor suppressive function of STK4 or the perturbed immune surveillance due to the lack of CD4+ T cells.
directness: INDIRECT
explanation: >-
The proposed mechanism behind the lymphoma predisposition. Indirect because the
authors offer it as a hypothesis with two alternatives rather than as a demonstrated
mechanism; the description above is worded to match that hedge.
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
When 24 patients are analyzed, cutaneous viral infections (n = 20), recurrent pneumonia (n = 18), Epstein Barr virus-associated lymphoproliferation (n = 11), atopic dermatitis (n = 10), autoimmune cytopenia (n = 7), and lymphoma (n = 6) were frequent.
explanation: Lymphoma in 6 of 24 reviewed patients (25%), supporting the occasional band.
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
he developed diffuse large B-cell lymphoma (DLBCL) and EBV viremia with a low viral load in his thirties.
explanation: >-
Documents DLBCL arising in adulthood, showing the lymphoma risk is not confined to
childhood.
frequency: OCCASIONAL
- name: Atrial septal defect
description: >-
Congenital heart defects, particularly atrial septal defects, occur in STK4
deficiency.
phenotype_term:
preferred_term: Atrial septal defect
term:
id: HP:0001631
label: Atrial septal defect
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
We describe a novel clinical phenotype associating T- and B-cell
lymphopenia, intermittent neutropenia, and atrial septal defects in 3
members of a consanguineous kindred.
explanation: Documents atrial septal defects as a congenital cardiac feature.
- name: Atopic dermatitis
description: >-
Atopy is common enough to be a diagnostic trap: it is one of the two features (with CD4
lymphopenia) that STK4 deficiency shares with autosomal recessive hyper-IgE syndrome, and it
is why the differential between them matters.
phenotype_term:
preferred_term: Atopic dermatitis
term:
id: HP:0001047
label: Atopic dermatitis
frequency: FREQUENT
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
When 24 patients are analyzed, cutaneous viral infections (n = 20), recurrent pneumonia (n = 18), Epstein Barr virus-associated lymphoproliferation (n = 11), atopic dermatitis (n = 10), autoimmune cytopenia (n = 7), and lymphoma (n = 6) were frequent.
explanation: >-
Atopic dermatitis in 10 of 24 reviewed patients (42%), supporting the frequent band.
- name: Eosinophilia
description: Intermittent eosinophilia accompanies the atopic phenotype.
phenotype_term:
preferred_term: Intermittent eosinophilia
term:
id: HP:0001880
label: Increased total eosinophil count
temporality: RECURRENT
frequency: FREQUENT
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "intermittent eosinophilia (4 out 9)"
explanation: >-
Intermittent eosinophilia in 4 of 9 patients in the clinical cohort (44%), supporting the
frequent band.
- name: Decreased circulating IgM concentration
description: >-
Immunoglobulin levels in STK4 deficiency are dysregulated rather than uniformly low or high:
IgG, IgA and IgE are commonly raised while IgM is often reduced. An entry that recorded only
the hypergammaglobulinaemia would mislead a reader into expecting all classes to move
together.
phenotype_term:
preferred_term: Low serum IgM
term:
id: HP:0002850
label: Decreased circulating total IgM
frequency: FREQUENT
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "low IgM (4 out 9)"
explanation: Low IgM in 4 of 9 patients in the clinical cohort (44%), supporting the frequent band.
- name: Decreased naive T cell proportion
description: >-
The T-cell compartment is skewed as well as depleted: recent thymic emigrants, naive T cells
and central memory T cells all fall while effector memory T cells rise. This is the cellular
signature of the naive-T-cell survival defect, and it is measurable before total counts drop.
phenotype_term:
preferred_term: Decreased recent thymic emigrants and naive T cells
term:
id: HP:0031397
label: Decreased naive T cell proportion
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Decreased recent thymic emigrants, naive and central memory T cells, but increased effector memory T cells were present.
explanation: >-
Directly reports the decrease in recent thymic emigrants and naive T cells with a reciprocal
effector-memory increase.
- name: Increased plasmablast proportion
description: >-
The B-cell compartment is abnormal in composition, not only in number. Plasmablasts are
increased and class-switched memory B cells decreased, both statistically significant against
age-matched controls.
phenotype_term:
preferred_term: Increased plasmablast proportion
term:
id: HP:0032128
label: Increased plasmablast proportion
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
The increase in plasmablasts (P = .003) and decrease in switched memory B cells (P = .022) were significant.
explanation: >-
Quantifies the plasmablast increase against age-matched healthy controls with a reported p
value.
- name: Decreased class-switched memory B cell proportion
description: >-
Reduced class-switched memory B cells accompany the plasmablast expansion and are the B-cell
correlate of impaired humoral memory.
phenotype_term:
preferred_term: Decreased switched memory B cell proportion
term:
id: HP:0030388
label: Decreased class-switched memory B cell proportion
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
The increase in plasmablasts (P = .003) and decrease in switched memory B cells (P = .022) were significant.
explanation: Quantifies the switched-memory B-cell decrease with a reported p value.
- name: Increased double-negative T cell number
description: >-
Elevated CD4-CD8- double-negative T cells are the finding that makes STK4 deficiency
mimic ALPS. Critically, the resemblance is superficial: in the reported patients neither an
ALPS-associated FAS-pathway mutation nor a FAS-mediated apoptosis defect was present.
phenotype_term:
preferred_term: Elevated double-negative T cell number
term:
id: HP:0002851
label: Increased double-negative T cell number
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
elevated DNT cell number, non-malignant lymphadenopathy and
hepatosplenomegaly, hematolytic anemia, hypergammaglobulinemia.
explanation: Documents elevated double-negative T cell number in an STK4-deficient patient.
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
None of the patients harbored typically ALPS-associated mutations of the Fas receptor mediated apoptotic pathway and Fas-mediated apoptosis was not affected.
explanation: >-
The negative result that separates this ALPS-like presentation from genuine ALPS, and the
basis for the differential diagnosis curated below.
- name: Increased gamma-delta T cell proportion
description: >-
Gamma-delta T cells expand, and in one adult patient the expanded population accounted for
most circulating CD3+ cells despite a low CD4+ count - so a normal total CD3 count can conceal
the CD4 deficit. The proposed reading is compensatory rather than pathological, though the
expanded cells were themselves functionally impaired.
phenotype_term:
preferred_term: Vd2 gamma-delta T cell expansion
term:
id: HP:0500270
label: Increased gamma-delta T cell proportion
evidence:
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Despite his low CD4+ T-cell count, the patient had normal counts of CD3+ cells, predominantly double-negative T cells (67.4%), which turned out to be Vδ2+ γδ T cells.
explanation: >-
Quantifies the gamma-delta expansion and shows it masking the CD4 deficit behind a normal
CD3 count.
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
γδ T-cell expansion has frequently been observed in the 33 reported cases with STK4 deficiency.
explanation: >-
Establishes that the expansion is a recurring feature across the reported case series, not a
one-patient observation.
- name: Persistent human papillomavirus infection
description: >-
Beyond ordinary cutaneous warts, STK4 deficiency can produce epidermodysplasia verruciformis -
disseminated infection with a beta-papillomavirus that is not virulent in immunocompetent
hosts. The reported patient's HPV38 disease is the clearest demonstration that the
papillomavirus susceptibility here is qualitative and not just a matter of wart burden.
phenotype_term:
preferred_term: Epidermodysplasia verruciformis due to HPV38
term:
id: HP:0020114
label: Persistent human papillomavirus infection
evidence:
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
We describe here a patient in his thirties who presented with epidermodysplasia verruciformis (EV) due to infection with a weakly virulent beta-papillomavirus (HPV38) and CD4+ T-cell lymphopenia.
explanation: >-
Documents epidermodysplasia verruciformis from a weakly virulent beta-papillomavirus in a
genetically confirmed STK4-deficient patient.
- name: Decreased specific antibody response to vaccination
description: >-
Insufficient vaccine responses were documented alongside the T-cell abnormalities, which
matters practically: it is part of the case for immunoglobulin replacement rather than relying
on active immunisation.
phenotype_term:
preferred_term: Insufficient vaccination responses
term:
id: HP:0032140
label: Decreased specific antibody response to vaccination
evidence:
- reference: PMID:33078349
reference_title: "STK4 Deficiency Impairs Innate Immunity and Interferon Production Through Negative Regulation of TBK1-IRF3 Signaling."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
the patient displayed some indicators of impaired adaptive immunity in the form of insufficient vaccination responses, T cell lymphopenia, and reduced Treg fractions
explanation: Documents insufficient vaccination responses in an STK4-deficient patient.
- name: Decreased regulatory T cell proportion
description: >-
Reduced regulatory T-cell fractions offer a plausible link between the same lesion and the
autoimmune half of the phenotype, which the T-cell survival defect alone does not explain.
phenotype_term:
preferred_term: Reduced Treg fractions
term:
id: HP:0020113
label: Decreased regulatory T cell proportion
evidence:
- reference: PMID:33078349
reference_title: "STK4 Deficiency Impairs Innate Immunity and Interferon Production Through Negative Regulation of TBK1-IRF3 Signaling."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
the patient displayed some indicators of impaired adaptive immunity in the form of insufficient vaccination responses, T cell lymphopenia, and reduced Treg fractions
explanation: Documents reduced regulatory T-cell fractions in an STK4-deficient patient.
- name: Hypothyroidism
description: >-
A non-immunological feature reported in one patient. Recorded because the entry otherwise
reads as a purely immune disorder, and STK4/MST1 is a Hippo-pathway kinase with roles beyond
lymphocytes; a single case does not establish it as a disease feature.
phenotype_term:
preferred_term: Hypothyroidism
term:
id: HP:0000821
label: Hypothyroidism
evidence:
- reference: PMID:33078349
reference_title: "STK4 Deficiency Impairs Innate Immunity and Interferon Production Through Negative Regulation of TBK1-IRF3 Signaling."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
as well as a somatic phenotype with hypothyroidism and low stature
explanation: Documents hypothyroidism as part of the somatic phenotype in one patient.
- name: Short stature
description: Reported with hypothyroidism as part of the somatic phenotype in one patient.
phenotype_term:
preferred_term: Low stature
term:
id: HP:0004322
label: Short stature
evidence:
- reference: PMID:33078349
reference_title: "STK4 Deficiency Impairs Innate Immunity and Interferon Production Through Negative Regulation of TBK1-IRF3 Signaling."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
as well as a somatic phenotype with hypothyroidism and low stature
explanation: Documents low stature as part of the somatic phenotype in one patient.
genetic:
- name: STK4
gene_term:
preferred_term: STK4
term:
id: hgnc:11408
label: STK4
association: CAUSATIVE
notes: >-
STK4 deficiency is caused by biallelic loss-of-function variants in STK4
(formerly MST1), typically homozygous premature-termination, frameshift,
nonsense, or splice-site mutations that abolish MST1 protein expression.
evidence:
- reference: PMID:22294732
reference_title: "The phenotype of human STK4 deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Homozygosity mapping and candidate gene sequencing revealed a homozygous
premature termination mutation in the gene STK4 (serine threonine kinase
4, formerly having the symbol MST1).
explanation: >-
Establishes STK4 (MST1) as the causative gene with a homozygous
loss-of-function mutation.
- reference: PMID:22174160
reference_title: "MST1 mutations in autosomal recessive primary immunodeficiency characterized by defective naive T-cell survival."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
we report a primary immunodeficiency phenotype associated with MST1
deficiency and primarily characterized by a progressive loss of naive T
cells.
explanation: >-
Independent identification of MST1 (STK4) deficiency as the cause of this
primary immunodeficiency.
- reference: PMID:34427831
reference_title: "A Novel STK4 Mutation Impairs T Cell Immunity Through Dysregulation of Cytokine-Induced Adhesion and Chemotaxis Genes."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
a novel, homozygous nonsense STK4 mutation (NM_006282.2:c.871C > T,
p.Arg291*) identified in a pediatric patient
explanation: >-
Documents allelic heterogeneity with a homozygous nonsense STK4 variant
causing loss of function.
treatments:
- name: Immunoglobulin replacement therapy
description: >-
Immunoglobulin substitution (IVIG/SCIG) is a mainstay of treatment to manage
humoral immune deficiency.
treatment_term:
preferred_term: immunoglobulin infusion therapy
term:
id: NCIT:C62710
label: Immunoglobulin Therapy
target_mechanisms:
- target: Impaired naive T-cell survival
treatment_effect: MODULATES
description: >-
Immunoglobulin substitution does not correct the T-cell survival defect
itself but compensates for the downstream humoral immune deficiency that
results from impaired lymphocyte function.
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Immunoglobulins, antibacterial, and antiviral prophylaxis are the
mainstays of treatment.
explanation: >-
Immunoglobulin replacement is a mainstay that compensates for the
humoral consequences of the underlying lymphocyte defect.
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Immunoglobulins, antibacterial, and antiviral prophylaxis are the
mainstays of treatment.
explanation: Identifies immunoglobulin substitution as a mainstay of treatment.
- name: Antimicrobial prophylaxis
description: >-
Antibacterial and antiviral prophylaxis are mainstays of treatment to
prevent recurrent infections.
treatment_term:
preferred_term: antimicrobial agent therapy
term:
id: NCIT:C15986
label: Pharmacotherapy
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Immunoglobulins, antibacterial, and antiviral prophylaxis are the
mainstays of treatment.
explanation: Identifies antibacterial/antiviral prophylaxis as a mainstay of treatment.
- name: Hematopoietic stem cell transplantation
description: >-
Allogeneic HSCT is the potential definitive therapy aiming to restore the
immune system, though more data are needed to recommend it as a uniformly
safe therapy.
therapeutic_modality: CELL_THERAPY
treatment_term:
preferred_term: hematopoietic stem cell transplantation
term:
id: NCIT:C15431
label: Hematopoietic Cell Transplantation
target_mechanisms:
- target: Impaired naive T-cell survival
treatment_effect: RESTORES
description: >-
Allogeneic HSCT replaces the STK4-deficient hematopoietic system with
donor cells, restoring normal naive T-cell survival and broader immune
function.
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
State-of-the-art treatment regimens consist of prevention or treatment of
infections, immunoglobulin substitution (IVIG) and restoration of the
immune system by hematopoietic stem cell transplantation.
explanation: >-
HSCT restores the immune system by replacing the defective
hematopoietic compartment, correcting the underlying mechanisms.
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
State-of-the-art treatment regimens consist of prevention or treatment of
infections, immunoglobulin substitution (IVIG) and restoration of the
immune system by hematopoietic stem cell transplantation.
explanation: Identifies HSCT as the immune-restorative treatment for STK4 deficiency.
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
However, more data are needed to recommend hematopoietic stem cell
transplantation as a safe therapy.
explanation: >-
Notes the uncertainty around HSCT safety, qualifying its role as definitive
therapy.
- name: Immunomodulatory therapy
description: >-
Used for the inflammatory and autoimmune complications rather than for the immunodeficiency
itself. The cohort review presents this as a permissive option ("clinicians may use") rather
than a recommendation, and no specific agent or regimen is named in the cited source, so none
is curated here.
treatment_term:
preferred_term: immunomodulatory therapy
term:
id: NCIT:C15986
label: Pharmacotherapy
target_phenotypes:
- preferred_term: Autoimmunity
term:
id: HP:0002960
label: Autoimmunity
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Clinicians may use immunomodulatory therapies during inflammatory or autoimmune complications.
directness: INDIRECT
explanation: >-
Indirect: the source states this as a permissible option without naming an
agent, a regimen, or an outcome.
progression:
- phase: Symptom onset and diagnostic delay
age_range: Median 6 years 8 months at onset; median 7 years 5 months at diagnosis
notes: >-
STK4 deficiency is not typically a neonatal SCID presentation. In the nine-patient clinical
cohort the median age at symptom onset was 6 years 8 months and the median age at diagnosis 7
years 5 months, with both ranges extending past 20 years. The gap between the two medians is
short, so the delay in this disease is mostly in when it starts declaring itself rather than
in how long recognition then takes - but the upper end of the range is what matters for
ascertainment, since an adult presenting with CD4 lymphopenia, warts and lymphoma is a
recognised route to the diagnosis.
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
In the cohort, median age at symptom onset and age at diagnosis were 6 years 8 months (range, 6-248 months) and 7 years 5 months (range, 6-260 months), respectively.
explanation: Reports both medians and their ranges in the nine-patient cohort.
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
The patient had no relevant history of infectious disease during childhood other than mild wart-like lesion on the skin, but he developed diffuse large B-cell lymphoma (DLBCL) and EBV viremia with a low viral load in his thirties.
explanation: >-
A worked example of the late end of the range: an essentially unremarkable childhood
followed by lymphoma in the fourth decade.
- phase: Variable clinical penetrance
notes: >-
Recorded because it constrains how the rest of this entry should be read. Infectious-disease
penetrance varies substantially between patients with the same genetic defect, so the
phenotype frequencies curated here describe a reported case series rather than the expected
course of any individual patient.
evidence:
- reference: PMID:39110273
reference_title: "Epidermodysplasia Verruciformis and Vδ2 γδ T-cell Expansion in STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
The clinical penetrance of infectious diseases varies considerably among patients with inborn errors of immunity (IEI), even for identical genetic defects.
explanation: >-
States the variable-penetrance principle, offered by the authors as the frame for their own
STK4 case.
differential_diagnoses:
- name: Autosomal recessive hyper-IgE syndrome
description: >-
The cohort review names this as the crucial differential, because the two diseases share the
two features that most readily prompt the diagnosis: atopy and CD4 lymphopenia. Elevated IgE
is common in STK4 deficiency, so the immunoglobulin pattern does not separate them either.
distinguishing_features:
- Progressive T- and B-cell lymphopenia with intermittent neutropenia favours STK4 deficiency.
- Congenital heart defects such as atrial septal defect are reported in STK4 deficiency.
- EBV-driven lymphoproliferation and lymphoma are characteristic of STK4 deficiency.
- Identification of a biallelic loss-of-function STK4 variant is confirmatory.
disease_term:
preferred_term: autosomal recessive hyper-IgE syndrome
term:
id: MONDO:0018037
label: hyper-IgE syndrome
evidence:
- reference: PMID:34146746
reference_title: "Diversity in Serine/Threonine Protein Kinase-4 Deficiency and Review of the Literature."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
The differential diagnosis with autosomal recessive hyper-IgE syndrome is crucial. Because, atopy and CD4 lymphopenia are common in both diseases.
explanation: >-
The authors' own identification of the differential and of the two features that make it
difficult.
- name: Autoimmune lymphoproliferative syndrome
description: >-
STK4-deficient patients can present with a full ALPS-like picture - elevated double-negative T
cells, non-malignant lymphadenopathy, hepatosplenomegaly, haemolytic anaemia and
hypergammaglobulinaemia - and both patients in one report were initially given a clinical ALPS
diagnosis.
distinguishing_features:
- ALPS-associated FAS-pathway mutations were absent in the STK4-deficient patients.
- FAS-mediated apoptosis was intact, unlike in genuine ALPS.
- Recurrent infections and CD4 lymphopenia point away from ALPS toward a combined immunodeficiency.
disease_term:
preferred_term: autoimmune lymphoproliferative syndrome
term:
id: MONDO:0017979
label: autoimmune lymphoproliferative syndrome
evidence:
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
Also patient P1 presented with ALPS-like features (lymphadenopathy, elevated DNT cell number and increased Vitamin B12 levels) and both were initially clinically diagnosed as ALPS-like.
explanation: Documents the ALPS-like misdirection in two STK4-deficient patients.
- reference: PMID:30386345
reference_title: "EBV Negative Lymphoma and Autoimmune Lymphoproliferative Syndrome Like Phenotype Extend the Clinical Spectrum of Primary Immunodeficiency Caused by STK4 Deficiency."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: >-
None of the patients harbored typically ALPS-associated mutations of the Fas receptor mediated apoptotic pathway and Fas-mediated apoptosis was not affected.
explanation: The genetic and functional findings that exclude genuine ALPS.
References & Deep Research
Deep Research
1Deep research results are used as seeds for research; they do not undergo the same validation as the main records and may contain errors. How we use deep research.
Question: You are an expert researcher providing comprehensive, well-cited information.
Provide detailed information focusing on: 1. Key concepts and definitions with current understanding 2. Recent developments and latest research (prioritize 2023-2024 sources) 3. Current applications and real-world implementations 4. Expert opinions and analysis from authoritative sources 5. Relevant statistics and data from recent studies
Format as a comprehensive research report with proper citations. Include URLs and publication dates where available. Always prioritize recent, authoritative sources and provide specific citations for all major claims.
Disease Characteristics Research Template
Target Disease
- Disease Name: STK4 Deficiency
- MONDO ID: (if available)
- Category: Mendelian
Research Objectives
Please provide a comprehensive research report on STK4 Deficiency covering all of the disease characteristics listed below. This report will be used to populate a disease knowledge base entry. Be thorough and cite primary literature (PMID preferred) for all claims.
For each section, suggested databases/resources are listed. These are the first places you should search for information on each topic.
1. Disease Information
Search first: OMIM, Orphanet, ICD-10/ICD-11, MeSH, PubMed
- What is the disease? Provide a concise overview.
- What are the key identifiers? (OMIM, Orphanet, ICD-10/ICD-11, MeSH, Mondo)
- What are the common synonyms and alternative names?
- Is the information derived from individual patients (e.g., EHR) or aggregated disease-level resources?
2. Etiology
- Disease Causal Factors: What are the primary causes? (genetic, environmental, infectious, mechanistic)
- Risk Factors:
Search first: PubMed, Cochrane Library, UpToDate, clinical guidelines, ClinVar, ClinGen, GWAS Catalog, PheGenI, CTD, CDC, WHO, epidemiological databases
- Genetic risk factors (causal variants, susceptibility loci, modifier genes)
- Environmental risk factors (toxins, lifestyle, occupational exposures, age, sex, family history)
- Protective Factors:
Search first: PubMed, Cochrane Library, clinical trial databases, GWAS Catalog, gnomAD, WHO, CDC, nutrition databases
- Genetic protective factors (protective variants, modifier alleles)
- Environmental protective factors (diet, lifestyle, exposures that reduce risk)
- Gene-Environment Interactions: How do genetic and environmental factors interact to influence disease?
Search first: CTD, PubMed, PheGenI, GxE databases
3. Phenotypes
Search first: HPO (Human Phenotype Ontology), OMIM, Orphanet, PubMed, clinicaltrials.gov, MedDRA, SNOMED CT, DECIPHER, LOINC
For each phenotype, provide: - Phenotype type: symptoms, clinical signs, physical manifestations, behavioral changes, or laboratory abnormalities
For symptoms/signs: HPO, OMIM, Orphanet, PubMed For behavioral changes: HPO, DSM, RDoC (Research Domain Criteria), PubMed For laboratory abnormalities: LOINC, SNOMED CT, LabTests Online, PubMed - Phenotype characteristics: Search first: OMIM, Orphanet, HPO, PubMed - Age of symptom onset (neonatal, childhood, adult-onset, late-onset) - Symptom severity (mild, moderate, severe, variable) - Symptom progression (stable, progressive, episodic, fluctuating) - Frequency among affected individuals (percentage or qualitative) - Quality of life impact: Effects on daily functioning and well-being (per-phenotype when possible) Search first: EQ-5D database, SF-36, WHO QOL databases, PubMed - Suggest HPO (Human Phenotype Ontology) terms for each phenotype
4. Genetic/Molecular Information
- Causal Genes: Gene mutations or chromosomal abnormalities responsible for disease (gene symbols, OMIM IDs)
Search first: OMIM, ClinVar, HGMD, Ensembl, NCBI Gene
- Pathogenic Variants:
- Affected genes (gene symbols, HGNC IDs) > Search first: OMIM, NCBI Gene, Ensembl, HGNC, UniProt, GeneCards
- Variant classification (pathogenic, likely pathogenic, VUS per ACMG/AMP guidelines) > Search first: ClinVar, ClinGen, ACMG/AMP guidelines, VarSome
- Variant type/class (missense, frameshift, nonsense, splice-site, structural)
- Allele frequency in population databases > Search first: gnomAD, 1000 Genomes, ExAC, TOPMed, dbSNP
- Somatic vs germline origin > Search first: COSMIC (somatic), ClinVar, ICGC, TCGA
- Functional consequences (loss of function, gain of function, dominant negative)
- Modifier Genes: Genes that modify disease severity or expression
- Epigenetic Information: DNA methylation, histone modifications, chromatin changes affecting disease
Search first: ENCODE, Roadmap Epigenomics, MethBase, DiseaseMeth
- Chromosomal Abnormalities: Large-scale genetic changes (aneuploidy, translocations, inversions)
Search first: DECIPHER, ClinVar, ECARUCA, UCSC Genome Browser
5. Environmental Information
- Environmental Factors: Non-genetic contributing factors (toxins, radiation, pollution, occupational exposure)
Search first: CTD (Comparative Toxicogenomics Database), TOXNET, PubMed, EPA databases
- Lifestyle Factors: Behavioral factors (smoking, diet, exercise, alcohol consumption)
Search first: CDC databases, WHO, PubMed, NHANES
- Infectious Agents: If applicable, pathogens causing or triggering disease (bacteria, viruses, fungi, parasites)
Search first: NCBI Taxonomy, ViPR, BV-BRC, MicrobeDB, GIDEON
6. Mechanism / Pathophysiology
- Molecular Pathways: Specific signaling cascades or biochemical pathways involved (Wnt, MAPK, mTOR, PI3K-AKT, etc.)
Search first: KEGG, Reactome, WikiPathways, PathBank, BioCyc
- Cellular Processes: Cell-level mechanisms (apoptosis, autophagy, cell cycle dysregulation, inflammation, etc.)
Search first: Gene Ontology (GO), Reactome, KEGG, PubMed
- Protein Dysfunction: How protein structure or function is altered (misfolding, aggregation, loss of function, gain of function)
Search first: UniProt, PDB (Protein Data Bank), InterPro, Pfam, AlphaFold
- Metabolic Changes: Alterations in metabolic processes (energy metabolism, lipid metabolism, amino acid metabolism)
Search first: KEGG, BioCyc, HMDB (Human Metabolome Database), BRENDA
- Immune System Involvement: Role of immune response (autoimmunity, immunodeficiency, chronic inflammation)
Search first: ImmPort, Immunome Database, IEDB, Gene Ontology
- Tissue Damage Mechanisms: How tissues/ are injured (oxidative stress, ischemia, fibrosis, necrosis)
Search first: PubMed, Gene Ontology, Reactome
- Biochemical Abnormalities: Specific molecular defects (enzyme deficiencies, receptor dysfunction, ion channel defects)
Search first: BRENDA, UniProt, KEGG, OMIM, PubMed
- Epigenetic Changes: DNA methylation, histone modifications affecting gene expression in disease
Search first: ENCODE, Roadmap Epigenomics, MethBase, DiseaseMeth
- Molecular Profiling (if available):
- Transcriptomics/gene expression changes > Search first: GEO (Gene Expression Omnibus), ArrayExpress, GTEx, Human Cell Atlas, SRA
- Proteomics findings > Search first: PRIDE, ProteomeXchange, Human Protein Atlas, STRING, BioGRID
- Metabolomics signatures > Search first: MetaboLights, Metabolomics Workbench, HMDB, METLIN
- Lipidomics alterations > Search first: LIPID MAPS, SwissLipids, LipidHome, Metabolomics Workbench
- Genomic structural features > Search first: UCSC Genome Browser, Ensembl, NCBI, dbVar, DGV
- Advanced Technologies (if applicable):
- Single-cell analysis findings (cell-type specific mechanisms, cellular heterogeneity) > Search first: Human Cell Atlas, Single Cell Portal, GEO, CELLxGENE
- Spatial transcriptomics findings > Search first: GEO, Spatial Research, Vizgen, 10x Genomics data
- Multi-omics integration results > Search first: TCGA, ICGC, cBioPortal, LinkedOmics, PubMed
- Functional genomics screens (CRISPR, RNAi) > Search first: DepMap, GenomeRNAi, PubMed, BioGRID ORCS
For each mechanism, describe: - The causal chain from initial trigger to clinical manifestation - Which mechanisms are upstream vs downstream - What cell types and biological processes are involved - Suggest GO terms for biological processes and CL terms for cell types
7. Anatomical Structures Affected
- Organ Level:
- Primary organs directly affected
- Secondary organ involvement (complications, secondary effects)
- Body systems involved (cardiovascular, nervous, digestive, respiratory, endocrine, etc.)
Search first: Uberon, FMA (Foundational Model of Anatomy), OMIM, HPO, ICD-11, MeSH, SNOMED CT
- Tissue and Cell Level:
- Specific tissue types affected (epithelial, connective, muscle, nervous)
- Specific cell populations targeted (with Cell Ontology terms)
Search first: Uberon, Human Protein Atlas, Cell Ontology, Human Cell Atlas, CellMarker, PanglaoDB
- Subcellular Level:
- Cellular compartments involved (mitochondria, nucleus, ER, lysosomes) (with GO Cellular Component terms)
Search first: Gene Ontology (Cellular Component), UniProt, Human Protein Atlas
- Localization:
- Specific anatomical sites (with UBERON terms) > Search first: FMA, Uberon, NeuroNames (for brain), SNOMED CT
- Lateralization (unilateral, bilateral, asymmetric) > Search first: HPO, clinical literature, imaging databases
8. Temporal Development
- Onset:
- Typical age of onset (congenital, pediatric, adult, geriatric)
- Onset pattern (acute, subacute, chronic, insidious)
Search first: OMIM, Orphanet, HPO, PubMed
- Progression:
- Disease stages (early, intermediate, advanced, end-stage) > Search first: Cancer Staging Manual (AJCC), WHO classifications, PubMed
- Progression rate (rapid, slow, variable)
- Disease course pattern (episodic, relapsing-remitting, progressive, stable)
- Disease duration (self-limited, chronic lifelong)
Search first: Disease registries, longitudinal cohort databases, natural history studies, PubMed, Orphanet, OMIM
- Patterns:
- Remission patterns (spontaneous, treatment-induced) > Search first: Clinical trial databases, disease registries, PubMed
- Critical periods (time windows of vulnerability or opportunity for intervention) > Search first: PubMed, developmental biology databases, clinical guidelines
9. Inheritance and Population
- Epidemiology:
- Prevalence (cases per 100,000 at given time)
- Incidence (new cases per 100,000 per year)
Search first: Orphanet, CDC, WHO, GBD (Global Burden of Disease), national registries, SEER, disease registries
- For Genetic Etiology:
- Inheritance pattern (AD, AR, X-linked, mitochondrial, multifactorial, polygenic) > Search first: OMIM, Orphanet, ClinVar, GTR (Genetic Testing Registry)
- Penetrance (complete, incomplete, age-dependent) > Search first: ClinVar, OMIM, PubMed, ClinGen
- Expressivity (variable, consistent) > Search first: OMIM, ClinVar, PubMed
- Genetic anticipation (increasing severity in successive generations) > Search first: OMIM, PubMed (especially for repeat expansion disorders)
- Germline mosaicism > Search first: ClinVar, OMIM, genetic counseling literature, PubMed
- Founder effects (population-specific mutations) > Search first: gnomAD, population genetics databases, PubMed
- Consanguinity role > Search first: OMIM, population studies, genetic counseling resources
- Carrier frequency > Search first: gnomAD, carrier screening databases, GeneReviews, GTR
- Population Demographics:
- Affected populations (ethnic or demographic groups with higher prevalence) > Search first: gnomAD, 1000 Genomes, PAGE Study, PubMed, population registries
- Geographic distribution (endemic areas, regional variation) > Search first: WHO, CDC, GBD, Orphanet, geographic epidemiology databases
- Geographic distribution of specific variants
- Sex ratio (male:female) > Search first: Disease registries, OMIM, PubMed, epidemiological databases
- Age distribution of affected individuals > Search first: CDC, disease registries, SEER, Orphanet
10. Diagnostics
- Clinical Tests:
- Laboratory tests (blood, urine, tissue chemistry, specific enzyme assays) > Search first: LOINC, LabTests Online, PubMed
- Biomarkers (proteins, metabolites, genetic markers, circulating biomarkers) > Search first: FDA Biomarker List, BEST (Biomarkers, EndpointS, and other Tools), PubMed
- Imaging studies (X-ray, CT, MRI, PET, ultrasound) > Search first: RadLex, DICOM, Radiopaedia, imaging databases
- Functional tests (pulmonary function, cardiac stress tests) > Search first: LOINC, clinical guidelines, PubMed
- Electrophysiology (EEG, EMG, ECG, nerve conduction studies) > Search first: LOINC, clinical neurophysiology databases, PubMed
- Biopsy findings (histopathology, immunohistochemistry) > Search first: SNOMED CT, College of American Pathologists resources, PubMed
- Pathology findings (microscopic examination) > Search first: SNOMED CT, Digital Pathology databases, PubMed
- Genetic Testing:
Search first: GTR (Genetic Testing Registry), GeneReviews, ClinGen
- Overview of recommended genetic testing approach
- Whole genome sequencing (WGS) utility > Search first: GTR, ClinVar, GEL (Genomics England), gnomAD
- Whole exome sequencing (WES) utility > Search first: GTR, ClinVar, OMIM, GeneMatcher
- Gene panels (which panels, which genes) > Search first: GTR, ClinVar, laboratory-specific databases
- Single gene testing > Search first: GTR, ClinVar, OMIM, GeneReviews
- Chromosomal microarray (CMA) > Search first: DECIPHER, ClinVar, dbVar, ECARUCA
- Karyotyping > Search first: Chromosome Abnormality Database, ClinVar, cytogenetics resources
- FISH > Search first: ClinVar, cytogenetics databases, PubMed
- Mitochondrial DNA testing > Search first: MITOMAP, MSeqDR, ClinVar, GTR
- Repeat expansion testing > Search first: GTR, ClinVar, repeat expansion databases, PubMed
- Omics-Based Diagnostics (if applicable):
- RNA sequencing / transcriptomics > Search first: GEO, ArrayExpress, GTEx, RNA-seq databases
- Proteomics > Search first: PRIDE, ProteomeXchange, FDA Biomarker database
- Metabolomics > Search first: MetaboLights, Metabolomics Workbench, HMDB
- Epigenomics > Search first: GEO, ENCODE, Roadmap Epigenomics, MethBase
- Liquid biopsy > Search first: COSMIC, ClinVar, liquid biopsy databases, PubMed
- Clinical Criteria:
- Standardized diagnostic criteria (DSM, ICD, society guidelines) > Search first: DSM-5, ICD-11, clinical society guidelines, UpToDate
- Differential diagnosis (other conditions to rule out, with distinguishing features) > Search first: DynaMed, UpToDate, clinical decision support systems
- Screening:
- Screening methods for asymptomatic individuals (newborn screening, carrier screening, cascade screening) > Search first: ACMG recommendations, CDC newborn screening, GTR
11. Outcome/Prognosis
- Survival and Mortality:
- Survival rate (5-year, 10-year, overall) > Search first: SEER, cancer registries, disease-specific registries, PubMed
- Life expectancy (with and without treatment if applicable) > Search first: Orphanet, disease registries, actuarial databases, PubMed
- Mortality rate > Search first: CDC, WHO, GBD, national mortality databases
- Disease-specific mortality (deaths directly attributable to disease) > Search first: Disease registries, CDC Wonder, GBD, PubMed
- Morbidity and Function:
- Morbidity (disease-related disability and health impacts) > Search first: GBD, WHO, disability databases, PubMed
- Disability outcomes (long-term functional impairments) > Search first: ICF (International Classification of Functioning), disability registries
- Quality of life measures (EQ-5D, SF-36, PROMIS, disease-specific tools) > Search first: EQ-5D database, SF-36, PROMIS, PubMed
- Disease Course:
- Complications (secondary problems: infections, organ failure, etc.) > Search first: ICD codes, disease registries, clinical databases, PubMed
- Recovery potential (likelihood and extent of recovery, with vs without treatment) > Search first: Natural history studies, rehabilitation databases, PubMed
- Prediction:
- Prognostic factors (age, disease severity, biomarkers, treatment response) > Search first: Prognostic models databases, clinical calculators, PubMed
- Prognostic biomarkers (molecular markers predicting disease course) > Search first: FDA Biomarker database, PubMed, cancer prognostic databases
12. Treatment
- Pharmacotherapy:
- Pharmacological treatments (drug names, drug classes, mechanisms of action) > Search first: DrugBank, RxNorm, ATC classification, DailyMed, FDA databases
- Pharmacogenomics (how genetic variants affect drug metabolism, efficacy, toxicity) > Search first: PharmGKB, CPIC (Clinical Pharmacogenetics), FDA Table of PGx Biomarkers
- Advanced Therapeutics:
- Gene therapy (viral vectors, CRISPR, gene replacement, gene editing) > Search first: ClinicalTrials.gov, FDA gene therapy database, ASGCT resources
- Cell therapy (stem cell transplant, CAR-T, cellular therapeutics) > Search first: ClinicalTrials.gov, FDA cell therapy database, FACT standards
- RNA-based therapies (ASOs, siRNA, mRNA therapies) > Search first: ClinicalTrials.gov, FDA approvals, PubMed
- Targeted therapies (treatments directed at specific molecular targets) > Search first: My Cancer Genome, OncoKB, ClinicalTrials.gov, FDA approvals
- Immunotherapies (checkpoint inhibitors, monoclonal antibodies) > Search first: Cancer Immunotherapy Database, FDA approvals, ClinicalTrials.gov
- Surgical and Interventional:
- Surgical interventions (types of surgery, timing, outcomes) > Search first: CPT codes, surgical registries, clinical guidelines, PubMed
- Supportive and Rehabilitative:
- Supportive care (symptom management, pain control, nutrition) > Search first: Clinical guidelines, Cochrane Library, PubMed
- Rehabilitation (physical therapy, occupational therapy, speech therapy) > Search first: Rehabilitation medicine databases, clinical guidelines, PubMed
- Experimental:
- Experimental treatments in clinical trials (with NCT identifiers if available) > Search first: ClinicalTrials.gov, EU Clinical Trials Register, WHO ICTRP
- Treatment Outcomes:
- Treatment response rates > Search first: Clinical trial databases, FDA reviews, systematic reviews, PubMed
- Side effects and adverse events > Search first: FDA Adverse Event Reporting System (FAERS), MedWatch, PubMed
- Treatment Strategy:
- Treatment algorithms (clinical pathways, decision trees) > Search first: Clinical practice guidelines, NCCN Guidelines, UpToDate
- Combination therapies > Search first: ClinicalTrials.gov, treatment guidelines, PubMed
- Personalized medicine approaches (genotype-guided treatment) > Search first: My Cancer Genome, CIViC, PharmGKB, precision medicine databases
For each treatment, suggest MAXO (Medical Action Ontology) terms where applicable.
13. Prevention
- Prevention Levels:
- Primary prevention (preventing disease occurrence: vaccination, risk factor modification) > Search first: CDC, WHO, USPSTF recommendations, Cochrane Library
- Secondary prevention (early detection and treatment: screening programs, early intervention) > Search first: USPSTF, CDC screening guidelines, WHO
- Tertiary prevention (preventing complications in those with disease) > Search first: Clinical guidelines, disease management protocols, PubMed
- Immunization: Vaccine strategies (if applicable)
Search first: CDC vaccine schedules, WHO immunization, FDA vaccine database
- Screening and Early Detection:
- Screening programs (population-based: newborn screening, cancer screening) > Search first: CDC screening programs, USPSTF, cancer screening databases
- Genetic screening (carrier screening, preimplantation genetic diagnosis, prenatal testing) > Search first: ACMG recommendations, ACOG guidelines, GTR
- Risk stratification (identifying high-risk individuals for targeted prevention) > Search first: Risk prediction models, clinical calculators, PubMed
- Behavioral Interventions: Lifestyle modifications to reduce risk
Search first: CDC, WHO, behavioral intervention databases, Cochrane Library
- Counseling: Genetic counseling (risk assessment, family planning guidance)
Search first: NSGC resources, ACMG guidelines, GeneReviews
- Public Health:
- Public health interventions (sanitation, vector control, health education) > Search first: CDC, WHO, public health databases, PubMed
- Environmental interventions (reducing environmental risk factors) > Search first: EPA databases, WHO environmental health, PubMed
- Prophylaxis: Preventive medications or procedures
Search first: Clinical guidelines, FDA approvals, PubMed
14. Other Species / Natural Disease
- Taxonomy: Species affected (with NCBI Taxon identifiers)
Search first: NCBI Taxonomy
- Breed: Specific breeds affected (with VBO identifiers if applicable)
Search first: VBO (Vertebrate Breed Ontology)
- Gene: Orthologous genes in other species (with NCBI Gene IDs)
Search first: NCBI Gene
- Natural Disease:
- Naturally occurring disease in other species (companion animals, wildlife) > Search first: OMIA (Online Mendelian Inheritance in Animals), VetCompass, PubMed
- Veterinary relevance and importance in animal health > Search first: OMIA, veterinary databases, PubMed
- Comparative Biology:
- Comparative pathology (similarities and differences across species) > Search first: OMIA, comparative pathology databases, PubMed
- Evolutionary conservation of disease mechanisms > Search first: HomoloGene, OrthoMCL, Alliance of Genome Resources
- Transmission (if applicable):
- Zoonotic potential > Search first: CDC zoonotic diseases, WHO zoonoses, GIDEON
- Cross-species susceptibility > Search first: NCBI Taxonomy, veterinary databases, PubMed
15. Model Organisms
- Model Types:
- Model organism type (mammalian, invertebrate, cellular, in vitro) > Search first: Alliance of Genome Resources, model organism databases
- Specific model systems (mouse, rat, zebrafish, Drosophila, C. elegans, yeast, cell lines, organoids, iPSCs) > Search first: MGI, RGD, ZFIN, FlyBase, WormBase, SGD, ATCC, Cellosaurus
- Induced models (drug treatment, surgical intervention, environmental manipulation) > Search first: MGI, model organism databases, PubMed
- Genetic Models:
- Types available (knockout, knock-in, transgenic, conditional, humanized) > Search first: MGI, IMPC, KOMP, EuMMCR, IMSR
- Model Characteristics:
- Phenotype recapitulation (how well model reproduces human disease features) > Search first: Model organism databases, comparative studies, PubMed
- Model limitations (aspects of human disease not captured) > Search first: Model organism databases, PubMed, review articles
- Applications:
- Research applications (what aspects of disease can be studied) > Search first: Model organism databases, PubMed
- Resources:
- Model databases > Search first: MGI, RGD, ZFIN, FlyBase, WormBase, IMSR, EMMA, MMRRC
Citation Requirements
- Cite primary literature (PMID preferred) for all mechanistic and clinical claims
- Prioritize recent reviews and landmark papers
- Include direct quotes from abstracts where possible to support key statements
- Distinguish evidence source types: human clinical, model organism, in vitro, computational
Output Format
Structure your response as a comprehensive narrative organized by the sections above. For each section, provide: - Factual content with specific details (numbers, percentages, gene names, variant nomenclature) - Ontology term suggestions (HPO, GO, CL, UBERON, CHEBI, MAXO, MONDO) where applicable - Evidence citations with PMIDs - Direct quotes from abstracts to support key claims - Clear indication when information is not available or not applicable for this disease
This report will be used to populate a disease knowledge base entry with: - Pathophysiology descriptions with causal chains - Gene/protein annotations (HGNC, GO terms) - Phenotype associations (HP terms) with frequencies - Cell type involvement (CL terms) - Anatomical locations (UBERON terms) - Chemical entities (CHEBI terms) - Treatment annotations (MAXO terms) - Evidence items with PMIDs and exact abstract quotes - Epidemiology, prognosis, diagnostic, and prevention information - Animal model descriptions with phenotype recapitulation details
STK4 Deficiency (MST1 deficiency): Comprehensive Disease Characteristics Report
Executive summary
STK4 deficiency (also called MST1 deficiency) is a rare autosomal recessive combined immunodeficiency (CID) caused by biallelic loss-of-function variants in STK4 (encoding MST1, a Hippo-pathway kinase). It is characterized by profound CD4+ T-cell lymphopenia, impaired naïve T-cell homeostasis with increased apoptosis, intermittent neutropenia, variable dysgammaglobulinemia, recurrent bacterial/viral/fungal infections (notably EBV viremia and viral skin disease including HPV warts/epidermodysplasia verruciformis), and increased risk of lymphoproliferation/lymphoma, sometimes even EBV-negative. Recent 2024 case reports broaden the spectrum to adult-onset recognition with γδ T-cell expansion and atypically mild courses with residual/truncated STK4 protein. (abdollahpour2012thephenotypeof pages 1-2, schipp2018ebvnegativelymphoma pages 1-2, alsaud2024auniquestk4 pages 2-3, ying2024epidermodysplasiaverruciformisand pages 8-8)
Target Disease
- Disease Name: STK4 Deficiency
- Category: Mendelian / Inborn error of immunity (combined immunodeficiency)
- MONDO ID: MONDO:0013934 (“combined immunodeficiency due to STK4 deficiency”) (OpenTargets Search: STK4 deficiency,immunodeficiency due to STK4 deficiency,primary immunodeficiency STK4)
1. Disease information
Definition/overview
Human STK4 (MST1) deficiency is an autosomal recessive inborn error of immunity presenting as combined immunodeficiency with prominent CD4+ T-cell lymphopenia, susceptibility to infections (bacterial/viral/fungal), and complications including EBV-associated lymphoproliferation and lymphoma. (schipp2018ebvnegativelymphoma pages 1-2, radwan2020acaseof pages 1-2, guennoun2021anovelstk4 pages 1-3)
Key identifiers (retrieved)
A structured identifier summary is provided here: | Identifier/resource | Value | Supported name/synonym(s) | Evidence / URL | |---|---|---|---| | MONDO | MONDO:0013934 | combined immunodeficiency due to STK4 deficiency | OpenTargets disease-target association lists disease as “combined immunodeficiency due to STK4 deficiency” with MONDO_0013934 (OpenTargets Search: STK4 deficiency,immunodeficiency due to STK4 deficiency,primary immunodeficiency STK4) | | OMIM / MIM (gene) | STK4; MIM:604965 | STK4, serine threonine kinase 4; MST1 (protein/literature synonym) | Abdollahpour et al. explicitly give “STK4; MIM: 604965” (Blood 2012, DOI: https://doi.org/10.1182/blood-2011-09-378158) (abdollahpour2012thephenotypeof pages 1-2) | | Literature disease label | not a separate registry identifier in current evidence | STK4 deficiency | Used as article/disease label in “The phenotype of human STK4 deficiency” (Blood 2012, DOI: https://doi.org/10.1182/blood-2011-09-378158) and “STK4 deficiency impairs innate immunity and interferon production…” (J Clin Immunol 2021, DOI: https://doi.org/10.1007/s10875-020-00891-7) (abdollahpour2012thephenotypeof pages 1-2, jørgensen2021stk4deficiencyimpairs pages 1-2) | | Literature disease label | not a separate registry identifier in current evidence | MST1 deficiency | Used in literature as synonym, e.g., “autosomal recessive MST1 deficiency” / “MST1 (STK4) deficiency” (J Clin Immunol 2016, DOI: https://doi.org/10.1007/s10875-016-0232-2) (dang2016defectiveleukocyteadhesion pages 1-2) | | Literature disease label | aligns with MONDO label above | combined immunodeficiency due to STK4 deficiency | Supported by OpenTargets MONDO label and by multiple papers describing STK4 deficiency as an autosomal recessive combined immunodeficiency (OpenTargets Search: STK4 deficiency,immunodeficiency due to STK4 deficiency,primary immunodeficiency STK4, guennoun2021anovelstk4 pages 1-3, alsaud2024auniquestk4 pages 1-2) | | Key 2024 literature naming | case-report terminology | STK4 deficiency; STK4 (MST1) deficiency | Al-Saud 2024: Front Immunol, DOI: https://doi.org/10.3389/fimmu.2024.1329610; Ying 2024: J Clin Immunol, DOI: https://doi.org/10.1007/s10875-024-01780-z (alsaud2024auniquestk4 pages 1-2, ying2024epidermodysplasiaverruciformisand pages 8-8) | | ICD-10 | not retrieved in current evidence | — | not retrieved in current evidence | | ICD-11 | not retrieved in current evidence | — | not retrieved in current evidence | | MeSH | not retrieved in current evidence | — | not retrieved in current evidence | | Orphanet | not retrieved in current evidence | — | not retrieved in current evidence |
Table: This table compiles the disease identifiers and literature-supported names/synonyms for STK4 deficiency available in the currently gathered evidence. It distinguishes registry-backed identifiers from labels used in the clinical literature and flags vocabularies not yet retrieved.
Notes on missing identifiers: ICD-10/ICD-11, MeSH, and Orphanet identifiers were not present in the retrieved full texts used for evidence extraction, and are therefore not reported here (rather than inferred). (artifact-00)
Synonyms / alternative names
- STK4 deficiency (most common in clinical case literature) (abdollahpour2012thephenotypeof pages 1-2)
- MST1 deficiency / MST1 (STK4) deficiency (dang2016defectiveleukocyteadhesion pages 1-2)
- “Combined immunodeficiency due to STK4 deficiency” (MONDO label) (OpenTargets Search: STK4 deficiency,immunodeficiency due to STK4 deficiency,primary immunodeficiency STK4)
Evidence origin
The current knowledge summarized here is derived primarily from: - Aggregated peer-reviewed primary literature (case reports/series and mechanistic studies) (abdollahpour2012thephenotypeof pages 1-2, schipp2018ebvnegativelymphoma pages 1-2, radwan2020acaseof pages 1-2, dang2016defectiveleukocyteadhesion pages 1-2) - Disease-level aggregation in OpenTargets/MONDO mappings (OpenTargets Search: STK4 deficiency,immunodeficiency due to STK4 deficiency,primary immunodeficiency STK4)
2. Etiology
Disease causal factors
- Genetic: Biallelic (homozygous) loss-of-function variants in STK4 (MST1) cause autosomal recessive CID. Examples include nonsense, frameshift, splice, and large deletions. (abdollahpour2012thephenotypeof pages 1-2, schipp2018ebvnegativelymphoma pages 1-2, jørgensen2021stk4deficiencyimpairs pages 2-4, radwan2020acaseof pages 1-2)
- Mechanistic: Loss of MST1 disrupts immune cell survival, trafficking/adhesion, and antiviral interferon signaling, producing combined immunodeficiency and immune dysregulation. (dang2016defectiveleukocyteadhesion pages 1-2, jørgensen2021stk4deficiencyimpairs pages 1-2)
Risk factors
- Consanguinity is repeatedly noted in reported families and is consistent with autosomal recessive inheritance. (abdollahpour2012thephenotypeof pages 3-4, dang2016defectiveleukocyteadhesion pages 1-2, ying2024epidermodysplasiaverruciformisand pages 1-2)
Protective factors
No genetic/environmental protective factors were identified in the retrieved evidence.
Gene–environment interactions
A 2024 STK4-deficient EV case explicitly frames clinical variability as influenced by “pathogen exposure, healthcare access and host-environment interactions,” indicating penetrance is modulated by exposure context even for identical genetic defects. (ying2024epidermodysplasiaverruciformisand pages 1-2)
3. Phenotypes
A phenotype scaffold with suggested HPO mappings is provided here: | Phenotype category | Description | Typical onset/course in retrieved evidence | Suggested HPO term(s) | Key supporting citations | |---|---|---|---|---| | Recurrent infections | Recurrent bacterial and viral infections are a core feature of STK4 deficiency/combined immunodeficiency. Reported examples include recurrent otitis, chest infections, skin abscesses, urinary infections, severe gastroenteritis, pneumonias, VZV/herpes zoster, and cryptosporidiosis. Frequency: not quantified in retrieved sources. | Usually childhood onset; can persist chronically into adolescence/adulthood. | HP:0002719 Recurrent infections; HP:0011106 Recurrent respiratory infections; HP:0002027 Recurrent skin infections | (abdollahpour2012thephenotypeof pages 1-2, schipp2018ebvnegativelymphoma pages 1-2, schipp2018ebvnegativelymphoma pages 7-8, alsaud2024auniquestk4 pages 2-3, radwan2020acaseof pages 1-2, dang2016defectiveleukocyteadhesion pages 1-2, jørgensen2021stk4deficiencyimpairs pages 1-2) | | EBV viremia / EBV-associated disease | Persistent EBV viremia and EBV-associated lymphoproliferative disease are repeatedly reported; one 2024 paper notes nearly half of reported patients had EBV viremia. Frequency in the full literature is incompletely quantified in retrieved primary sources. | Often appears in childhood to adolescence; may be persistent/chronic. | HP:0031864 Epstein-Barr virus infection; HP:0012315 Viremia; HP:0002841 Recurrent viral infections | (schipp2018ebvnegativelymphoma pages 1-2, radwan2020acaseof pages 1-2, guennoun2021anovelstk4 pages 1-3, alsaud2024auniquestk4 pages 1-2) | | Lymphoma / lymphoproliferation | B-cell lymphoma, Hodgkin lymphoma, Burkitt lymphoma, and EBV-associated lymphoproliferation have been reported; lymphoma may occur even without detectable EBV. Frequency: not quantified in retrieved sources. | Childhood or adolescence in reported cases; severe, progressive complication. | HP:0002664 Neoplasm; HP:0100753 B-cell lymphoma; HP:0002830 Recurrent lymphoma | (schipp2018ebvnegativelymphoma pages 1-2, schipp2018ebvnegativelymphoma pages 7-8, radwan2020acaseof pages 1-2) | | Warts / HPV disease | Cutaneous warts are common in case reports; HPV types 57 and 84 were documented in an early family, and EV/HPV susceptibility is part of the phenotype spectrum. One 2024 case specifically reported epidermodysplasia verruciformis due to HPV38. Frequency: not quantified in retrieved sources. | Often begins in childhood; can be chronic/persistent. | HP:0001923 Cutaneous warts; HP:0200058 Epidermodysplasia verruciformis; HP:0012372 Viral skin infection | (abdollahpour2012thephenotypeof pages 3-4, alsaud2024auniquestk4 pages 2-3, ying2024epidermodysplasiaverruciformisand pages 8-8) | | Mucocutaneous candidiasis / oral thrush | Recurrent mucocutaneous candidiasis, oral thrush, and related fungal mucosal infections are recurrently described. Frequency: not quantified in retrieved sources. | Childhood onset; often recurrent. | HP:0002721 Chronic mucocutaneous candidiasis; HP:0000175 Oral candidiasis | (abdollahpour2012thephenotypeof pages 1-2, abdollahpour2012thephenotypeof pages 3-4, alsaud2024auniquestk4 pages 2-3, radwan2020acaseof pages 1-2) | | Tuberculosis / mycobacterial-like infection | Pulmonary tuberculosis, granulomatous lymphadenopathy evoking mycobacterial infection, and prolonged anti-TB therapy have been reported in individual patients. Frequency: not quantified in retrieved sources. | Childhood to adolescence; may be prolonged/relapsing. | HP:0032264 Tuberculosis; HP:0002840 Increased susceptibility to mycobacterial infection; HP:0002716 Lymphadenopathy | (guennoun2021stk4deficiencyunderlies pages 15-19, radwan2020acaseof pages 1-2, guennoun2021anovelstk4 pages 1-3) | | Autoimmunity / ALPS-like phenotype | Autoimmune hemolytic anemia, thrombocytopenia, polyarthritis, lymphadenopathy, hepatosplenomegaly, elevated double-negative T cells, and ALPS-like presentations extend the phenotype. Fas-mediated apoptosis was reportedly intact. Frequency: not quantified in retrieved sources. | Childhood to adolescence; variable, relapsing or persistent immune dysregulation. | HP:0001890 Autoimmune hemolytic anemia; HP:0001744 Splenomegaly; HP:0002716 Lymphadenopathy; HP:0001945 Fever; HP:0012649 Autoimmunity | (schipp2018ebvnegativelymphoma pages 1-2, schipp2018ebvnegativelymphoma pages 7-8) | | Cardiac defects | Structural cardiac anomalies are reported, including atrial septal defect, patent foramen ovale, valvular insufficiency, and pulmonary valve stenosis. Frequency: not quantified in retrieved sources. | Congenital/childhood-recognized; generally non-progressive structural findings. | HP:0001631 Atrial septal defect; HP:0001653 Patent foramen ovale; HP:0001642 Pulmonary valve stenosis | (abdollahpour2012thephenotypeof pages 1-2, abdollahpour2012thephenotypeof pages 3-4, schipp2018ebvnegativelymphoma pages 7-8, alsaud2024auniquestk4 pages 1-2) | | Hypothyroidism / short stature | One STK4-deficient child had hypothyroidism and short stature as part of the broader syndromic presentation. Frequency: not quantified in retrieved sources. | Childhood; chronic. | HP:0000821 Hypothyroidism; HP:0004322 Short stature | (jørgensen2021stk4deficiencyimpairs pages 1-2) | | CD4 lymphopenia | Profound CD4+ T-cell lymphopenia is among the most consistent laboratory hallmarks; values in retrieved reports include very low absolute CD4 counts and reduced naive CD4 subsets. | Usually detected in childhood; chronic/persistent. | HP:0005403 CD4 lymphocytopenia; HP:0011839 Abnormality of T cell count | (abdollahpour2012thephenotypeof pages 1-2, schipp2018ebvnegativelymphoma pages 1-2, schipp2018ebvnegativelymphoma pages 7-8, radwan2020acaseof pages 1-2, guennoun2021stk4deficiencyunderlies pages 15-19, dang2016defectiveleukocyteadhesion pages 1-2) | | T- and B-cell lymphopenia | Combined T- and B-cell lymphopenia is frequently described, though severity is variable and some cases retain a near-normal CD19+ fraction. Frequency: not quantified in retrieved sources. | Childhood onset; chronic. | HP:0001888 Lymphopenia; HP:0005404 B lymphocytopenia; HP:0011839 Abnormality of T cell count | (abdollahpour2012thephenotypeof pages 1-2, abdollahpour2012thephenotypeof pages 3-4, alsaud2024auniquestk4 pages 2-3, guennoun2021stk4deficiencyunderlies pages 15-19, guennoun2021anovelstk4 pages 1-3) | | Dysgammaglobulinemia | Immunoglobulin abnormalities are variable, including hypergammaglobulinemia, low IgG2/poor vaccine responses, elevated IgM, hypogammaglobulinemia, or dysregulated immunoglobulin levels. Frequency: not quantified in retrieved sources. | Variable across childhood/adolescence; chronic. | HP:0004313 Decreased circulating IgG level; HP:0010783 Elevated circulating IgM level; HP:0010701 Abnormality of immune system physiology | (schipp2018ebvnegativelymphoma pages 1-2, schipp2018ebvnegativelymphoma pages 7-8, alsaud2024auniquestk4 pages 2-3, dang2016defectiveleukocyteadhesion pages 1-2, jørgensen2021stk4deficiencyimpairs pages 1-2) | | Neutropenia | Intermittent or persistent neutropenia is repeatedly reported; sometimes accompanied by apparently normal marrow maturation. Frequency: not quantified in retrieved sources. | Usually childhood onset; intermittent/fluctuating in several reports. | HP:0001875 Neutropenia; HP:0001889 Frequent infections | (abdollahpour2012thephenotypeof pages 1-2, abdollahpour2012thephenotypeof pages 3-4, alsaud2024auniquestk4 pages 2-3, radwan2020acaseof pages 1-2) | | Double-negative T-cell expansion / ALPS-like immunophenotype | Elevated TCRαβ+ CD4-CD8- double-negative T cells were reported in ALPS-like patients. Frequency: not quantified in retrieved sources. | Childhood/adolescent presentation; persistent in reported cases. | HP:0033079 Increased double negative T cells; HP:0012649 Autoimmunity | (schipp2018ebvnegativelymphoma pages 1-2, schipp2018ebvnegativelymphoma pages 7-8) | | γδ T-cell expansion | Expanded γδ T-cell populations, including Vδ2+ γδ T-cell predominance, have been described and may represent a compensatory antiviral response. One 2024 report states γδ T-cell expansion has frequently been observed among 33 reported cases. | Can be recognized in adulthood as well as earlier disease; chronic. | HP:0011832 Abnormal lymphocyte physiology; HP:0011839 Abnormality of T cell count | (ying2024epidermodysplasiaverruciformisand pages 8-8) | | Naive T-cell depletion / increased apoptosis | Beyond numeric lymphopenia, patients show marked loss of naïve T cells with increased apoptosis and defective T-cell survival. Frequency: not quantified in retrieved sources. | Chronic immunologic abnormality from childhood onward. | HP:0011839 Abnormality of T cell count; HP:0030783 Increased lymphocyte apoptosis | (guennoun2021stk4deficiencyunderlies pages 15-19, dang2016defectiveleukocyteadhesion pages 1-2, guennoun2021anovelstk4 pages 1-3) | | Defective leukocyte adhesion / chemotaxis | Functional phenotype includes impaired chemotaxis and adhesion (e.g., deficient CXCL11 responses, impaired ICAM-1/LFA-1 binding), relevant to host defense and trafficking. Frequency: not quantified in retrieved sources. | Chronic cellular defect; detected on functional testing rather than routine clinical exam. | HP:0012640 Abnormal leukocyte chemotaxis; HP:0011893 Abnormal leukocyte function | (dang2016defectiveleukocyteadhesion pages 1-2, guennoun2021anovelstk4 pages 1-3) |
Table: This table summarizes the major clinical and laboratory phenotypes reported for STK4 deficiency, along with likely HPO mappings and supporting citations from the retrieved evidence. It is useful as a KB-ready phenotype scaffold when frequencies are incompletely quantified in the available primary reports.
Hallmark phenotypes (high-confidence)
- CD4+ T-cell lymphopenia (often profound) with reduction of naïve subsets (abdollahpour2012thephenotypeof pages 4-6, dang2016defectiveleukocyteadhesion pages 1-2)
- Recurrent infections: bacterial/viral/fungal; respiratory infections and skin infections common (abdollahpour2012thephenotypeof pages 1-2, alsaud2024auniquestk4 pages 2-3)
- Viral susceptibility, including EBV viremia/LPD and viral skin disease (warts/EV) (schipp2018ebvnegativelymphoma pages 1-2, ying2024epidermodysplasiaverruciformisand pages 1-2)
- Intermittent neutropenia in multiple reports (abdollahpour2012thephenotypeof pages 3-4, radwan2020acaseof pages 1-2)
- Lymphoma predisposition including EBV-negative lymphoma (schipp2018ebvnegativelymphoma pages 1-2, schipp2018ebvnegativelymphoma pages 2-3)
Quantitative examples / statistics from recent studies
- Double-negative T-cell predominance: A 2024 adult case had predominantly double-negative T cells (67.4%), identified as Vδ2+ γδ T cells. (ying2024epidermodysplasiaverruciformisand pages 1-2)
- Case count note: The same 2024 report states “γδ T-cell expansion has frequently been observed in the 33 reported cases with STK4 deficiency.” (ying2024epidermodysplasiaverruciformisand pages 1-2)
- EBV proportion estimate (secondary within a primary paper): A 2024 case report states “nearly half of the patients” exhibit EBV viremia, reflecting the authors’ synthesis of published cases (not a de novo cohort analysis). (alsaud2024auniquestk4 pages 1-2)
Quality of life impact
Direct QoL instrument data (e.g., SF-36/EQ-5D) were not identified in the retrieved sources. Clinically, recurrent infections, chronic viral skin disease, and malignancy risk imply significant morbidity and healthcare utilization. (radwan2020acaseof pages 1-2, ying2024epidermodysplasiaverruciformisand pages 1-2)
4. Genetic / molecular information
Causal gene
- STK4 (MST1), OMIM/MIM 604965 (gene identifier explicitly present in Blood 2012) (abdollahpour2012thephenotypeof pages 1-2)
Pathogenic variants (examples from retrieved primary literature)
Representative variants reported: - c.G750A, p.W250X (homozygous stop) in a consanguineous family (Blood 2012) (abdollahpour2012thephenotypeof pages 4-6) - c.442C>T, p.Arg148Stop (homozygous nonsense) (Dang 2016) (dang2016defectiveleukocyteadhesion pages 1-2) - c.1103delT, p.M368RfsX2 (frameshift) and c.525+2T>G (splice donor) (Schipp 2018) (schipp2018ebvnegativelymphoma pages 1-2) - Large deletion involving exons 4–8 (Radwan 2020) (radwan2020acaseof pages 1-2) - c.871C>T, p.Arg291 (homozygous nonsense) (Guennoun 2021) (guennoun2021anovelstk4 pages 1-3) - c.523dupA, p.(L174fsTer45) (homozygous frameshift) (Jørgensen 2021) (jørgensen2021stk4deficiencyimpairs pages 1-2) - p.Trp425X* (biallelic stop-gain; adult EV/γδ T-cell expansion case) (Ying 2024) (ying2024epidermodysplasiaverruciformisand pages 1-2)
A KB-ready tabular summary of genetics/diagnostics/treatments across key reports is provided here: | Study (year) | Patient Count | Variant(s) (cDNA/protein) | Diagnostic Method(s) | Key Labs (CD4/T/B/NK, Ig) | Key Infections/Complications | Treatments (IVIG, prophylaxis, HSCT, chemo/rituximab) | Outcomes | |---|---|---|---|---|---|---|---| | Abdollahpour et al. (2012) (abdollahpour2012thephenotypeof pages 1-2, abdollahpour2012thephenotypeof pages 3-4) | 3 | c.G750A, p.W250X | Gene sequencing, SNP homozygosity mapping, Western blot | Profound CD4+, T, and B lymphopenia; high IgE, IgG, IgA; low IgM; neutropenia | Recurrent bacterial/viral infections, skin abscesses, mucocutaneous candidiasis, cutaneous warts (HPV57/84), EBV lymphadenopathy, ASD | NR | NR | | Dang et al. (2016) (dang2016defectiveleukocyteadhesion pages 1-2) | 3 | c.442C>T, p.Arg148Stop | WES, linkage analysis, Sanger sequencing, Western blot | Profound CD4 lymphopenia, absent naive T cells, hypergammaglobulinemia, low IgG2 | Recurrent infections, cryptosporidiosis, EBV-LPD | Rituximab, steroids, HSCT | 1 died from HSCT complications, 1 fatal CMV immune dysregulation, 1 good HSCT outcome | | Schipp et al. (2018) (schipp2018ebvnegativelymphoma pages 1-2) | 2 | c.1103delT (p.M368RfsX2); c.525+2T>G | Targeted exome enrichment, WES, Sanger, qRT-PCR, Western blot | Profound CD4 lymphopenia, elevated DNT cells, variable Ig (low IgG, high IgM/IgA) | Recurrent infections, EBV-negative B-cell and Hodgkin lymphoma, ALPS-like phenotype, active EBV, pulmonary valve stenosis | NHL-BFM 04 chemo, IVIG, steroids, rituximab, HSCT | P1 achieved complete lymphoma remission | | Radwan et al. (2020) (radwan2020acaseof pages 1-2) | 1 | Large deletion (exons 4-8) | Targeted NGS panel | Profound CD4 lymphopenia (0.26x10^9/L), high IgE (800 IU/L) | Recurrent chest infections, persistent EBV viremia, mycobacterial-like caseous granuloma, Burkitt's lymphoma | Anti-TB therapy, monthly IVIG, LMB chemotherapy | Died (chemo failed to control lymphoma) | | Guennoun et al. (2021) (guennoun2021stk4deficiencyunderlies pages 15-19) | 1 | c.871C>T, p.Arg291* | WGS, Sanger, qRT-PCR, Western blot, PhIP-Seq, flow cytometry | Selective CD4+ lymphopenia, reduced naive T cells, normal B and NK counts, expanded CD56bright NK | Recurrent skin/chest infections, bronchiectasis, pulmonary TB, persistent EBV viremia, intermittent neutropenia | Prolonged anti-TB drugs, asthma therapy | Persistent EBV viremia, recurrent hospitalizations | | Jørgensen et al. (2021) (jørgensen2021stk4deficiencyimpairs pages 1-2, jørgensen2021stk4deficiencyimpairs pages 2-4) | 1 | c.523dupA, p.(L174fsTer45) | Targeted NGS panel, Sanger, Western blot, RT-qPCR | Profound CD4 lymphopenia, reduced switched B cells, hyperglobulinemia, intermittent neutropenia | Severe herpes zoster, chronic warts, recurrent pneumonias, hypothyroidism, short stature | Ig substitution (IVIG) | Surviving (HSCT not planned) | | Al-Saud et al. (2024) (alsaud2024auniquestk4 pages 2-3, alsaud2024auniquestk4 pages 1-2) | 1 | Novel truncation of C-terminal SARAH domain | NGS, flow cytometry | Severe T cell lymphopenia (<500/mm3), low B cells, normal NK cells, high IgM, normal IgG/IgA | Recurrent infections (otitis, UTI, oral thrush), severe gastroenteritis | IVIG (0.4 g/kg/4 weeks), prophylactic antibiotics and antifungals | Surviving well (mild clinical phenotype) | | Ying et al. (2024) (ying2024epidermodysplasiaverruciformisand pages 8-8, ying2024epidermodysplasiaverruciformisand pages 1-2) | 1 | p.Trp425X | Exome sequencing, Sanger, flow cytometry | CD4+ T-cell lymphopenia, 67.4% DNT cells (Vδ2+ γδ T cells) | Epidermodysplasia verruciformis (HPV38), DLBCL, EBV viremia | NR | NR |
Table: A summary of STK4 deficiency patient cases from the retrieved literature, outlining key genetic variants, diagnostic methods, immunologic lab results, clinical complications, and treatments.
Functional consequence (current understanding)
Most reported variants are predicted/observed to cause loss of MST1 protein (e.g., nonsense variants with absent protein on Western blot) or truncation that disrupts key domains. (dang2016defectiveleukocyteadhesion pages 1-2, abdollahpour2012thephenotypeof pages 4-6)
Modifier genes / epigenetics / chromosomal abnormalities
No modifier genes, disease-specific epigenetic signatures, or recurrent chromosomal abnormalities were identified in retrieved evidence.
5. Environmental information
Infectious exposures as key non-genetic determinants
The phenotype is heavily shaped by infectious exposures, including: - EBV viremia/LPD and lymphoma (schipp2018ebvnegativelymphoma pages 1-2, radwan2020acaseof pages 1-2) - HPV-associated warts and EV (abdollahpour2012thephenotypeof pages 3-4, ying2024epidermodysplasiaverruciformisand pages 1-2) - Tuberculosis/mycobacterial-like pathology in some cases (radwan2020acaseof pages 1-2, guennoun2021anovelstk4 pages 1-3)
No toxin, radiation, or lifestyle risk factors were identified in retrieved evidence.
6. Mechanism / pathophysiology
Core causal chain (integrated)
1) Biallelic STK4 loss-of-function → reduced/absent MST1 kinase activity (dang2016defectiveleukocyteadhesion pages 1-2) 2) Impaired lymphocyte survival and homeostasis (loss of naïve T cells; apoptosis susceptibility; FOXO/IL-7R/BCL2 axis disruption) → CD4-predominant lymphopenia (abdollahpour2012thephenotypeof pages 4-6, jørgensen2021stk4deficiencyimpairs pages 1-2) 3) Defective leukocyte trafficking and immune synapse/adhesion (LFA-1 affinity/ICAM-1 binding; chemotaxis) → ineffective immune surveillance and responses (dang2016defectiveleukocyteadhesion pages 1-2) 4) Impaired innate antiviral signaling, including reduced TBK1/IRF3 phosphorylation → deficient type I/II/III interferon responses → viral susceptibility (including herpesviruses) (jørgensen2021stk4deficiencyimpairs pages 1-2) 5) Downstream clinical outcomes: recurrent infections, chronic viral skin disease, EBV-associated lymphoproliferation and lymphoma; variable immune dysregulation/autoimmunity. (schipp2018ebvnegativelymphoma pages 1-2, radwan2020acaseof pages 1-2)
Key pathways and molecular processes (with ontology suggestions)
1) Hippo signaling (canonical vs non-canonical) - Canonical Hippo axis: MST1/2 → LATS1/2 → YAP/TAZ; however, immune phenotypes often reflect non-canonical Hippo signaling in immune cells. (ueda2020mst12balanceimmune pages 1-2, louis2024thehippokinases pages 1-2) - GO suggestions: - GO:0035329 hippo signaling - GO:0008285 negative regulation of cell proliferation
2) T-cell survival/apoptosis and FOXO axis - STK4 deficiency is associated with impaired T-cell immunity and increased apoptosis; one mechanistic paper lists reduced expression of Foxo1, IL-7R, and BCL2 with increased apoptosis susceptibility. (jørgensen2021stk4deficiencyimpairs pages 1-2) - Blood 2012 provides functional evidence of increased apoptosis susceptibility and mitochondrial membrane potential loss in patient T cells and neutrophils, and decreased FOXO3 expression in PBMCs. (abdollahpour2012thephenotypeof pages 4-6) - GO suggestions: GO:0006915 apoptotic process; GO:0042981 regulation of apoptotic process
3) Leukocyte adhesion/migration (integrins; chemotaxis) - Human MST1 deficiency shows impaired ICAM-1 adhesion under flow and reduced chemotaxis to CXCL11 despite preserved CXCR3, supporting a trafficking defect. (dang2016defectiveleukocyteadhesion pages 1-2) - GO suggestions: GO:0050900 leukocyte migration; GO:0030595 leukocyte chemotaxis
4) Interferon signaling (TBK1–IRF3) - STK4 deficiency can cause “significantly impaired type I, II, and III interferon responses” tied to reduced TBK1/IRF3 phosphorylation. (jørgensen2021stk4deficiencyimpairs pages 1-2) - GO suggestions: GO:0035455 response to interferon-alpha; GO:0060337 type I interferon signaling pathway
5) Innate immunity / macrophage antibacterial restriction (2024 development) - A 2024 mBio study generated Mst1/2 knockout macrophages and reports cytokine changes (TNFα, CXCL10, IL-1ra), non-canonical inflammatory Hippo signaling independent of LATS1/2 inhibition, and restriction of infection by Legionella, E. coli, and Pseudomonas. (louis2024thehippokinases pages 1-2) - GO suggestions: GO:0006955 immune response; GO:0009615 response to virus; GO:0042742 defense response to bacterium
Cell types involved (CL suggestions)
- T cells: CL:0000084 (T cell), CL:0000624 (CD4-positive, alpha-beta T cell)
- γδ T cells noted in 2024 adult case: CL:0000798 (gamma-delta T cell) (ying2024epidermodysplasiaverruciformisand pages 1-2)
- Macrophages: CL:0000235 (macrophage) (louis2024thehippokinases pages 1-2)
7. Anatomical structures affected
Based on clinical reports: - Immune system / hematolymphoid tissues: lymph nodes, blood immune compartments (lymphopenia, lymphadenopathy/LPD) (abdollahpour2012thephenotypeof pages 4-6) - Skin: warts/EV lesions (ying2024epidermodysplasiaverruciformisand pages 1-2) - Lung/respiratory tract: recurrent pneumonias/bronchiectasis (guennoun2021stk4deficiencyunderlies pages 15-19) - Heart: atrial septal defect / pulmonary valve stenosis reported in some patients (abdollahpour2012thephenotypeof pages 4-6, schipp2018ebvnegativelymphoma pages 2-3)
UBERON suggestions: - UBERON:0002405 immune system - UBERON:0002048 lung - UBERON:0002097 skin - UBERON:0000948 heart
8. Temporal development
- Onset: commonly in childhood with recurrent infections and lymphopenia (abdollahpour2012thephenotypeof pages 1-2, radwan2020acaseof pages 1-2); however, 2024 data show adult recognition with relatively mild childhood infection history but later lymphoma/EV (ying2024epidermodysplasiaverruciformisand pages 1-2).
- Course: chronic immunodeficiency with episodic infections; risk of progressive complications (EBV viremia, lymphoma). (schipp2018ebvnegativelymphoma pages 1-2, radwan2020acaseof pages 1-2)
9. Inheritance and population
Inheritance
- Autosomal recessive inheritance is repeatedly documented, commonly in consanguineous families. (abdollahpour2012thephenotypeof pages 3-4, dang2016defectiveleukocyteadhesion pages 1-2, ying2024epidermodysplasiaverruciformisand pages 1-2)
Epidemiology
Prevalence/incidence and carrier frequency were not quantified in the retrieved evidence and should be populated from Orphanet/registry sources in a subsequent pass (not inferred here).
10. Diagnostics
Clinical tests / immune phenotyping
Common diagnostic findings include: - Profound CD4 lymphopenia and reduced naïve T-cell subsets; variable B-cell defects and dysgammaglobulinemia; intermittent neutropenia. (abdollahpour2012thephenotypeof pages 4-6, jørgensen2021stk4deficiencyimpairs pages 2-4) - Functional immunology (chemotaxis/adhesion assays) can reveal trafficking defects (ICAM-1 adhesion under flow; CXCL11 chemotaxis). (dang2016defectiveleukocyteadhesion pages 1-2)
Genetic testing approaches in primary reports
- WES: used in Dang 2016 and Ying 2024. (dang2016defectiveleukocyteadhesion pages 1-2, ying2024epidermodysplasiaverruciformisand pages 1-2)
- WGS with Sanger confirmation: Guennoun 2021. (guennoun2021stk4deficiencyunderlies pages 15-19)
- Targeted NGS PID gene panels: Jørgensen 2021; Radwan 2020. (jørgensen2021stk4deficiencyimpairs pages 2-4, radwan2020acaseof pages 1-2)
- Protein expression by Western blot/immunoblotting to confirm loss of MST1 protein in null variants. (dang2016defectiveleukocyteadhesion pages 1-2, guennoun2021stk4deficiencyunderlies pages 15-19)
Differential diagnosis (examples explicitly mentioned)
- DOCK8 deficiency (phenotypic overlap, including high IgE features; STK4 considered in this context) (radwan2020acaseof pages 1-2)
- WHIM/CXCR4, G6PC3 deficiency, ELANE/HAX1 congenital neutropenia were genetically excluded in a Blood 2012 workup. (abdollahpour2012thephenotypeof pages 4-6)
- ALPS-like presentations and other EBV/LPD-associated IEIs (e.g., ITK, MAGT1, SAP/XIAP, CD27) discussed in Schipp 2018. (schipp2018ebvnegativelymphoma pages 2-3)
11. Outcome / prognosis
- Prognosis is heterogeneous: some patients survive with supportive therapy; others develop severe malignancy or infection-related complications.
- HSCT outcomes are variable, including transplant-related mortality and post-transplant immune dysregulation in the Dang 2016 cohort. (dang2016defectiveleukocyteadhesion pages 1-2)
- Fatal lymphoma outcome occurred in an Egyptian child despite chemotherapy, in whom HSCT was postponed due to donor unavailability and transient clinical improvement on IVIG. (radwan2020acaseof pages 1-2)
Quantitative survival rates were not available in retrieved evidence.
12. Treatment
Current applications / real-world implementations (from case literature)
Supportive and definitive treatments reported include: - Immunoglobulin replacement (IVIG): commonly used; one 2024 case specifies 0.4 g/kg every 4 weeks plus antibacterial prophylaxis with good clinical status. (alsaud2024auniquestk4 pages 2-3) - Antimicrobial therapy / prophylaxis: prolonged anti-tuberculosis regimens and prophylactic antibacterial treatment are reported. (guennoun2021stk4deficiencyunderlies pages 15-19, alsaud2024auniquestk4 pages 2-3) - Rituximab and steroids for EBV-associated lymphoproliferation (Dang 2016). (dang2016defectiveleukocyteadhesion pages 1-2) - Chemotherapy for lymphoma (e.g., NHL-BFM 04 protocol; LMB chemotherapy listed in one fatal Burkitt lymphoma case). (schipp2018ebvnegativelymphoma pages 2-3, radwan2020acaseof pages 1-2) - HSCT: used as immune reconstitution in some cases, with variable outcomes. (dang2016defectiveleukocyteadhesion pages 1-2)
MAXO suggestions (non-exhaustive)
- MAXO:0000761 Immunoglobulin replacement therapy
- MAXO:0000061 Antibiotic therapy
- MAXO:0000062 Antifungal therapy
- MAXO:0001020 Hematopoietic stem cell transplantation
- MAXO:0000647 Chemotherapy
- MAXO:0000102 Anti-CD20 monoclonal antibody therapy (rituximab)
Clinical trials
A targeted clinical trial program specific to STK4 deficiency was not identified in the retrieved ClinicalTrials search results in this run.
13. Prevention
No disease-specific primary prevention exists for a Mendelian CID. Preventive practice is largely tertiary prevention: - infection prophylaxis and early treatment - immunoglobulin replacement - vaccination strategy individualized to immune competence (not detailed in retrieved sources) - malignancy vigilance (EBV monitoring; lymphoma surveillance) (schipp2018ebvnegativelymphoma pages 1-2, radwan2020acaseof pages 1-2)
14. Other species / natural disease
No naturally occurring veterinary STK4 deficiency syndrome was identified in retrieved evidence.
15. Model organisms
Multiple sources note that mouse Mst1/Mst1/2 deficiency models recapitulate immune phenotypes (lymphopenia, trafficking defects, altered apoptosis), and 2024 data extend MST1/2 function to macrophage antibacterial defense and conserved roles in amoebae. (ueda2020mst12balanceimmune pages 1-2, louis2024thehippokinases pages 1-2, bouchard2020hipposignaltransduction pages 4-6)
Recent developments (2023–2024 prioritized)
1) Adult presentation and EV with HPV38 + γδ T-cell compensation: A 2024 J Clin Immunol report describes EV due to HPV38, adult-onset lymphoma/EBV viremia, and a striking Vδ2+ γδ T-cell expansion (67.4% DNT cells), proposing γδ expansion as compensatory antiviral protection. (ying2024epidermodysplasiaverruciformisand pages 1-2) 2) Milder phenotype from SARAH-domain truncation escaping NMD: A 2024 Frontiers in Immunology case emphasizes that some downstream truncations evade nonsense-mediated decay, producing a truncated protein and a relatively mild clinical course despite severe lymphopenia. (alsaud2024auniquestk4 pages 1-2) 3) Innate immunity and non-canonical Hippo signaling in macrophages (2024 mBio): Knockout studies show MST1/2 regulate macrophage gene programs and cytokine release independently of canonical LATS1/2 effects, and restrict multiple bacterial infections, supporting broader innate immune roles relevant to STK4 deficiency susceptibility. (louis2024thehippokinases pages 1-2)
Evidence quality and limitations
- The clinical evidence base is dominated by case reports and small case series, limiting robust frequency estimates for phenotypes, genotype–phenotype correlations, and survival statistics.
- Several key registry identifiers (Orphanet, ICD, MeSH) and PubMed PMIDs were not available directly in the retrieved text evidence used in this run; therefore they are not asserted here.
Visual evidence
- Table/Figure evidence of immunologic parameters and clinical features (warts and cardiac defects) was retrieved from the Blood 2012 report (Table 1 and Figure 1) (abdollahpour2012thephenotypeof media f08af791, abdollahpour2012thephenotypeof media cada1af7).
References
-
(abdollahpour2012thephenotypeof pages 1-2): Hengameh Abdollahpour, Giridharan Appaswamy, Daniel Kotlarz, Jana Diestelhorst, Rita Beier, Alejandro A. Schäffer, E. Michael Gertz, Axel Schambach, Hans H. Kreipe, Dietmar Pfeifer, Karin R. Engelhardt, Nima Rezaei, Bodo Grimbacher, Sabine Lohrmann, Roya Sherkat, and Christoph Klein. The phenotype of human stk4 deficiency. Blood, 119:3450-3457, Apr 2012. URL: https://doi.org/10.1182/blood-2011-09-378158, doi:10.1182/blood-2011-09-378158. This article has 388 citations and is from a highest quality peer-reviewed journal.
-
(schipp2018ebvnegativelymphoma pages 1-2): Cyrill Schipp, David Schlütermann, Andrea Hönscheid, Schafiq Nabhani, Jessica Höll, Prasad T. Oommen, Sebastian Ginzel, Bernhard Fleckenstein, Björn Stork, Arndt Borkhardt, Polina Stepensky, and Ute Fischer. Ebv negative lymphoma and autoimmune lymphoproliferative syndrome like phenotype extend the clinical spectrum of primary immunodeficiency caused by stk4 deficiency. Frontiers in Immunology, Oct 2018. URL: https://doi.org/10.3389/fimmu.2018.02400, doi:10.3389/fimmu.2018.02400. This article has 59 citations and is from a peer-reviewed journal.
-
(alsaud2024auniquestk4 pages 2-3): Bandar Al-Saud, Huda Alajlan, Hibah Alruwaili, Latifa Almoaibed, Amer Al-Mazrou, Hazem Ghebeh, Monther Al-Alwan, and Anas M. Alazami. A unique stk4 mutation truncating only the c-terminal sarah domain results in a mild clinical phenotype despite severe t cell lymphopenia: case report. Frontiers in Immunology, Feb 2024. URL: https://doi.org/10.3389/fimmu.2024.1329610, doi:10.3389/fimmu.2024.1329610. This article has 5 citations and is from a peer-reviewed journal.
-
(ying2024epidermodysplasiaverruciformisand pages 8-8): Wenjing Ying, Xin Long, Travis Vandergriff, Hemanth Karnati, Meghan Heberton, Mingyi Chen, Xiaochuan Wang, Christian Wysocki, and Xiao-Fei Kong. Epidermodysplasia verruciformis and vδ2 γδ t-cell expansion in stk4 deficiency. Journal of Clinical Immunology, Aug 2024. URL: https://doi.org/10.1007/s10875-024-01780-z, doi:10.1007/s10875-024-01780-z. This article has 4 citations and is from a domain leading peer-reviewed journal.
-
(OpenTargets Search: STK4 deficiency,immunodeficiency due to STK4 deficiency,primary immunodeficiency STK4): Open Targets Query (STK4 deficiency,immunodeficiency due to STK4 deficiency,primary immunodeficiency STK4, 17 results). Buniello, A. et al. (2025). Open Targets Platform: facilitating therapeutic hypotheses building in drug discovery. Nucleic Acids Research.
-
(radwan2020acaseof pages 1-2): Nesrine Radwan, Rasha El-Owaidy, Zeinab A. El-Sayed, Ashraf Abdel-Baky, Alaa El-Haddad, Hanaa Rashad, Eman Naguib Khorshed, Craig D. Platt, Jacqueline G. Wallace, Janet Chou, Elham Hossny, and Shereen Medhat Reda. A case of stk4 deficiency with complications evoking mycobacterial infection. Journal of Clinical Immunology, 40:665-669, May 2020. URL: https://doi.org/10.1007/s10875-020-00783-w, doi:10.1007/s10875-020-00783-w. This article has 13 citations and is from a domain leading peer-reviewed journal.
-
(guennoun2021anovelstk4 pages 1-3): Andrea Guennoun, Salim Bougarn, Taushif Khan, Rafah Mackeh, Mahbuba Rahman, Fatima Al-Ali, Manar Ata, Waleed Aamer, Debra Prosser, Tanwir Habib, Evonne Chin-Smith, Khawla Al-Darwish, Qian Zhang, Alya Al-Shakaki, Amal Robay, Ronald G. Crystal, Khalid Fakhro, Amal Al-Naimi, Eman Al Maslamani, Amjad Tuffaha, Ibrahim Janahi, Mohammad Janahi, Donald R. Love, Mohammed Yousuf Karim, Bernice Lo, Amel Hassan, Mehdi Adeli, and Nico Marr. A novel stk4 mutation impairs t cell immunity through dysregulation of cytokine-induced adhesion and chemotaxis genes. Journal of Clinical Immunology, 41:1839-1852, Aug 2021. URL: https://doi.org/10.1007/s10875-021-01115-2, doi:10.1007/s10875-021-01115-2. This article has 14 citations and is from a domain leading peer-reviewed journal.
-
(jørgensen2021stk4deficiencyimpairs pages 1-2): Sofie E. Jørgensen, Ali Al-Mousawi, Kristian Assing, Ulla Hartling, Dorthe Grosen, Niels Fisker, Christian Nielsen, Marianne A. Jakobsen, and Trine H. Mogensen. Stk4 deficiency impairs innate immunity and interferon production through negative regulation of tbk1-irf3 signaling. Journal of Clinical Immunology, 41:109-124, Oct 2021. URL: https://doi.org/10.1007/s10875-020-00891-7, doi:10.1007/s10875-020-00891-7. This article has 25 citations and is from a domain leading peer-reviewed journal.
-
(dang2016defectiveleukocyteadhesion pages 1-2): Tarana Singh Dang, Joseph DP Willet, Helen R Griffin, Neil V Morgan, Graeme O’Boyle, Peter D Arkwright, Stephen M Hughes, Mario Abinun, Louise J Tee, Dawn Barge, Karin R Engelhardt, Michael Jackson, Andrew J Cant, Eamonn R Maher, Mauro Santibanez Koref, Louise N Reynard, Simi Ali, and Sophie Hambleton. Defective leukocyte adhesion and chemotaxis contributes to combined immunodeficiency in humans with autosomal recessive mst1 deficiency. Journal of Clinical Immunology, 36:117-122, Jan 2016. URL: https://doi.org/10.1007/s10875-016-0232-2, doi:10.1007/s10875-016-0232-2. This article has 92 citations and is from a domain leading peer-reviewed journal.
-
(alsaud2024auniquestk4 pages 1-2): Bandar Al-Saud, Huda Alajlan, Hibah Alruwaili, Latifa Almoaibed, Amer Al-Mazrou, Hazem Ghebeh, Monther Al-Alwan, and Anas M. Alazami. A unique stk4 mutation truncating only the c-terminal sarah domain results in a mild clinical phenotype despite severe t cell lymphopenia: case report. Frontiers in Immunology, Feb 2024. URL: https://doi.org/10.3389/fimmu.2024.1329610, doi:10.3389/fimmu.2024.1329610. This article has 5 citations and is from a peer-reviewed journal.
-
(jørgensen2021stk4deficiencyimpairs pages 2-4): Sofie E. Jørgensen, Ali Al-Mousawi, Kristian Assing, Ulla Hartling, Dorthe Grosen, Niels Fisker, Christian Nielsen, Marianne A. Jakobsen, and Trine H. Mogensen. Stk4 deficiency impairs innate immunity and interferon production through negative regulation of tbk1-irf3 signaling. Journal of Clinical Immunology, 41:109-124, Oct 2021. URL: https://doi.org/10.1007/s10875-020-00891-7, doi:10.1007/s10875-020-00891-7. This article has 25 citations and is from a domain leading peer-reviewed journal.
-
(abdollahpour2012thephenotypeof pages 3-4): Hengameh Abdollahpour, Giridharan Appaswamy, Daniel Kotlarz, Jana Diestelhorst, Rita Beier, Alejandro A. Schäffer, E. Michael Gertz, Axel Schambach, Hans H. Kreipe, Dietmar Pfeifer, Karin R. Engelhardt, Nima Rezaei, Bodo Grimbacher, Sabine Lohrmann, Roya Sherkat, and Christoph Klein. The phenotype of human stk4 deficiency. Blood, 119:3450-3457, Apr 2012. URL: https://doi.org/10.1182/blood-2011-09-378158, doi:10.1182/blood-2011-09-378158. This article has 388 citations and is from a highest quality peer-reviewed journal.
-
(ying2024epidermodysplasiaverruciformisand pages 1-2): Wenjing Ying, Xin Long, Travis Vandergriff, Hemanth Karnati, Meghan Heberton, Mingyi Chen, Xiaochuan Wang, Christian Wysocki, and Xiao-Fei Kong. Epidermodysplasia verruciformis and vδ2 γδ t-cell expansion in stk4 deficiency. Journal of Clinical Immunology, Aug 2024. URL: https://doi.org/10.1007/s10875-024-01780-z, doi:10.1007/s10875-024-01780-z. This article has 4 citations and is from a domain leading peer-reviewed journal.
-
(schipp2018ebvnegativelymphoma pages 7-8): Cyrill Schipp, David Schlütermann, Andrea Hönscheid, Schafiq Nabhani, Jessica Höll, Prasad T. Oommen, Sebastian Ginzel, Bernhard Fleckenstein, Björn Stork, Arndt Borkhardt, Polina Stepensky, and Ute Fischer. Ebv negative lymphoma and autoimmune lymphoproliferative syndrome like phenotype extend the clinical spectrum of primary immunodeficiency caused by stk4 deficiency. Frontiers in Immunology, Oct 2018. URL: https://doi.org/10.3389/fimmu.2018.02400, doi:10.3389/fimmu.2018.02400. This article has 59 citations and is from a peer-reviewed journal.
-
(guennoun2021stk4deficiencyunderlies pages 15-19): Andrea Guennoun, Salim Bougarn, Taushif Khan, Rafah Mackeh, Mahbuba Rahman, Fatima Al Ali, Manar Ata, Waleed Aamer, Debra Prosser, Tanwir Habib, Evonne Chin-Smith, Khawla Al-Darwish, Qian Zhang, Alya Al-Shakaki, Amal Robay, Ronald Crystal, Khalid Fakhro, Amal Al-Naimi, Eman Al Maslamani, Amjad Tuffaha, Ibrahim Janahi, Mohammad Janahi, Donald Love, Mohammed Yousuf Karim, Bernice Lo, Amel Hassan, Mehdi Adeli, and Nico Marr. Stk4 deficiency underlies impaired interferon signaling and t cell immunity. ArXiv, Mar 2021. URL: https://doi.org/10.21203/rs.3.rs-328827/v1, doi:10.21203/rs.3.rs-328827/v1. This article has 0 citations.
-
(abdollahpour2012thephenotypeof pages 4-6): Hengameh Abdollahpour, Giridharan Appaswamy, Daniel Kotlarz, Jana Diestelhorst, Rita Beier, Alejandro A. Schäffer, E. Michael Gertz, Axel Schambach, Hans H. Kreipe, Dietmar Pfeifer, Karin R. Engelhardt, Nima Rezaei, Bodo Grimbacher, Sabine Lohrmann, Roya Sherkat, and Christoph Klein. The phenotype of human stk4 deficiency. Blood, 119:3450-3457, Apr 2012. URL: https://doi.org/10.1182/blood-2011-09-378158, doi:10.1182/blood-2011-09-378158. This article has 388 citations and is from a highest quality peer-reviewed journal.
-
(schipp2018ebvnegativelymphoma pages 2-3): Cyrill Schipp, David Schlütermann, Andrea Hönscheid, Schafiq Nabhani, Jessica Höll, Prasad T. Oommen, Sebastian Ginzel, Bernhard Fleckenstein, Björn Stork, Arndt Borkhardt, Polina Stepensky, and Ute Fischer. Ebv negative lymphoma and autoimmune lymphoproliferative syndrome like phenotype extend the clinical spectrum of primary immunodeficiency caused by stk4 deficiency. Frontiers in Immunology, Oct 2018. URL: https://doi.org/10.3389/fimmu.2018.02400, doi:10.3389/fimmu.2018.02400. This article has 59 citations and is from a peer-reviewed journal.
-
(ueda2020mst12balanceimmune pages 1-2): Yoshihiro Ueda, Naoyuki Kondo, and Tatsuo Kinashi. Mst1/2 balance immune activation and tolerance by orchestrating adhesion, transcription, and organelle dynamics in lymphocytes. Frontiers in Immunology, May 2020. URL: https://doi.org/10.3389/fimmu.2020.00733, doi:10.3389/fimmu.2020.00733. This article has 28 citations and is from a peer-reviewed journal.
-
(louis2024thehippokinases pages 1-2): Brendyn M. St. Louis, Sydney M. Quagliato, Yu-Ting Su, Gregory Dyson, and Pei-Chung Lee. The hippo kinases control inflammatory hippo signaling and restrict bacterial infection in phagocytes. May 2024. URL: https://doi.org/10.1128/mbio.03429-23, doi:10.1128/mbio.03429-23. This article has 8 citations and is from a domain leading peer-reviewed journal.
-
(bouchard2020hipposignaltransduction pages 4-6): Antoine Bouchard, Mariko Witalis, Jinsam Chang, Vincent Panneton, Joanna Li, Yasser Bouklouch, and Woong-Kyung Suh. Hippo signal transduction mechanisms in t cell immunity. Immune Network, Oct 2020. URL: https://doi.org/10.4110/in.2020.20.e36, doi:10.4110/in.2020.20.e36. This article has 11 citations.
-
(abdollahpour2012thephenotypeof media f08af791): Hengameh Abdollahpour, Giridharan Appaswamy, Daniel Kotlarz, Jana Diestelhorst, Rita Beier, Alejandro A. Schäffer, E. Michael Gertz, Axel Schambach, Hans H. Kreipe, Dietmar Pfeifer, Karin R. Engelhardt, Nima Rezaei, Bodo Grimbacher, Sabine Lohrmann, Roya Sherkat, and Christoph Klein. The phenotype of human stk4 deficiency. Blood, 119:3450-3457, Apr 2012. URL: https://doi.org/10.1182/blood-2011-09-378158, doi:10.1182/blood-2011-09-378158. This article has 388 citations and is from a highest quality peer-reviewed journal.
-
(abdollahpour2012thephenotypeof media cada1af7): Hengameh Abdollahpour, Giridharan Appaswamy, Daniel Kotlarz, Jana Diestelhorst, Rita Beier, Alejandro A. Schäffer, E. Michael Gertz, Axel Schambach, Hans H. Kreipe, Dietmar Pfeifer, Karin R. Engelhardt, Nima Rezaei, Bodo Grimbacher, Sabine Lohrmann, Roya Sherkat, and Christoph Klein. The phenotype of human stk4 deficiency. Blood, 119:3450-3457, Apr 2012. URL: https://doi.org/10.1182/blood-2011-09-378158, doi:10.1182/blood-2011-09-378158. This article has 388 citations and is from a highest quality peer-reviewed journal.