Hydatidiform Mole
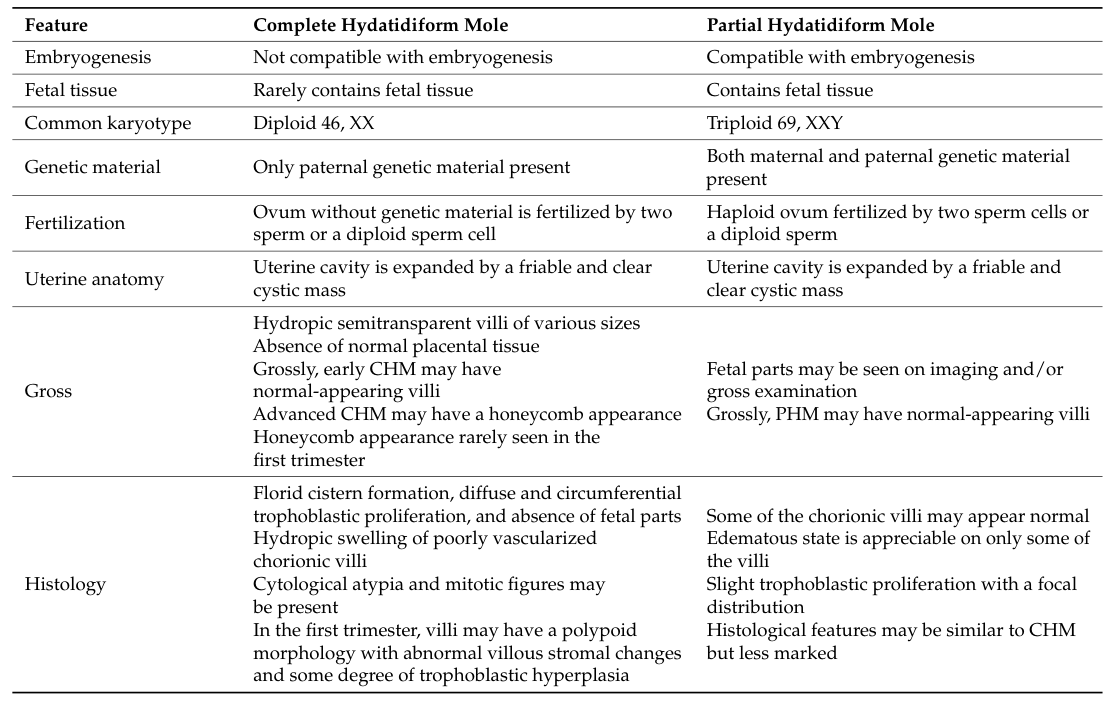
Hydatidiform mole is the benign, premalignant end of the gestational trophoblastic disease spectrum: an abnormal pregnancy characterized by hydropic swelling of the chorionic villi and proliferation of villous trophoblast. It arises from aberrant fertilization that produces an imbalance of parental genomes. Complete hydatidiform mole is typically diploid and androgenetic (entirely paternal genome, most often from duplication of a single sperm in an ovum lacking maternal chromosomes), with no fetal tissue and diffuse villous hydrops; partial hydatidiform mole is typically triploid and diandric (two paternal genome complements plus one maternal), with focal villous hydrops and a non-viable fetus. The androgenetic/diandric excess of paternally expressed genes and loss of maternally imprinted CDKN1C/p57 drive trophoblastic hyperplasia. Rare recurrent forms are maternal-effect diseases, in which the causative genotype is the mother's rather than the conceptus's, and they divide into two mechanisms. Biallelic variants in the oocyte subcortical maternal complex genes NLRP7 and KHDC3L leave maternally methylated regions unmethylated, so a diploid biparental conceptus behaves epigenetically as an androgenetic one; PADI6 is a further component of the same complex implicated in recurrent mole, without a reported methylation measurement. Biallelic variants in the meiotic double-strand-break genes MEI1, TOP6BL and REC114 instead leave the oocyte without maternal chromosomes, so the conceptus really is androgenetic - a route demonstrated for Mei1 in mice, where the whole first-division spindle is extruded into the polar body. Hydatidiform mole presents with first-trimester bleeding and markedly elevated hCG, is treated by uterine evacuation, and confers a risk of progression to gestational trophoblastic neoplasia, requiring serial hCG surveillance.
Ask OpenScientist
Ask a research question about Hydatidiform Mole. OpenScientist will conduct autonomous deep research using the Disorder Mechanisms Knowledge Base and PubMed literature (typically 10-30 minutes).
Do not include personal health information in your question. Questions and results are cached in your browser's local storage.
Subtypes
7Show evidence (2 references)
Show evidence (2 references)
- HYDM1
- HYDM2
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (2 references)
Show evidence (2 references)
Pathophysiology
4Show evidence (4 references)
Show evidence (7 references)
Show evidence (2 references)
Show evidence (2 references)
Pathograph
Phenotypes
3Blood 1
Show evidence (1 reference)
Digestive 1
Show evidence (1 reference)
Metabolism 1
Show evidence (1 reference)
Genetic Associations
6Show evidence (3 references)
Show evidence (2 references)
Show evidence (2 references)
Show evidence (2 references)
Show evidence (2 references)
Show evidence (2 references)
Medical Actions
2Show evidence (1 reference)
Show evidence (1 reference)
Source YAML
click to showname: Hydatidiform Mole
creation_date: "2026-06-17T00:00:00Z"
description: >-
Hydatidiform mole is the benign, premalignant end of the gestational
trophoblastic disease spectrum: an abnormal pregnancy characterized by
hydropic swelling of the chorionic villi and proliferation of villous
trophoblast. It arises from aberrant fertilization that produces an
imbalance of parental genomes. Complete hydatidiform mole is typically
diploid and androgenetic (entirely paternal genome, most often from
duplication of a single sperm in an ovum lacking maternal chromosomes),
with no fetal tissue and diffuse villous hydrops; partial hydatidiform
mole is typically triploid and diandric (two paternal genome
complements plus one maternal), with focal villous hydrops and a
non-viable fetus. The androgenetic/diandric excess of paternally
expressed genes and loss of maternally imprinted CDKN1C/p57 drive
trophoblastic hyperplasia. Rare recurrent forms are maternal-effect
diseases, in which the causative genotype is the mother's rather than the
conceptus's, and they divide into two mechanisms. Biallelic variants in the
oocyte subcortical maternal complex genes NLRP7 and KHDC3L leave maternally
methylated regions unmethylated, so a diploid biparental conceptus behaves
epigenetically as an androgenetic one; PADI6 is a further component of the
same complex implicated in recurrent mole, without a reported methylation
measurement. Biallelic variants in the meiotic double-strand-break genes
MEI1, TOP6BL and REC114 instead leave the oocyte without maternal
chromosomes, so the conceptus really is androgenetic - a route demonstrated
for Mei1 in mice, where the whole first-division spindle is extruded into
the polar body. Hydatidiform mole presents with first-trimester
bleeding and markedly elevated hCG, is treated by uterine
evacuation, and confers a risk of progression to gestational
trophoblastic neoplasia, requiring serial hCG surveillance.
categories:
- Pregnancy Disorder
- Gestational Trophoblastic Disease
disease_term:
preferred_term: Hydatidiform Mole
term:
id: MONDO:0006248
label: hydatidiform mole
parents:
- gestational trophoblastic disease
- pregnancy disorder
has_subtypes:
- name: Complete Mole
display_name: Complete Hydatidiform Mole
classification: histological
subtype_term:
preferred_term: complete hydatidiform mole
term:
id: MONDO:0016785
label: complete hydatidiform mole
description: >-
Complete hydatidiform mole is typically diploid and androgenetic, with
the entire genome paternally derived. There is no identifiable fetal or
embryonic tissue, and the chorionic villi show diffuse hydropic swelling
with circumferential trophoblastic hyperplasia. p57 immunostaining is
negative in villous cytotrophoblast and stroma because the maternally
expressed CDKN1C allele is absent. It carries the highest risk of
progression to gestational trophoblastic neoplasia.
evidence:
- reference: PMID:33024305
reference_title: "Refined diagnosis of hydatidiform moles with p57 immunohistochemistry and molecular genotyping: updated analysis of a prospective series of 2217 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Of 564 \nsuccessfully immunostained CHMs, 563 (99.8%) were p57-negative"
explanation: >-
A large prospective series confirms that complete hydatidiform moles are
essentially uniformly p57-negative, reflecting absence of the maternally
expressed CDKN1C allele.
- reference: PMID:33024305
reference_title: "Refined diagnosis of hydatidiform moles with p57 immunohistochemistry and molecular genotyping: updated analysis of a prospective series of 2217 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Of 153 genotyped \nCHMs, 148 (96.7%) were androgenetic"
explanation: >-
The same series confirms that complete moles are predominantly
androgenetic (paternal-only genome).
- name: Partial Mole
display_name: Partial Hydatidiform Mole
classification: histological
subtype_term:
preferred_term: partial hydatidiform mole
term:
id: MONDO:0016786
label: partial hydatidiform mole
description: >-
Partial hydatidiform mole is typically triploid and diandric (two
paternal genome complements and one maternal), with focal villous
hydrops, scattered trophoblastic hyperplasia, and frequently an abnormal
non-viable fetus or fetal tissue. p57 immunostaining is retained because
a maternal genome is present. Risk of progression to neoplasia is much
lower than for complete mole.
evidence:
- reference: PMID:33024305
reference_title: "Refined diagnosis of hydatidiform moles with p57 immunohistochemistry and molecular genotyping: updated analysis of a prospective series of 2217 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Of 497 genotyped PHMs, 484 (97%) \nwere diandric triploid"
explanation: >-
Genotyping confirms that partial hydatidiform moles are predominantly
diandric triploid (two paternal genome complements plus one maternal).
- reference: PMID:33024305
reference_title: "Refined diagnosis of hydatidiform moles with p57 immunohistochemistry and molecular genotyping: updated analysis of a prospective series of 2217 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Of 486 successfully \nimmunostained PHMs, 481 (99%) were p57-positive"
explanation: >-
Partial moles retain p57 expression because a maternal genome (and thus
the maternally expressed CDKN1C allele) is present.
- name: Familial Biparental Mole
display_name: Familial Biparental (Recurrent) Hydatidiform Mole
classification: molecular
children:
- HYDM1
- HYDM2
description: >-
Familial recurrent hydatidiform mole is a rare autosomal recessive,
maternal-effect condition in which affected women have recurrent complete
moles despite a normal biparental (diploid) genome. It is caused by
biallelic variants in NLRP7 or KHDC3L, which disrupt establishment of
maternal genomic imprinting in the oocyte so that the conceptus behaves
epigenetically like an androgenetic mole.
evidence:
- reference: PMID:38665615
reference_title: "Decoding the Genetics of Recurrent Molar Pregnancy."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The risk of recurrence \nis seen to be associated with biallelic maternal mutations in NLRP7, KHDC3 L and \nPAD16 genes."
explanation: >-
Recurrent (familial biparental) hydatidiform mole is associated with
biallelic maternal-effect mutations in NLRP7 and KHDC3L.
- name: HYDM1
display_name: Recurrent Hydatidiform Mole 1 (NLRP7)
classification: molecular
subtype_term:
preferred_term: hydatidiform mole, recurrent, 1
term:
id: MONDO:0009273
label: hydatidiform mole, recurrent, 1
description: >-
The NLRP7-defined form and the commonest monogenic cause of recurrent mole.
NLRP7 encodes a component of the oocyte subcortical maternal complex, and
the moles are diploid biparental: the causative genotype belongs to the
mother, not to the conceptus.
genes:
- preferred_term: NLRP7
term:
id: hgnc:22947
label: NLRP7
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:42588606
reference_title: "NLRP7 in Hydatidiform Mole and Gestational Trophoblastic Neoplasia: From Maternal-Effect Biology to a Genetic Permissiveness Framework for Integrated Cancer Surveillance and Reproductive Decision-Making."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: REVIEW_SYNTHESIS
snippet: >-
Biallelic mutations of NLRP7, a maternal-effect gene encoding a key component of the subcortical maternal complex, are the major monogenic cause of recurrent hydatidiform mole (RHM)
explanation: >-
Names NLRP7 as the leading monogenic cause of recurrent mole and states
that it acts as a maternal-effect gene through the subcortical maternal
complex, which is the claim this row rests on.
- name: HYDM2
display_name: Recurrent Hydatidiform Mole 2 (KHDC3L)
classification: molecular
subtype_term:
preferred_term: hydatidiform mole, recurrent, 2
term:
id: MONDO:0013671
label: hydatidiform mole, recurrent, 2
description: >-
The KHDC3L-defined form. KHDC3L is a second subcortical maternal complex
component, the moles are likewise diploid biparental, and genome-wide
methylation loss has been measured directly in a patient's own oocytes.
genes:
- preferred_term: KHDC3L
term:
id: hgnc:33699
label: KHDC3L
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:32210488
reference_title: "Founder Effect of KHDC3L, p.M1V Mutation, on Iranian Patients with Recurrent Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: BACKGROUND
snippet: >-
Three maternal-effect genes, including NLRP7, KHDC3L, and PADI6 have been identified as the cause of RHMs.
explanation: >-
Names KHDC3L among the maternal-effect genes causing recurrent mole. The
sentence covers three genes, so the KHDC3L-specific support is the
homozygous founder variant this study reports and which the entry's
KHDC3L genetic record cites.
- name: HYDM3
display_name: Recurrent Hydatidiform Mole 3 (MEI1)
classification: molecular
subtype_term:
preferred_term: hydatidiform mole, recurrent, 3
term:
id: MONDO:0032746
label: hydatidiform mole, recurrent, 3
description: >-
The MEI1-defined form. MEI1 is required for meiotic double-strand break
formation, and unlike the NLRP7 and KHDC3L forms the resulting moles are
androgenetic monospermic rather than biparental: the oocyte loses its own
chromosomes, so the conceptus carries only the paternal genome. This is
still a maternal-effect disease, because the biallelic variants are the
mother's.
genes:
- preferred_term: MEI1
term:
id: hgnc:28613
label: MEI1
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
This evidence is based on the identification of bi-allelic mutations in MEI1 in two familial case subjects, in TOP6BL in two unrelated women, and in REC114 in one woman.
explanation: >-
Gives the per-gene basis of the claim rather than the grouped statement:
MEI1 rests on two familial case subjects, which is the strongest of the
three and the only one for which the authors obtained molar tissue.
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
Therefore, HMs from affected women with mutations in the three genes are androgenetic and have a different mechanism at their origin than HMs from women with bi-allelic mutations in NLRP7 or KHDC3L.
explanation: >-
States the genotypic distinction this row records: the moles are
androgenetic, not biparental, and the mechanism differs from the
NLRP7/KHDC3L route.
- name: HYDM4
display_name: Recurrent Hydatidiform Mole 4 (TOP6BL)
classification: molecular
subtype_term:
preferred_term: hydatidiform mole, recurrent, 4
term:
id: MONDO:0032747
label: hydatidiform mole, recurrent, 4
description: >-
The TOP6BL-defined form. TOP6BL, approved under that symbol in 2023 and
reported in the primary literature as C11orf80 or TOPOVIBL, is required for
meiotic double-strand break formation, so this form shares the androgenetic
mechanism of HYDM3. It rests on two unrelated women, and the androgenetic
genotype of their moles was reported to the authors rather than measured by
them.
genes:
- preferred_term: TOP6BL
term:
id: hgnc:26197
label: C11orf80
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
This evidence is based on the identification of bi-allelic mutations in MEI1 in two familial case subjects, in TOP6BL in two unrelated women, and in REC114 in one woman.
explanation: >-
Gives the per-gene basis of the claim: TOP6BL rests on two unrelated
women, which is why this row records the gene without asserting the
strength the MEI1 row carries.
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
The tissues from affected woman HM74, with bi-allelic mutations in TOP6BL/C11orf80, were reported to be most likely androgenetic CHMs.
explanation: >-
Records the hedge in the source itself: the androgenetic genotype of the
TOP6BL moles was reported rather than measured by the authors, which is
why this row says tissue was not available for direct genotyping.
pathophysiology:
- name: Aberrant Fertilization and Parental Genome Imbalance
description: >-
Hydatidiform mole originates from abnormal fertilization producing an
excess of paternal relative to maternal genome. Complete moles are
usually diploid androgenetic, arising when an ovum that has lost or
inactivated its nucleus is fertilized and the paternal genome is
duplicated (or by dispermy); partial moles are usually triploid diandric,
arising when a normal ovum is fertilized by two sperm. This parental
genome imbalance is the initiating event of molar pregnancy.
Most cases are sporadic, but there is an inherited route to the same state.
Biallelic maternal variants in the meiotic double-strand-break genes MEI1,
TOP6BL and REC114 were identified together in women with recurrent
androgenetic complete moles. The mechanism was demonstrated in Mei1-null
mice: the oocyte extrudes its whole first-division spindle, carrying every
maternal chromosome, into the first polar body, and the resulting cytoplast
can still be fertilized, so the conceptus is androgenetic. The causative
genotype is the mother's, so these women have recurrent androgenetic moles
rather than one sporadic event.
cell_types:
- preferred_term: trophoblast cell
term:
id: CL:0000351
label: trophoblast cell
genes:
- preferred_term: MEI1
term:
id: hgnc:28613
label: MEI1
- preferred_term: TOP6BL
term:
id: hgnc:26197
label: C11orf80
- preferred_term: REC114
term:
id: hgnc:25065
label: REC114
evidence:
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
We identified bi-allelic deleterious mutations in MEI1, TOP6BL/C11orf80, and REC114, with roles in meiotic double-strand breaks formation in women with recurrent androgenetic complete hydatidiform moles.
explanation: >-
Names the three meiotic genes bound on this node and ties them to
recurrent androgenetic moles, which is the inherited route to the
parental-genome imbalance this node describes.
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: MODEL_ORGANISM
quote_role: PRIMARY_RESULT
snippet: >-
Thus, we uncover a meiotic abnormality in mammals and a mechanism for the genesis of androgenetic zygotes that is the extrusion of all maternal chromosomes and their spindles into the first polar body.
explanation: >-
Supplies the mechanism stated in this node's description: the maternal
chromosomes leave with the spindle into the first polar body.
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Hydatidiform moles are \ncharacterized by abnormal fertilization, resulting in villous hydrops and \ntrophoblastic hyperplasia"
explanation: >-
Hydatidiform mole originates from abnormal fertilization, the initiating
event of molar pregnancy.
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "being completely androgenetic in complete \nhydatidiform moles and diandric triploid in partial hydatidiform moles"
explanation: >-
Supports the androgenetic (complete) and diandric triploid (partial)
origins reflecting paternal-genome excess.
downstream:
- target: Loss of Genomic Imprinting and p57 Silencing
description: >-
Paternal-genome excess and absent maternal allele dysregulate imprinted
gene dosage, silencing maternally expressed CDKN1C/p57.
- name: Loss of Genomic Imprinting and p57 Silencing
description: >-
The androgenetic/diandric genome imbalance dysregulates parent-of-origin
imprinted genes. The maternally expressed, paternally imprinted gene
CDKN1C (encoding the cyclin-dependent kinase inhibitor p57KIP2) is
silenced when the maternal allele is absent (complete mole) or
epigenetically disrupted (familial biparental mole), removing a brake on
trophoblast proliferation. Negative p57 immunostaining of villous
cytotrophoblast and stroma is the diagnostic hallmark of complete mole.
cell_types:
- preferred_term: mononuclear cytotrophoblast cell
term:
id: CL:0000523
label: mononuclear cytotrophoblast cell
genes:
- preferred_term: NLRP7
term:
id: hgnc:22947
label: NLRP7
- preferred_term: KHDC3L
term:
id: hgnc:33699
label: KHDC3L
- preferred_term: PADI6
term:
id: hgnc:20449
label: PADI6
biological_processes:
- preferred_term: genomic imprinting
modifier: ABNORMAL
term:
id: GO:0071514
label: genomic imprinting
evidence:
- reference: PMID:26544189
reference_title: "Absence of Maternal Methylation in Biparental Hydatidiform Moles from Women with NLRP7 Maternal-Effect Mutations Reveals Widespread Placenta-Specific Imprinting."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
The methylation defects observed in five RHM biopsies from NLRP7 defective patients are restricted to lack-of-methylation at maternal DMRs.
explanation: >-
The measured lesion in the familial biparental form: maternally
methylated regions carry no methylation, which is the imprinting failure
this node asserts and the reason NLRP7 is bound here.
- reference: PMID:31847873
reference_title: "A KHDC3L mutation resulting in recurrent hydatidiform mole causes genome-wide DNA methylation loss in oocytes and persistent imprinting defects post-fertilisation."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
Genome-wide analysis of a pre-implantation embryo and molar tissue from the same patient showed that following fertilisation methylation defects at imprinted genes persist, while most non-imprinted regions of the genome recover near-normal methylation post-implantation.
explanation: >-
The same failure measured for KHDC3L, and it shows the defect persisting
at imprinted loci in the molar tissue itself.
- reference: PMID:29693651
reference_title: "Biallelic PADI6 variants linking infertility, miscarriages, and hydatidiform moles."
supports: SUPPORT
evidence_source: IN_VITRO
quote_role: PRIMARY_RESULT
snippet: >-
We demonstrated that PADI6 co-localizes with NLRP7 in human oocytes and preimplantation embryos and reviewed the morphology and genotypes of four products of conception from our patient.
explanation: >-
Co-localization with NLRP7 in human oocytes is why PADI6 is bound on the
same node. Note this is the weakest of the three bindings here: no
methylation measurement has been reported for a PADI6 mole.
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "fundamental genetic event leading to overall alteration of imprinting gene \nexpression in the molar trophoblast"
explanation: >-
Overrepresentation of the paternal genome alters imprinted gene
expression in the molar trophoblast, the basis for loss of the
maternally expressed CDKN1C/p57.
- reference: PMID:33024305
reference_title: "Refined diagnosis of hydatidiform moles with p57 immunohistochemistry and molecular genotyping: updated analysis of a prospective series of 2217 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Of 564 \nsuccessfully immunostained CHMs, 563 (99.8%) were p57-negative"
explanation: >-
Negative p57 immunostaining in complete moles reflects silencing of the
maternally expressed CDKN1C allele.
- reference: PMID:39057130
reference_title: "Gestational Trophoblastic Disease: Complete versus Partial Hydatidiform Moles."
supports: SUPPORT
evidence_source: OTHER
quote_role: REVIEW_SYNTHESIS
snippet: >-
Notably, recurrent occurrences are associated with abnormal genomic
imprinting of maternal effect genes such as NLRP7 (chromosome 19q13.4) and
KHDC3L (chromosome 6q1)
explanation: >-
Supports the familial-biparental route into this node: the two
maternal-effect genes bound here reach it through abnormal genomic
imprinting rather than through a paternal-genome excess. Graded OTHER with
REVIEW_SYNTHESIS because the sentence is the review's synthesis of the
recurrent-mole literature, not a measurement it made.
- reference: PMID:41786744
reference_title: "TCL1A mediates DNA methylation defects in recurrent hydatidiform mole with NLRP7 pathogenic variants."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: BACKGROUND
snippet: >-
Pathogenic variants in NLRP7, implicated in 55% of recurrent hydatidiform
mole characterized by hypomethylation at maternally methylated imprinted
regions, are proposed to disrupt de novo DNA methylation in human oocytes
explanation: >-
Names the specific epigenetic lesion behind the NLRP7 arm - hypomethylation
of maternally methylated imprinted regions - with the authors' own hedge
that the oocyte de novo methylation step is proposed rather than
demonstrated. Graded BACKGROUND: the sentence is this paper's framing of
established findings about patient methylomes, not its own TCL1A result.
downstream:
- target: Trophoblastic Hyperplasia and Villous Hydrops
description: >-
Loss of imprinting-dependent growth control drives excessive
trophoblast proliferation and hydropic villous swelling.
- name: Trophoblastic Hyperplasia and Villous Hydrops
description: >-
Disinhibited trophoblast proliferation produces the defining pathology of
molar pregnancy: enlarged, edematous (hydropic) chorionic villi with
hyperplastic villous trophoblast. Excess syncytiotrophoblast secretes
markedly elevated human chorionic gonadotropin (hCG), driving the
clinical features (hyperemesis, large-for-dates uterus, theca-lutein
cysts, and occasionally hyperthyroidism). This molar tissue constitutes
the abnormal "grape-like" placental mass.
cell_types:
- preferred_term: trophoblast cell
term:
id: CL:0000351
label: trophoblast cell
biological_processes:
- preferred_term: cell population proliferation
modifier: INCREASED
term:
id: GO:0008283
label: cell population proliferation
evidence:
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Hydatidiform moles are \ncharacterized by abnormal fertilization, resulting in villous hydrops and \ntrophoblastic hyperplasia"
explanation: >-
Villous hydrops and trophoblastic hyperplasia are the defining
pathological features of molar pregnancy.
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Complete molar pregnancies \npresent with symptoms such as first-trimester vaginal bleeding, severe nausea, \nand high β-human chorionic gonadotropin (β-hCG) levels."
explanation: >-
Attributes the presenting symptoms to the molar pregnancy itself, which
is the basis for the edges from this node to the bleeding and
nausea phenotypes.
downstream:
- target: Vaginal bleeding
causal_link_type: DIRECT
description: >-
Hydropic molar villi in the uterine cavity are what bleeds, and the cited
review lists first-trimester vaginal bleeding among the symptoms complete
molar pregnancies present with.
evidence:
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Complete molar pregnancies \npresent with symptoms such as first-trimester vaginal bleeding, severe nausea, \nand high β-human chorionic gonadotropin (β-hCG) levels."
explanation: >-
Lists first-trimester vaginal bleeding as a presenting symptom of the molar
pregnancy this node describes. The sentence enumerates symptoms without
ranking them, which is why this edge claims no frequency.
- target: Elevated hCG
causal_link_type: DIRECT
description: >-
The hyperplastic syncytiotrophoblast is itself the source of the hormone, so
the hCG level tracks trophoblast mass and is what post-evacuation
surveillance measures.
evidence:
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Complete molar pregnancies \npresent with symptoms such as first-trimester vaginal bleeding, severe nausea, \nand high β-human chorionic gonadotropin (β-hCG) levels."
explanation: >-
Lists high beta-hCG among the features produced by the molar trophoblast
proliferation this node describes.
- target: Severe nausea and vomiting
description: >-
Mediated by the markedly elevated hCG the hyperplastic syncytiotrophoblast
secretes rather than by the villous mass directly.
- target: Risk of Gestational Trophoblastic Neoplasia
description: >-
Residual or persistent hyperproliferative trophoblast after evacuation
can invade and progress to gestational trophoblastic neoplasia.
- name: Risk of Gestational Trophoblastic Neoplasia
description: >-
After uterine evacuation, a fraction of molar pregnancies progress to
gestational trophoblastic neoplasia (persistent/invasive mole or
choriocarcinoma), detected by a plateauing or rising hCG. The risk is
substantially higher for complete than partial moles. This malignant
sequela is captured in the separate Gestational Trophoblastic Neoplasm
entry; here it is the principal downstream complication of molar
pregnancy that mandates post-evacuation hCG surveillance.
cell_types:
- preferred_term: trophoblast cell
term:
id: CL:0000351
label: trophoblast cell
evidence:
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Posttreatment, regular \nβ-hCG monitoring is essential to detect potential progression to gestational \ntrophoblastic neoplasia (GTN)."
explanation: >-
Post-evacuation hCG surveillance is required precisely because molar
pregnancy can progress to gestational trophoblastic neoplasia.
- reference: PMID:20673583
reference_title: "Gestational trophoblastic disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "the premalignant disorders of complete and partial \nhydatidiform mole, and the malignant disorders of invasive mole"
explanation: >-
Complete and partial hydatidiform mole are premalignant precursors of
the malignant trophoblastic disorders (gestational trophoblastic
neoplasia).
phenotypes:
- name: Vaginal bleeding
description: >-
First-trimester vaginal bleeding is the most common presenting symptom of
hydatidiform mole.
phenotype_term:
preferred_term: Abnormal vaginal bleeding
term:
id: HP:0034263
label: Abnormal vaginal bleeding
evidence:
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Complete molar pregnancies \npresent with symptoms such as first-trimester vaginal bleeding, severe nausea, \nand high β-human chorionic gonadotropin (β-hCG) levels."
explanation: >-
First-trimester vaginal bleeding is a cardinal presenting symptom of
complete hydatidiform mole.
- name: Elevated hCG
description: >-
Markedly elevated serum human chorionic gonadotropin, often far above
that expected for gestational age, especially in complete mole.
phenotype_term:
preferred_term: Elevated circulating beta chorionic gonadotropin concentration
term:
id: HP:6000485
label: Elevated circulating beta chorionic gonadotropin concentration
reports_on:
- target: Trophoblastic Hyperplasia and Villous Hydrops
relationship: READOUT_OF
direction: POSITIVE
endpoint_context: DIAGNOSTIC
interpretation: Serum beta-hCG measures the burden of hyperplastic hCG-secreting villous trophoblast.
evidence:
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Complete molar pregnancies \npresent with symptoms such as first-trimester vaginal bleeding, severe nausea, \nand high β-human chorionic gonadotropin (β-hCG) levels."
explanation: >-
High beta-hCG levels are a hallmark presenting feature of complete
hydatidiform mole.
- name: Severe nausea and vomiting
description: >-
Exaggerated nausea/vomiting (hyperemesis), driven by markedly elevated
beta-hCG, is a common presenting symptom of complete molar pregnancy.
phenotype_term:
preferred_term: Severe nausea and vomiting
term:
id: HP:0002017
label: Nausea and vomiting
evidence:
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Complete molar pregnancies \npresent with symptoms such as first-trimester vaginal bleeding, severe nausea, \nand high β-human chorionic gonadotropin (β-hCG) levels."
explanation: >-
Severe nausea is listed among the cardinal presenting symptoms of complete
hydatidiform mole.
genetic:
- name: NLRP7
gene_term:
preferred_term: NLRP7
term:
id: hgnc:22947
label: NLRP7
relationship_type: CAUSATIVE
subtype: HYDM1
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:38665615
reference_title: "Decoding the Genetics of Recurrent Molar Pregnancy."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The risk of recurrence \nis seen to be associated with biallelic maternal mutations in NLRP7, KHDC3 L and \nPAD16 genes."
explanation: >-
Recurrence is associated with biallelic maternal mutations,
consistent with autosomal recessive (maternal-effect) inheritance.
evidence:
- reference: PMID:38665615
reference_title: "Decoding the Genetics of Recurrent Molar Pregnancy."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "compound heterozygous for pathogenic variants in the NLRP7 gene"
explanation: >-
Biallelic (compound heterozygous) maternal NLRP7 variants cause
recurrent molar pregnancy (familial biparental hydatidiform mole).
- reference: PMID:26544189
reference_title: "Absence of Maternal Methylation in Biparental Hydatidiform Moles from Women with NLRP7 Maternal-Effect Mutations Reveals Widespread Placenta-Specific Imprinting."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
The methylation defects observed in five RHM biopsies from NLRP7 defective patients are restricted to lack-of-methylation at maternal DMRs.
explanation: >-
Measures the epigenetic lesion directly in molar tissue from NLRP7
patients: maternally methylated regions carry no methylation, which is
how a diploid biparental conceptus comes to behave as an androgenetic
one.
- reference: PMID:26544189
reference_title: "Absence of Maternal Methylation in Biparental Hydatidiform Moles from Women with NLRP7 Maternal-Effect Mutations Reveals Widespread Placenta-Specific Imprinting."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
These epigenotypes are consistent with NLRP7 being a maternal-effect gene and involved in imprint acquisition in the oocyte.
explanation: >-
Places the NLRP7 lesion in the mother's oocyte rather than in the
conceptus, which is what makes this a maternal-effect disease.
- name: KHDC3L
gene_term:
preferred_term: KHDC3L
term:
id: hgnc:33699
label: KHDC3L
relationship_type: CAUSATIVE
subtype: HYDM2
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:32210488
reference_title: "Founder Effect of KHDC3L, p.M1V Mutation, on Iranian Patients with Recurrent Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "is also the first report of the \nhomozygous state that has led to RHM."
explanation: >-
A homozygous KHDC3L variant causing recurrent hydatidiform mole is
consistent with autosomal recessive inheritance.
evidence:
- reference: PMID:32210488
reference_title: "Founder Effect of KHDC3L, p.M1V Mutation, on Iranian Patients with Recurrent Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Three \nmaternal-effect genes, including NLRP7, KHDC3L, and PADI6 have been identified \nas the cause of RHMs."
explanation: >-
KHDC3L is one of the maternal-effect genes whose biallelic variants
cause recurrent (familial biparental) hydatidiform mole. The sentence
covers three genes, so the KHDC3L-specific support is the homozygous
founder variant reported by the same study.
- reference: PMID:31847873
reference_title: "A KHDC3L mutation resulting in recurrent hydatidiform mole causes genome-wide DNA methylation loss in oocytes and persistent imprinting defects post-fertilisation."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
Genome-wide analysis of a pre-implantation embryo and molar tissue from the same patient showed that following fertilisation methylation defects at imprinted genes persist, while most non-imprinted regions of the genome recover near-normal methylation post-implantation.
explanation: >-
Shows that in a KHDC3L patient the imprinting defect survives
fertilization in the molar tissue itself, while the rest of the genome
recovers, which is why the imprinted loci carry the phenotype.
- name: MEI1
notes: >-
MEI1 is required for meiotic double-strand break formation. Biallelic
maternal variants let the oocyte extrude its whole spindle, with all
maternal chromosomes, into the first polar body, so fertilization of the
remaining cytoplast yields an androgenetic conceptus. The route is therefore
maternal-effect like NLRP7 and KHDC3L but reaches the molar phenotype
through a different genotype: androgenetic monospermic rather than diploid
biparental.
gene_term:
preferred_term: MEI1
term:
id: hgnc:28613
label: MEI1
relationship_type: CAUSATIVE
subtype: HYDM3
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
This evidence is based on the identification of bi-allelic mutations in MEI1 in two familial case subjects, in TOP6BL in two unrelated women, and in REC114 in one woman.
explanation: >-
The per-gene statement behind the CAUSATIVE typing: two familial case
subjects with biallelic MEI1 variants, rather than the grouped
three-gene sentence in the abstract.
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: MODEL_ORGANISM
quote_role: PRIMARY_RESULT
snippet: >-
We demonstrate that Mei1-/- oocytes are capable of fertilization and 5% produce androgenetic zygotes.
explanation: >-
The mouse experiment that supplies the mechanism: loss of Mei1 is
sufficient to produce androgenetic zygotes, which is the step this entry
attributes to the gene.
- name: TOP6BL
notes: >-
TOP6BL is the partner subunit of the SPO11 complex that introduces meiotic
double-strand breaks, and it shares MEI1's route to an androgenetic
conceptus. HGNC approved the symbol TOP6BL on 2023-05-18, replacing
C11orf80, with TOPOVIBL as an alias; read live from rest.genenames.org. The
OBO HGNC build behind term validation still carries C11orf80, so `label:`
holds that string while `preferred_term` holds the approved symbol - the
same arrangement CLAUDE.md records for GBA1/GBA. The 2018 primary report
also writes TOP6BL/C11orf80.
gene_term:
preferred_term: TOP6BL
term:
id: hgnc:26197
label: C11orf80
relationship_type: CAUSATIVE
subtype: HYDM4
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
This evidence is based on the identification of bi-allelic mutations in MEI1 in two familial case subjects, in TOP6BL in two unrelated women, and in REC114 in one woman.
explanation: >-
The per-gene statement behind this record: two unrelated women with
biallelic TOP6BL variants.
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
The tissues from affected woman HM74, with bi-allelic mutations in TOP6BL/C11orf80, were reported to be most likely androgenetic CHMs.
explanation: >-
Records both the androgenetic genotype and the authors' own hedge about
it, since the tissue was reported to them rather than genotyped by them.
- name: REC114
notes: >-
REC114 acts with MEI1 and TOP6BL in meiotic double-strand break formation
and was implicated in recurrent androgenetic mole by the same study, in a
single woman. MONDO records no numbered recurrent-mole class for it:
`runoak -i ols:mondo search` returned nothing for "REC114" and
MONDO:0006248 has exactly four numbered recurrent-mole children, for NLRP7,
KHDC3L, MEI1 and TOP6BL. The gene therefore has no subtype row here.
gene_term:
preferred_term: REC114
term:
id: hgnc:25065
label: REC114
relationship_type: CAUSATIVE
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
This evidence is based on the identification of bi-allelic mutations in MEI1 in two familial case subjects, in TOP6BL in two unrelated women, and in REC114 in one woman.
explanation: >-
The per-gene statement behind this record, and the reason it is the
thinnest of the three meiotic genes: a single woman.
- reference: PMID:30388401
reference_title: "Causative Mutations and Mechanism of Androgenetic Hydatidiform Moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
Taken together, these data establish the role of MEI1, and possibly the two other genes, in the genesis of androgenetic CHMs.
explanation: >-
The authors' own grading of their three claims. REC114 and TOP6BL fall
under "possibly", which is recorded here rather than smoothed over.
- name: PADI6
notes: >-
PADI6 is a further subcortical maternal complex component, and this is the
thinnest of the six gene records here. Its established disease is oocyte and
early-embryo maturation arrest. The mole association rests on a single
family whose proband had a clinical history of four molar pregnancies: on
pathology re-review of the four available products of conception only one
met morphological criteria for a hydatidiform mole, and it showed patchy
rather than complete loss of p57 nuclear staining, while the one conception
genotyped - a non-molar loss - was diploid biparental. Two reviews cited
elsewhere in this entry list PADI6 alongside NLRP7 and KHDC3L as a cause of
recurrent mole, but those sentences cover the set rather than the member, so
the CAUSATIVE typing here rests on that family plus the demonstration that
PADI6 sits in the same oocyte complex as NLRP7. No methylation defect has
been reported for a PADI6 mole. MONDO records no numbered recurrent-mole
class for PADI6: `runoak -i ols:mondo search "PADI6"` returns only
MONDO:1010200 oocyte/zygote/embryo maturation arrest 16.
gene_term:
preferred_term: PADI6
term:
id: hgnc:20449
label: PADI6
relationship_type: CAUSATIVE
inheritance:
- name: Autosomal recessive
inheritance_term:
preferred_term: Autosomal recessive inheritance
term:
id: HP:0000007
label: Autosomal recessive inheritance
evidence:
- reference: PMID:29693651
reference_title: "Biallelic PADI6 variants linking infertility, miscarriages, and hydatidiform moles."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
quote_role: PRIMARY_RESULT
snippet: >-
We found biallelic missense variants that affect conserved amino acids in PADI6 and segregate with the disease phenotype in the family.
explanation: >-
The gene-specific report behind this record: biallelic PADI6 variants
segregating in one family whose proband had four molar pregnancies.
- reference: PMID:29693651
reference_title: "Biallelic PADI6 variants linking infertility, miscarriages, and hydatidiform moles."
supports: SUPPORT
evidence_source: IN_VITRO
quote_role: PRIMARY_RESULT
snippet: >-
We demonstrated that PADI6 co-localizes with NLRP7 in human oocytes and preimplantation embryos and reviewed the morphology and genotypes of four products of conception from our patient.
explanation: >-
Places PADI6 in the same oocyte complex as NLRP7 by direct
co-localization in human oocytes, which is why this entry treats it as
the same maternal-effect mechanism rather than a separate one.
treatments:
- name: Uterine Evacuation
description: >-
Suction dilation and curettage to evacuate the molar pregnancy is the
primary treatment for hydatidiform mole.
therapeutic_modality: SURGERY
treatment_term:
preferred_term: Surgical Procedure
term:
id: NCIT:C15329
label: Surgical Procedure
evidence:
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Treatment \ntypically involves dilation and curettage (D&C)"
explanation: >-
Dilation and curettage (uterine evacuation) is the primary treatment
for hydatidiform mole.
- name: Hysterectomy
description: >-
Hysterectomy is an alternative to uterine evacuation for patients who do not
desire future fertility, removing the molar tissue and reducing subsequent
gestational trophoblastic neoplasia risk.
therapeutic_modality: SURGERY
treatment_term:
preferred_term: Hysterectomy
term:
id: NCIT:C15329
label: Surgical Procedure
evidence:
- reference: PMID:29083593
reference_title: "Hydatidiform Mole."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "hysterectomy may be \nconsidered for patients not desiring future pregnancies"
explanation: >-
Hysterectomy is an accepted alternative treatment for molar pregnancy in
patients not desiring future fertility.
notes: >-
Recurrent-mole series. MONDO:0006248 has exactly four numbered
recurrent-mole children, and each names one gene in its OWL axioms: HYDM1
NLRP7, HYDM2 KHDC3L, HYDM3 MEI1, HYDM4 TOP6BL. All four now have a
has_subtypes row, and HYDM1 and HYDM2 are also listed as children of the
Familial Biparental Mole row, which is the grouping the two subcortical
maternal complex genes share. Two further causal genes have no numbered
class and so no row: REC114, reported by the same study as MEI1 and TOP6BL,
and PADI6. Searched `runoak -i ols:mondo search` for "REC114" (nothing) and
"PADI6" (only MONDO:1010200 oocyte/zygote/embryo maturation arrest 16) on
2026-09-26.
The maternal-effect point is the reason this entry does not read as ordinary
Mendelian inheritance. In all six recurrent-mole genes the biallelic variants
belong to the mother, and the affected conceptus need carry none of them, so
an affected woman's recurrence risk is set by her own genotype and oocyte
donation is the reproductive option that changes it. The `inheritance` blocks
record autosomal recessive transmission of the maternal genotype, which is
what HP:0000007 describes. HPO has no mode-of-inheritance term for a
maternal-effect disease: HP:0000005 has 40 descendants and none of them names
one, the nearest being HP:0034344 female-limited expression, which is about
sex-limited expression rather than about the mother's genotype acting on the
conceptus; `runoak -i ols:hp search "maternal effect"` returns nothing.
Enumerated through OLS on 2026-09-26. The distinction is therefore carried in
prose here and in each gene's own notes.
The two routes are not variants of one mechanism and are wired to different
pathophysiology nodes. NLRP7, KHDC3L and PADI6 sit on the imprinting node,
because their moles are diploid biparental and the lesion is absent
methylation at maternal DMRs. MEI1, TOP6BL and REC114 sit on the
aberrant-fertilization node, because their moles are genuinely androgenetic:
the oocyte loses its chromosomes before fertilization. The primary report
states that distinction explicitly. The three meiotic genes are also not
equally well supported - the authors themselves write that their data
establish MEI1 "and possibly the two other genes", which is quoted on the
REC114 record.
Classification note. `icdo_morphology` is deliberately left empty. An earlier
draft of this entry assigned `Trophoblastic Tumor` on the strength of the
ICD-O morphology codes moles do carry -- 9100/0 for hydatidiform mole NOS and
9103/0 for the partial mole. That was wrong, and by the same rule the rest of
the enum follows: NCIT:C3110 (Hydatidiform Mole) does not descend from
NCIT:C3422 (Trophoblastic Tumor) at all. Its parents are Gestational
Trophoblastic Disorder and Placenta Disorder, NCIT asserts no
Neoplastic_Status for it, and both NCIT:C4871 (Complete Hydatidiform Mole)
and NCIT:C4293 (Partial Hydatidiform Mole) sit explicitly under Placental
Non-Neoplastic Disorder. WHO agrees: gestational trophoblastic *neoplasia* is
reserved for invasive mole, choriocarcinoma, PSTT and ETT, and a non-invasive
mole is gestational trophoblastic disease but not GTN. Since
`ICDOMorphologyEnum` applies only to neoplastic diseases, the honest action is
to omit the slot rather than assert a neoplasm this entry is not. The molar
pregnancies that do progress are covered by the `Gestational_Trophoblastic_Neoplasm`
entry, which carries `Trophoblastic Tumor` correctly.
References & Deep Research
Deep Research
1Deep research results are used as seeds for research; they do not undergo the same validation as the main records and may contain errors. How we use deep research.
1. Disease Information
1.1 Definition and current understanding
Hydatidiform mole is an abnormal gestation characterized by hydropic swelling of chorionic villi with trophoblastic hyperplasia, and is classified into complete hydatidiform mole (CHM) and partial hydatidiform mole (PHM) based on genetic constitution and associated morphology (senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4).
- CHM (classic concept): androgenetic diploidy with paternal-only genome, typically 46,XX, usually no fetal tissue (gonzalez2024gestationaltrophoblasticdisease pages 1-2, senat2024gestationaltrophoblasticdisease pages 4-7).
- PHM (classic concept): diandric triploidy with maternal+paternal contribution, commonly 69,XXY (also 69,XXX/69,XYY reported), often with fetal tissue (gonzalez2024gestationaltrophoblasticdisease pages 2-4, senat2024gestationaltrophoblasticdisease pages 4-7).
1.2 Common synonyms / alternative names
- “Molar pregnancy”
- “Complete mole” / “Partial mole”
- Included under GTD; post-evacuation malignant/persistent disease is often described as post-molar gestational trophoblastic neoplasia (post-molar GTN) (larsson2025treatmentoutcomesand pages 1-2, joyce2024evaluationofbiomarkers pages 62-66).
1.3 Key identifiers (available in retrieved evidence)
- ICD-10 (reported in a Swedish population-based GTN study methods/coding): non-specified hydatidiform mole O01.9; GTN-related codes reported include invasive mole D39.2A, PSTT D39.2C, choriocarcinoma C58.9, and ETT morphology codes (91043/91053/m91053) (larsson2025treatmentoutcomesand pages 1-2).
- FIGO/WHO classification references: WHO 2020 classification for GTD is explicitly cited in a 2024 biomarker thesis-like document; FIGO diagnostic criteria for post-molar GTN are also summarized (joyce2024evaluationofbiomarkers pages 62-66, larsson2025treatmentoutcomesand pages 1-2).
- OMIM (recurrent/familial forms): NLRP7-associated recurrent HM labeled HYDM1 (OMIM#231090); KHDC3L-associated labeled HYDM2 (OMIM#614293) (kocabey2023highriskof pages 1-2).
Not found in retrieved full-text set: MeSH descriptor ID, Orphanet ID, MONDO ID.
1.4 Evidence provenance
This report is derived from aggregated disease-level resources (reviews/systematic reviews) and human clinical/registry/cohort studies and case series (senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4, larsson2025treatmentoutcomesand pages 1-2, zhu2025demographicsriskfactors pages 1-2, kocabey2023highriskof pages 1-2).
2. Etiology
2.1 Primary causal mechanisms
Abnormal fertilization leading to abnormal genomic dosage and imprinting is the core etiologic theme.
- Sporadic CHM: typically arises when an “empty” ovum (lacking maternal genome) is fertilized by one sperm with duplication or by two sperm, producing androgenetic diploidy (usually 46,XX) (gonzalez2024gestationaltrophoblasticdisease pages 1-2).
- Sporadic PHM: typically results from dispermy (two sperm) fertilizing a normal ovum, producing diandric triploidy (commonly 69,XXY) (gonzalez2024gestationaltrophoblasticdisease pages 1-2, gonzalez2024gestationaltrophoblasticdisease pages 2-4).
2.2 Risk factors (human clinical/epidemiology)
Consistently reported clinical risk factors include: - Maternal age extremes: increased under ~20 and over 40 years (senat2024gestationaltrophoblasticdisease pages 4-7). A review reports ~2.5-fold increased risk >35 and fivefold >40 (gonzalez2024gestationaltrophoblasticdisease pages 1-2). A cohort review lists maternal age >40 among established risk factors for post-molar GTN (zhu2025demographicsriskfactors pages 1-2). - Prior molar pregnancy: prior HM increases future HM risk; one review cites ~1–2% increased future HM risk and higher risk with multiple prior moles (florea2023hydatidiformmole—betweenchromosomal pages 8-9). - High pre-evacuation hCG and large uterine/lesion metrics: pre-evacuation β-hCG >100,000 mIU/mL, uterine size larger than gestational age, and large theca lutein cysts are repeatedly noted predictors of post-molar GTN (florea2023hydatidiformmole—betweenchromosomal pages 9-11, zhu2025demographicsriskfactors pages 1-2).
2.3 Protective factors
Protective factors were not explicitly identified in the retrieved evidence corpus.
2.4 Gene–environment interactions
Not explicitly described in the retrieved evidence corpus.
3. Phenotypes
3.1 Core clinical phenotypes (typical onset: early pregnancy/first trimester)
Common clinical presentation includes: - Vaginal bleeding (often first trimester) (joyce2024evaluationofbiomarkers pages 62-66, senat2024gestationaltrophoblasticdisease pages 4-7, riccio2023recurrenthydatidiformmoles pages 1-2) - Hyperemesis / severe nausea-vomiting (senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4, riccio2023recurrenthydatidiformmoles pages 1-2) - Uterine size larger than expected (senat2024gestationaltrophoblasticdisease pages 4-7) - Pelvic pressure/pain (gonzalez2024gestationaltrophoblasticdisease pages 2-4) - Theca lutein ovarian cysts; frequency reported ~9–25% (senat2024gestationaltrophoblasticdisease pages 4-7) - Pregnancy-induced hypertension / early preeclampsia (senat2024gestationaltrophoblasticdisease pages 4-7, riccio2023recurrenthydatidiformmoles pages 1-2) - Hyperthyroidism/thyrotoxicosis due to high β-hCG “molecular mimicry” with TSH (gonzalez2024gestationaltrophoblasticdisease pages 2-4, riccio2023recurrenthydatidiformmoles pages 1-2)
A 2024 biomarker-focused document notes that earlier detection has reduced severe presentations such as anemia, hyperemesis, preeclampsia, and hyperthyroidism (joyce2024evaluationofbiomarkers pages 62-66).
3.2 Laboratory abnormalities
- Markedly elevated β-hCG; CHM often has very high hCG and may exceed 100,000 U/L (joyce2024evaluationofbiomarkers pages 62-66, senat2024gestationaltrophoblasticdisease pages 4-7).
3.3 Imaging phenotypes
- Ultrasound “snowstorm/blizzard” appearance and “grape-like” vesicular/cystic changes are classic for CHM and may be identified around 8–10 weeks gestation in some settings (senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4, riccio2023recurrenthydatidiformmoles pages 1-2).
- In one 2024 source, ultrasound detection was higher for CHM (88%) than PHM (56%) (joyce2024evaluationofbiomarkers pages 62-66).
3.4 Pathology / histopathology phenotypes
CHM classically shows edematous hydropic villi with circumferential trophoblastic hyperplasia; PHM shows mixed villous populations (large hydropic and smaller fibrotic villi) (gonzalez2024gestationaltrophoblasticdisease pages 2-4).
3.5 Suggested ontology terms (examples)
HPO (phenotypes): - Abnormal uterine bleeding; Hyperemesis gravidarum; Pelvic pain; Enlarged uterus; Ovarian cyst; Hypertension in pregnancy / Preeclampsia; Hyperthyroidism; Elevated chorionic gonadotropin.
LOINC (lab concepts, examples): - “Chorionic gonadotropin.beta [Units/volume] in Serum or Plasma”.
UBERON (anatomy): uterus, placenta/chorionic villi, ovary.
(Exact ontology IDs should be assigned during curation in the target system; not all IDs were present in the retrieved sources.)
4. Genetic / Molecular Information
4.1 Core genetic concepts (sporadic CHM vs PHM)
- CHM: androgenetic diploidy (paternal-only genome), usually 46,XX (gonzalez2024gestationaltrophoblasticdisease pages 1-2).
- PHM: diandric triploidy, commonly 69,XXY (gonzalez2024gestationaltrophoblasticdisease pages 2-4).
4.2 Recurrent/biparental hydatidiform mole (maternal-effect gene etiologies)
A major advance is recognition of autosomal recessive maternal-effect causes of recurrent HM, in which conceptions may be diploid biparental but still manifest a complete-mole phenotype due to imprinting failure.
- In a large cohort of 113 recurrent HM patients, authors report that 50–80% carry biallelic pathogenic variants in NLRP7 or KHDC3L, and all molar tissues from these patients were diploid biparental; mutation-negative patients showed heterogeneous molar genotypes (only 8% diploid biparental; others androgenetic diploid and triploid dispermic) (nguyen2018thegeneticsof pages 1-2).
4.3 Causal genes and example variants (human evidence)
- NLRP7 (maternal-effect gene; HYDM1, OMIM#231090): A 2023 case series reported homozygous pathogenic variants c.2471+1G>A (splice-site) and c.2571dupC (p.Ile858HisfsTer11) (frameshift); all three NLRP7-positive recurrent HM cases developed GTN and required single-agent chemotherapy with normalization of β-hCG (kocabey2023highriskof pages 2-4, kocabey2023highriskof pages 1-2).
- KHDC3L (maternal-effect gene; HYDM2, OMIM#614293): review-level evidence indicates a smaller fraction of familial recurrent cases (e.g., ~10–14% in some reviews) and recommends testing after NLRP7 if negative; specific c./p. variants were not present in the extracted context (nasser2024molecularbasisof pages 5-6, kocabey2023highriskof pages 1-2).
- PADI6: a 2023 narrative review describes recessive PADI6 variants linked to infertility, early embryonic arrest after ART, and HM; specific variants were not provided in the retrieved excerpt (florea2023hydatidiformmole—betweenchromosomal pages 8-9).
4.4 Epigenetic / imprinting abnormalities
A 2024 systematic review summarizes that maternal-effect mutations (particularly NLRP7) are associated with absence of maternal methylation and broader placenta-specific imprinting defects; abnormalities in methylation-related markers (including LINE-1 methylation) have been investigated as predictors of post-molar GTN (nasser2024molecularbasisof pages 15-16, nasser2024molecularbasisof pages 5-6).
5. Environmental Information
Environmental toxin, lifestyle, or infectious-agent causes were not established in the retrieved evidence corpus for HM.
6. Mechanism / Pathophysiology
6.1 Causal chain (high-level)
- Abnormal fertilization (empty ovum fertilization → androgenetic diploidy; dispermy → diandric triploidy) or maternal-effect gene dysfunction (biparental but imprinting-defective conceptus). (gonzalez2024gestationaltrophoblasticdisease pages 1-2, nguyen2018thegeneticsof pages 1-2)
- Aberrant trophoblast proliferation + villous hydrops → uterine enlargement, bleeding, hyperemesis. (gonzalez2024gestationaltrophoblasticdisease pages 2-4, senat2024gestationaltrophoblasticdisease pages 4-7)
- Excess β-hCG secretion → measurable biomarker used for monitoring; may cause thyrotoxicosis via TSH receptor cross-reactivity/mimicry. (gonzalez2024gestationaltrophoblasticdisease pages 2-4)
- Persistence after evacuation in a subset → post-molar GTN, diagnosed by FIGO hCG criteria (plateau, rise, or persistent detectable levels) (larsson2025treatmentoutcomesand pages 1-2, senat2024gestationaltrophoblasticdisease pages 4-7).
6.2 Suggested GO/CL terms (examples)
GO Biological Process (examples): trophoblast differentiation, placental development, DNA methylation, genomic imprinting.
CL cell types (examples): cytotrophoblast, syncytiotrophoblast, villous stromal cell.
(IDs not provided in the retrieved sources; should be assigned in curation.)
7. Anatomical Structures Affected
- Primary: uterus and placental chorionic villi (villous trophoblast), with ovarian involvement via theca lutein cysts (senat2024gestationaltrophoblasticdisease pages 4-7, joyce2024evaluationofbiomarkers pages 62-66).
- Secondary/complications: metastasis for invasive mole/GTN can involve lungs and vagina (senat2024gestationaltrophoblasticdisease pages 4-7).
Suggested UBERON (examples): uterus, placenta, ovary, lung.
8. Temporal Development
- Onset: typically detected in early pregnancy / first trimester, with ultrasound diagnosis often feasible around 8–10 weeks in some settings (senat2024gestationaltrophoblasticdisease pages 4-7).
- Progression: after evacuation, a minority develops persistent disease/post-molar GTN; surveillance relies on β-hCG dynamics over weeks to months, and FIGO criteria define plateau/rise/persistence (larsson2025treatmentoutcomesand pages 1-2, senat2024gestationaltrophoblasticdisease pages 4-7).
9. Inheritance and Population
9.1 Epidemiology (incidence)
Incidence varies geographically: - ~0.57–1.1 per 1,000 pregnancies in Europe/North America/Oceania and ~2 per 1,000 in Japan/Southeast Asia (senat2024gestationaltrophoblasticdisease pages 4-7). - Other sources cite 1–3 per 1,000 in developed regions and up to 10 per 1,000 in some developing settings; Japan 1.02–2.70 per 1,000 live births (zhu2025demographicsriskfactors pages 1-2).
9.2 Post-molar GTN risk (by mole type)
- CHM: commonly ~15–20% progression risk (florea2023hydatidiformmole—betweenchromosomal pages 9-11, joyce2024evaluationofbiomarkers pages 62-66).
- PHM: commonly ~0.5–1% (florea2023hydatidiformmole—betweenchromosomal pages 9-11, joyce2024evaluationofbiomarkers pages 62-66). Broader ranges are reported in some summaries (e.g., 7–30% vs 2.5–7.5%) (senat2024gestationaltrophoblasticdisease pages 4-7).
9.3 Inheritance (recurrent/familial forms)
Familial recurrent HM is typically autosomal recessive due to maternal-effect genes such as NLRP7 and KHDC3L (nasser2024molecularbasisof pages 5-6, kocabey2023highriskof pages 1-2).
10. Diagnostics
10.1 Clinical and laboratory tests
- β-hCG is the key biomarker for diagnosis/surveillance; CHM often shows very high hCG (>100,000 U/L) (joyce2024evaluationofbiomarkers pages 62-66).
10.2 Imaging
- Transvaginal ultrasound: “snowstorm/blizzard” and cystic/grape-like patterns are classic descriptors (senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4, riccio2023recurrenthydatidiformmoles pages 1-2).
10.3 Pathology (histopathology) and immunohistochemistry
- One source explicitly states: “Histopathological examination… remain[s] the gold standard for the diagnosis of molar pregnancy.” (joyce2024evaluationofbiomarkers pages 62-66)
- p57 (CDKN1C) immunohistochemistry: CHM typically shows loss/absence of p57, whereas PHM retains p57 expression (gonzalez2024gestationaltrophoblasticdisease pages 2-4, joyce2024evaluationofbiomarkers pages 62-66).
10.4 Molecular diagnosis and “gold standard” statements
- STR genotyping is explicitly called “the gold standard for making the correct diagnosis” in a 2024 GTD review (senat2024gestationaltrophoblasticdisease pages 4-7).
- STR genotyping is also described as an ancillary method to establish paternal allele patterns supporting CHM (florea2023hydatidiformmole—betweenchromosomal pages 2-4).
10.5 Post-molar GTN diagnostic criteria (FIGO hCG criteria)
FIGO criteria are summarized in multiple sources, including: - hCG plateau (four measurements over ≥3 weeks) and hCG rise (three weekly measurements over ≥2 weeks), or histologic choriocarcinoma (larsson2025treatmentoutcomesand pages 1-2, senat2024gestationaltrophoblasticdisease pages 4-7).
10.6 Differential diagnosis (selected)
- Hydropic abortus and other “molar mimics” are emphasized as key differentials; morphology alone can be insufficient, with one review stating ~50% of partial moles may not be diagnosed by routine histology (florea2023hydatidiformmole—betweenchromosomal pages 2-4).
11. Outcome / Prognosis
11.1 Remission/cure
Gestational trophoblastic neoplasia (GTN) has very high cure rates with modern management: - A 2024 source states “GTN is the most curative of all gynaecological malignancies with cure rates approaching 100% even in the presence of metastatic disease.” (joyce2024evaluationofbiomarkers pages 62-66) - A Swedish population-based cohort of 185 GTN patients reported primary complete remission 98.4% and relapse 3.2% (larsson2025treatmentoutcomesand pages 1-2). - A 2025 Shanghai cohort of 506 HM patients found 8.3% progressed to post-molar GTN and all achieved complete response after treatment (zhu2025demographicsriskfactors pages 1-2).
11.2 Prognostic factors for progression
Risk factors for post-molar GTN include very high hCG (>100,000 mIU/mL), uterine size larger than expected, large theca lutein cysts, and older maternal age (florea2023hydatidiformmole—betweenchromosomal pages 9-11, zhu2025demographicsriskfactors pages 1-2).
12. Treatment
12.1 Standard treatment for hydatidiform mole (fertility-preserving)
- Ultrasound-guided uterine evacuation (suction dilation & curettage / D&C) is standard for patients wishing to preserve fertility (gonzalez2024gestationaltrophoblasticdisease pages 4-5, riccio2023recurrenthydatidiformmoles pages 1-2).
12.2 Post-evacuation surveillance
- β-hCG monitoring: every 1–2 weeks until normalization; after normalization, monthly for 6 months for CHM; for PHM, one additional monthly normal measurement is recommended (gonzalez2024gestationaltrophoblasticdisease pages 2-4, gonzalez2024gestationaltrophoblasticdisease pages 4-5).
12.3 Hysterectomy
- For those not desiring future fertility, hysterectomy with salpingectomy is recommended in one review and may reduce subsequent GTN risk by ~80% (gonzalez2024gestationaltrophoblasticdisease pages 4-5).
- In low-risk GTN, therapeutic hysterectomy shortened time to hCG normalization (48 vs 74 days) in a population-based cohort (larsson2025treatmentoutcomesand pages 1-2).
12.4 Chemotherapy (for GTN)
- Management of GTN includes chemotherapy guided by risk stratification systems (FIGO/WHO) (larsson2025treatmentoutcomesand pages 1-2, senat2024gestationaltrophoblasticdisease pages 4-7).
- In recurrent HM with NLRP7 pathogenic variants, low-risk GTN was treated with single-agent methotrexate, with subsequent β-hCG normalization (kocabey2023highriskof pages 2-4).
Suggested MAXO terms (examples): uterine evacuation (suction curettage), hysterectomy, chemotherapy (methotrexate-based), serial hCG monitoring.
13. Prevention
No vaccine or primary prevention strategies were established in the retrieved evidence corpus. Secondary prevention relies on timely diagnosis, complete evacuation, and structured hCG surveillance to detect post-molar GTN early (gonzalez2024gestationaltrophoblasticdisease pages 2-4, senat2024gestationaltrophoblasticdisease pages 4-7).
14. Other Species / Natural Disease
Not addressed in the retrieved evidence corpus.
15. Model Organisms
Not addressed in the retrieved evidence corpus.
Recent developments & “latest research” highlights (2023–2025 evidence in this corpus)
- Precision diagnosis emphasis: STR genotyping explicitly described as the diagnostic “gold standard” in a 2024 review (senat2024gestationaltrophoblasticdisease pages 4-7), reflecting ongoing movement toward genetically anchored diagnosis.
- Expanded IHC adjunct panels: Beyond p57, an IHC study tested imprinted genes and found RB1 and TSSC3 positive in 100% PHM/non-molar cases but only in a minority of CHM, supporting their adjunctive role when molecular testing is limited (chia2023diagnosticutilityof pages 1-2).
- Risk prediction modeling (real-world implementation): A 2019–2023 Shanghai cohort (n=506) developed and evaluated multivariable predictors of post-molar GTN incorporating age, β-hCG ratio, and ultrasound characteristics, and also reported reproductive outcomes after HM (zhu2025demographicsriskfactors pages 1-2).
Embedded summary tables (for knowledge base curation)
| Concept | Details | Source |
|---|---|---|
| Disease name | Hydatidiform mole (HM); a gestational trophoblastic disease classified into complete hydatidiform mole (CHM) and partial hydatidiform mole (PHM) | (senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4, joyce2024evaluationofbiomarkers pages 62-66) |
| Common synonyms / related terms | Molar pregnancy; complete mole; partial mole; HM/CHM/PHM; post-molar gestational trophoblastic neoplasia (GTN) refers to neoplastic progression after HM | (senat2024gestationaltrophoblasticdisease pages 4-7, larsson2025treatmentoutcomesand pages 1-2, joyce2024evaluationofbiomarkers pages 62-66) |
| Classification framework | Genetic classification distinguishes CHM (paternal-only genome) from PHM (triploid conceptus with maternal + paternal contribution); FIGO hCG criteria are used for post-molar GTN diagnosis/risk assessment | (senat2024gestationaltrophoblasticdisease pages 4-7, larsson2025treatmentoutcomesand pages 1-2, gonzalez2024gestationaltrophoblasticdisease pages 2-4) |
| ICD / diagnostic codes | ICD-10 code explicitly reported: non-specified hydatidiform mole O01.9; additional GTN-related codes reported include invasive mole D39.2A, PSTT D39.2C, choriocarcinoma C58.9, ETT morphology codes 91043/91053/m91053 | (larsson2025treatmentoutcomesand pages 1-2) |
| Complete hydatidiform mole (CHM): core genetics | Usually diploid, most commonly 46,XX; androgenetic/paternal-only genome; typically arises from fertilization of an empty ovum by one sperm with duplication or by two sperm | (senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4, gonzalez2024gestationaltrophoblasticdisease pages 1-2) |
| Partial hydatidiform mole (PHM): core genetics | Usually triploid, commonly 69,XXY (also 69,XXX/69,XYY reported); diandric triploidy with maternal and paternal contribution, often from dispermy of a normal ovum | (senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4, gonzalez2024gestationaltrophoblasticdisease pages 1-2) |
| p57 immunostaining pattern in CHM | Loss/absence of nuclear p57 expression in villous cytotrophoblast and stromal cells is characteristic of CHM because maternal genome contribution is absent | (gonzalez2024gestationaltrophoblasticdisease pages 1-2, joyce2024evaluationofbiomarkers pages 62-66, gonzalez2024gestationaltrophoblasticdisease pages 2-4) |
| p57 immunostaining pattern in PHM | Retained/intact nuclear p57 expression is expected in PHM because maternal genome contribution is present | (gonzalez2024gestationaltrophoblasticdisease pages 1-2, joyce2024evaluationofbiomarkers pages 62-66, gonzalez2024gestationaltrophoblasticdisease pages 2-4) |
| Diagnostic gold standard / definitive diagnosis | STR genotyping is explicitly described as the gold standard for correct diagnosis in one 2024 review; another review states definitive diagnosis is made by histopathologic examination, with p57 and molecular testing used as ancillary/complementary tools | (senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4) |
| GTN progression risk after CHM | Reported progression risk to GTN is about 15–20%; some reviews cite broader ranges up to 7–30% or note post-CHM GTN risk as high as 25% in a study | (florea2023hydatidiformmole—betweenchromosomal pages 9-11, senat2024gestationaltrophoblasticdisease pages 4-7, gonzalez2024gestationaltrophoblasticdisease pages 2-4, joyce2024evaluationofbiomarkers pages 62-66) |
| GTN progression risk after PHM | Reported progression risk to GTN is about 0.5–1%; some reviews cite broader ranges up to 2.5–7.5% | (florea2023hydatidiformmole—betweenchromosomal pages 9-11, senat2024gestationaltrophoblasticdisease pages 4-7, joyce2024evaluationofbiomarkers pages 62-66) |
| hCG follow-up after evacuation | Serum beta-hCG should be monitored every 1–2 weeks until normal; after normalization, monthly monitoring for 6 months is recommended for CHM, while PHM requires one additional monthly normal measurement | (gonzalez2024gestationaltrophoblasticdisease pages 2-4) |
| Epidemiology snapshot | Incidence reported at ~0.57–1.1 per 1,000 pregnancies in Europe/North America/Oceania and ~2 per 1,000 in Japan/Southeast Asia; other review data cite 1–2 per 1,000 in Europe/North America and up to 10 per 1,000 in India/Indonesia | (senat2024gestationaltrophoblasticdisease pages 4-7, joyce2024evaluationofbiomarkers pages 62-66) |
| Prognosis / cure context | GTN is highly curable with modern management; overall cure rates are reported as exceeding 90%, and one review states cure rates approach 100% even with metastatic disease | (larsson2025treatmentoutcomesand pages 1-2, joyce2024evaluationofbiomarkers pages 62-66) |
Table: This table summarizes key terminology, diagnostic coding, and the most clinically important distinctions between complete and partial hydatidiform mole, including genetics, p57 staining, and GTN progression risk. It is useful as a compact reference for disease knowledge base curation and differential diagnosis.
| Category | Gene / marker | Inheritance / origin | Molecular mechanism | Example pathogenic variants / pattern | Key clinical notes | Evidence |
|---|---|---|---|---|---|---|
| Maternal-effect gene | NLRP7 | Typically autosomal recessive in familial recurrent hydatidiform mole (FRHM); affected conceptions are often diploid biparental | Oocyte maternal-effect gene; defective establishment/maintenance of maternal imprinting with placenta-specific methylation defects; reported associations with altered DNMT3A, LIN28B, ERVWE1, LINE-1, and STAT5A methylation/expression | c.2471+1G>A (canonical splice-site; homozygous), c.2571dupC, p.Ile858HisfsTer11 (frameshift; homozygous), c.2810+2T>G (splice-site); broader series show multiple homozygous or compound-heterozygous truncating/splice variants | Major cause of FRHM; reported in ~40–80% of FRHM/RHM cohorts. In a 113-patient series, all moles from patients with NLRP7/KHDC3L variants were diploid biparental. In a 3-case 2023 series, all NLRP7-positive recurrent cases progressed to GTN after evacuation and required single-agent methotrexate; one review notes only ~7% chance of normal live birth with biallelic NLRP7 variants, supporting counseling about oocyte donation | (kocabey2023highriskof pages 2-4, nasser2024molecularbasisof pages 5-6, florea2023hydatidiformmole—betweenchromosomal pages 8-9, kocabey2023highriskof pages 1-2, nguyen2018thegeneticsof pages 1-2) |
| Maternal-effect gene | KHDC3L | Typically autosomal recessive; affected conceptions classically diploid biparental | Maternal-effect / imprinting gene involved in oocyte competence; variants associated with abnormal genomic imprinting and recurrent biparental mole formation | No variant examples with c./p. notation were provided in the available context; review-level evidence cites protein-truncating mutations and p.M1V founder mutation | Accounts for roughly 5–14% of familial recurrent mole cases depending on cohort/review; testing is generally recommended after NLRP7 if NLRP7 is negative in recurrent HM workup | (nasser2024molecularbasisof pages 15-16, nasser2024molecularbasisof pages 5-6, florea2023hydatidiformmole—betweenchromosomal pages 8-9, kocabey2023highriskof pages 1-2, nguyen2018thegeneticsof pages 1-2) |
| Maternal-effect gene | PADI6 | Recessive maternal-effect etiology reported in recurrent HM / reproductive failure | SCMC-related maternal-effect dysfunction; linked to abnormal early embryogenesis and HM, with review evidence that missense variants may be milder than protein-truncating variants; contributes to imprinting/early developmental failure rather than classic sporadic androgenetic mole biology | Specific c./p. examples were not available in the provided context | Linked to primary female infertility, early embryonic arrest after ART, and hydatidiform mole; should be considered in recurrent/biparental mole differential when NLRP7/KHDC3L testing is unrevealing | (nasser2024molecularbasisof pages 15-16, florea2023hydatidiformmole—betweenchromosomal pages 8-9) |
| Genotype class | Diploid biparental HM | Maternal-effect gene-associated recurrent form | Presence of both maternal and paternal genomes despite complete-mole phenotype; reflects imprinting failure rather than androgenetic conception | Genotype pattern: diploid biparental | Strongly enriched in women with NLRP7/KHDC3L variants; in the 113-patient study, tissues from mutation-positive patients were all diploid biparental, whereas mutation-negative recurrent cases were heterogeneous | (nasser2024molecularbasisof pages 5-6, nguyen2018thegeneticsof pages 1-2) |
| Genotype class | Diploid androgenetic HM | Usually sporadic, non-maternal-effect form | Paternal-only genome, classic complete mole mechanism | Genotype pattern: diploid androgenetic monospermic | Seen commonly among mutation-negative recurrent/sporadic cases; generally distinct from biparental recurrent mole syndrome | (nguyen2018thegeneticsof pages 1-2) |
| Genotype class | Triploid dispermic HM | Usually sporadic partial mole biology | Diandric triploidy from dispermy; not the classic maternal-effect recurrent biparental mechanism | Genotype pattern: triploid dispermic | In mutation-negative recurrent cases, a substantial fraction of tissues were triploid dispermic; these patients tended to have fewer reproductive losses and more live births than mutation-positive patients | (florea2023hydatidiformmole—betweenchromosomal pages 8-9, nguyen2018thegeneticsof pages 1-2) |
| Diagnostic marker | RB1 | IHC adjunct marker; not a causal gene here | Paternally imprinted/maternally expressed pattern useful for distinguishing CHM from PHM/non-molar abortus when p57 is equivocal | Positive in 100% of PHM and non-molar abortuses; positive in only 10.3% of CHM | Useful adjunct to p57 in laboratories lacking molecular testing or in equivocal cases | (chia2023diagnosticutilityof pages 1-2) |
| Diagnostic marker | TSSC3 | IHC adjunct marker; not a causal gene here | Paternally imprinted/maternally expressed pattern useful for distinguishing CHM from PHM/non-molar abortus | Positive in 100% of PHM and non-molar abortuses; positive in only 31% of CHM | Useful adjunct to p57 for CHM vs PHM/non-molar distinction, especially where molecular genotyping is unavailable | (chia2023diagnosticutilityof pages 1-2) |
| Diagnostic marker | DOG1 | IHC adjunct evaluated in study | Tested as a possible adjunct marker | Uniformly negative in all cell types/case groups in the cited study | Not useful diagnostically in this setting based on available evidence | (chia2023diagnosticutilityof pages 1-2) |
| Diagnostic marker | DNMT1 / GATA3 | IHC adjuncts evaluated in study | Maternally imprinted marker expression assessed across villous/trophoblastic compartments | Expressed in all cases except one CHM with negative GATA3 | Less discriminatory than RB1/TSSC3 for routine CHM vs PHM separation in the cited cohort | (chia2023diagnosticutilityof pages 1-2) |
Table: This table summarizes the main maternal-effect genes and genotype classes implicated in hydatidiform mole, especially recurrent biparental forms, and adds key diagnostic immunohistochemical adjuncts beyond p57. It is useful for linking molecular etiology to recurrence risk, imprinting defects, and practical pathology workflows.
Visual evidence (diagnostic table)
A key diagnostic comparison table (CHM vs PHM) was retrieved as cropped images from Gonzalez et al. 2024 (gonzalez2024gestationaltrophoblasticdisease media 25fa70d0, gonzalez2024gestationaltrophoblasticdisease media e5bff0f9).
Evidence type notes
- Human clinical evidence: cohort outcomes, progression risk estimates, imaging/lab surveillance, and remission/relapse outcomes (larsson2025treatmentoutcomesand pages 1-2, zhu2025demographicsriskfactors pages 1-2, joyce2024evaluationofbiomarkers pages 62-66).
- Human pathology/molecular diagnostics evidence: p57 patterns, STR genotyping as gold standard, and adjunct IHC markers (senat2024gestationaltrophoblasticdisease pages 4-7, joyce2024evaluationofbiomarkers pages 62-66, chia2023diagnosticutilityof pages 1-2).
- Human genetic case-series evidence: NLRP7 variant examples and associated GTN progression in recurrent HM (kocabey2023highriskof pages 2-4, kocabey2023highriskof pages 1-2).
Direct quotes from abstracts (available in evidence)
- NLRP7/embryogenesis mechanism abstract quote: “NLRP7 dysfunctions affect embryonic development and lead to Hydatidiform Moles…” (nasser2024molecularbasisof pages 5-6)
(Additional abstract-quote extraction was limited by the specific full-text segments retrieved in this run; primary claims are otherwise evidence-cited above.)
References
-
(joyce2024evaluationofbiomarkers pages 62-66): CM Joyce. Evaluation of biomarkers for the diagnosis, management and. Unknown journal, 2024.
-
(senat2024gestationaltrophoblasticdisease pages 4-7): Hanna Senat, Patrycja Grabowska, Aleksandra Senat, Patrycja Bolla, Aleksandra Madej, and Zuzanna Marczyńska. Gestational trophoblastic disease a contemporary review of diagnostic and pathology. current challenge and future directions for gynecologists and obstetricians. Journal of Education, Health and Sport, 59:73-86, Feb 2024. URL: https://doi.org/10.12775/jehs.2024.59.005, doi:10.12775/jehs.2024.59.005. This article has 1 citations.
-
(gonzalez2024gestationaltrophoblasticdisease pages 2-4): Jeffrey Gonzalez, Meagan Popp, Stephanie Ocejo, Alvaro Abreu, Hisham F. Bahmad, and Robert Poppiti. Gestational trophoblastic disease: complete versus partial hydatidiform moles. Diseases, 12:159, Jul 2024. URL: https://doi.org/10.3390/diseases12070159, doi:10.3390/diseases12070159. This article has 23 citations.
-
(gonzalez2024gestationaltrophoblasticdisease pages 1-2): Jeffrey Gonzalez, Meagan Popp, Stephanie Ocejo, Alvaro Abreu, Hisham F. Bahmad, and Robert Poppiti. Gestational trophoblastic disease: complete versus partial hydatidiform moles. Diseases, 12:159, Jul 2024. URL: https://doi.org/10.3390/diseases12070159, doi:10.3390/diseases12070159. This article has 23 citations.
-
(larsson2025treatmentoutcomesand pages 1-2): Agnes Larsson, Emelie Wallin, Mats Nilsson, and Ulrika Joneborg. Treatment outcomes and the role of surgery in gestational trophoblastic neoplasia: a population-based cohort study. Acta Oncologica, 64:807-814, Jun 2025. URL: https://doi.org/10.2340/1651-226x.2025.43274, doi:10.2340/1651-226x.2025.43274. This article has 1 citations and is from a peer-reviewed journal.
-
(kocabey2023highriskof pages 1-2): M. Kocabey, I. Gulhan, A. Koc, T. Cankaya, V. Karatasli, and A. Ileri. High risk of gestational trophoblastic neoplasia development in recurrent hydatidiform moles with nlrp7 pathogenic variations. Balkan Journal of Medical Genetics : BJMG, 25:45-50, Dec 2023. URL: https://doi.org/10.2478/bjmg-2022-0025, doi:10.2478/bjmg-2022-0025. This article has 5 citations.
-
(zhu2025demographicsriskfactors pages 1-2): Tingting Zhu, Guohua Zhu, Jiahui Ma, Xiaojuan Yu, Tingting Chen, Xiang Tao, Li Sun, Xin Lu, and Yan Du. Demographics, risk factors associated with malignant progression, and pregnancy outcomes of hydatidiform mole: a retrospective cohort study in shanghai, china. Frontiers in Oncology, Jul 2025. URL: https://doi.org/10.3389/fonc.2025.1643590, doi:10.3389/fonc.2025.1643590. This article has 1 citations.
-
(florea2023hydatidiformmole—betweenchromosomal pages 8-9): Andreea Florea, Lavinia Caba, Ana-Maria Grigore, Lucian-Mihai Antoci, Mihaela Grigore, Mihaela I. Gramescu, and Eusebiu Vlad Gorduza. Hydatidiform mole—between chromosomal abnormality, uniparental disomy and monogenic variants: a narrative review. Life, 13:2314, Dec 2023. URL: https://doi.org/10.3390/life13122314, doi:10.3390/life13122314. This article has 13 citations.
-
(florea2023hydatidiformmole—betweenchromosomal pages 9-11): Andreea Florea, Lavinia Caba, Ana-Maria Grigore, Lucian-Mihai Antoci, Mihaela Grigore, Mihaela I. Gramescu, and Eusebiu Vlad Gorduza. Hydatidiform mole—between chromosomal abnormality, uniparental disomy and monogenic variants: a narrative review. Life, 13:2314, Dec 2023. URL: https://doi.org/10.3390/life13122314, doi:10.3390/life13122314. This article has 13 citations.
-
(riccio2023recurrenthydatidiformmoles pages 1-2): S. Riccio, F. Galanti, M. Scudo, L. Di Troia, M. G. Ferrillo, F. Manzara, P. Ianiri, and F. A. Battaglia. Recurrent hydatidiform moles: a clinical challenge—a case report and an update on management and therapeutical strategies. Case Reports in Obstetrics and Gynecology, 2023:1-5, Jun 2023. URL: https://doi.org/10.1155/2023/3752274, doi:10.1155/2023/3752274. This article has 4 citations.
-
(nguyen2018thegeneticsof pages 1-2): Ngoc Minh Phuong Nguyen, Yassemine Khawajkie, Nawel Mechtouf, Maryam Rezaei, Magali Breguet, Elvira Kurvinen, Sujatha Jagadeesh, Asli Ece Solmaz, Monica Aguinaga, Reda Hemida, Mehmet Ibrahim Harma, Cécile Rittore, Kurosh Rahimi, Jocelyne Arseneau, Karine Hovanes, Ronald Clisham, Tiffanee Lenzi, Bonnie Scurry, Marie-Claude Addor, Rashmi Bagga, Genevieve Girardet Nendaz, Vildana Finci, Gemma Poke, Leslie Grimes, Nerine Gregersen, Kayla York, Pierre-Adrien Bolze, Chirag Patel, Hossein Mozdarani, Jacques Puechberty, Jessica Scotchie, Majid Fardaei, Muge Harma, R. J. McKinlay Gardner, Trilochan Sahoo, Tracy Dudding-Byth, Radhika Srinivasan, Philippe Sauthier, and Rima Slim. The genetics of recurrent hydatidiform moles: new insights and lessons from a comprehensive analysis of 113 patients. Modern Pathology, 31:1116-1130, Jul 2018. URL: https://doi.org/10.1038/s41379-018-0031-9, doi:10.1038/s41379-018-0031-9. This article has 93 citations and is from a domain leading peer-reviewed journal.
-
(kocabey2023highriskof pages 2-4): M. Kocabey, I. Gulhan, A. Koc, T. Cankaya, V. Karatasli, and A. Ileri. High risk of gestational trophoblastic neoplasia development in recurrent hydatidiform moles with nlrp7 pathogenic variations. Balkan Journal of Medical Genetics : BJMG, 25:45-50, Dec 2023. URL: https://doi.org/10.2478/bjmg-2022-0025, doi:10.2478/bjmg-2022-0025. This article has 5 citations.
-
(nasser2024molecularbasisof pages 5-6): Shadha Nasser, Mohammed Bahutair, R. Dube, Manjunatha Goud, Bellary Kuruba, Rasha Khougali Abdelrahman Aziz, Attia Salama, Mohamed Anas, Mohamed Anas Mohamed Faruk Patni, Subhranshu Sekhar Kar, and Rakhee Kar. Molecular basis of hydatidiform moles—a systematic review. International Journal of Molecular Sciences, 25:8739, Aug 2024. URL: https://doi.org/10.3390/ijms25168739, doi:10.3390/ijms25168739. This article has 10 citations.
-
(nasser2024molecularbasisof pages 15-16): Shadha Nasser, Mohammed Bahutair, R. Dube, Manjunatha Goud, Bellary Kuruba, Rasha Khougali Abdelrahman Aziz, Attia Salama, Mohamed Anas, Mohamed Anas Mohamed Faruk Patni, Subhranshu Sekhar Kar, and Rakhee Kar. Molecular basis of hydatidiform moles—a systematic review. International Journal of Molecular Sciences, 25:8739, Aug 2024. URL: https://doi.org/10.3390/ijms25168739, doi:10.3390/ijms25168739. This article has 10 citations.
-
(florea2023hydatidiformmole—betweenchromosomal pages 2-4): Andreea Florea, Lavinia Caba, Ana-Maria Grigore, Lucian-Mihai Antoci, Mihaela Grigore, Mihaela I. Gramescu, and Eusebiu Vlad Gorduza. Hydatidiform mole—between chromosomal abnormality, uniparental disomy and monogenic variants: a narrative review. Life, 13:2314, Dec 2023. URL: https://doi.org/10.3390/life13122314, doi:10.3390/life13122314. This article has 13 citations.
-
(gonzalez2024gestationaltrophoblasticdisease pages 4-5): Jeffrey Gonzalez, Meagan Popp, Stephanie Ocejo, Alvaro Abreu, Hisham F. Bahmad, and Robert Poppiti. Gestational trophoblastic disease: complete versus partial hydatidiform moles. Diseases, 12:159, Jul 2024. URL: https://doi.org/10.3390/diseases12070159, doi:10.3390/diseases12070159. This article has 23 citations.
-
(chia2023diagnosticutilityof pages 1-2): Wai Kit Chia, Pik Yuen Chia, Nor Haslinda Abdul Aziz, Salwati Shuib, Muaatamarulain Mustangin, Yoke Kqueen Cheah, Teck Yee Khong, Yin Ping Wong, and Geok Chin Tan. Diagnostic utility of tssc3 and rb1 immunohistochemistry in hydatidiform mole. International Journal of Molecular Sciences, 24:9656, Jun 2023. URL: https://doi.org/10.3390/ijms24119656, doi:10.3390/ijms24119656. This article has 6 citations.
-
(gonzalez2024gestationaltrophoblasticdisease media 25fa70d0): Jeffrey Gonzalez, Meagan Popp, Stephanie Ocejo, Alvaro Abreu, Hisham F. Bahmad, and Robert Poppiti. Gestational trophoblastic disease: complete versus partial hydatidiform moles. Diseases, 12:159, Jul 2024. URL: https://doi.org/10.3390/diseases12070159, doi:10.3390/diseases12070159. This article has 23 citations.
-
(gonzalez2024gestationaltrophoblasticdisease media e5bff0f9): Jeffrey Gonzalez, Meagan Popp, Stephanie Ocejo, Alvaro Abreu, Hisham F. Bahmad, and Robert Poppiti. Gestational trophoblastic disease: complete versus partial hydatidiform moles. Diseases, 12:159, Jul 2024. URL: https://doi.org/10.3390/diseases12070159, doi:10.3390/diseases12070159. This article has 23 citations.