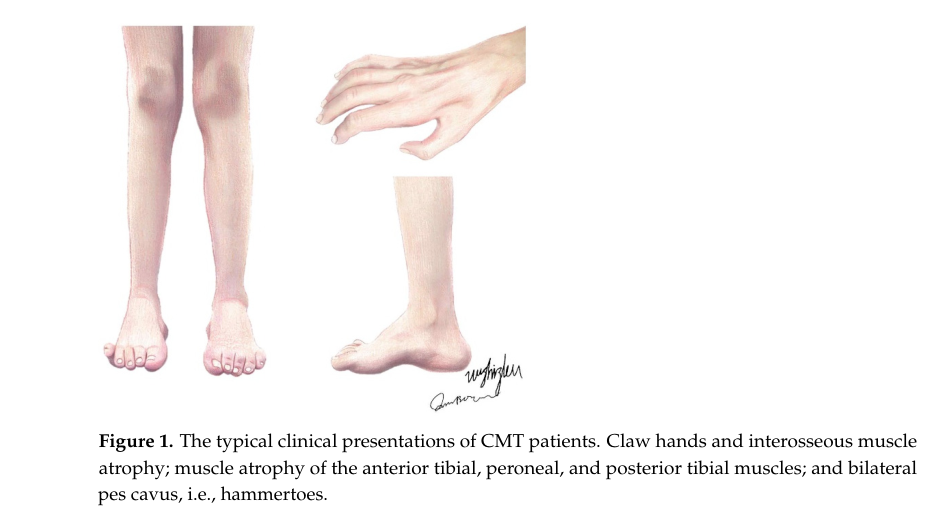
Charcot-Marie-Tooth Disease Type 1
Charcot-Marie-Tooth disease type 1 (CMT1) is the demyelinating compartment of Charcot-Marie-Tooth disease: a group of inherited peripheral neuropathies in which the primary lesion lies in the myelinating Schwann cell rather than the axon. Motor nerve conduction velocities are uniformly slowed (classically <38 m/s in the median nerve), reflecting dysmyelination and demyelination, and the characteristic clinical phenotype — slowly progressive distal weakness, sensory loss, pes cavus, and depressed reflexes — emerges from secondary, length-dependent axonal loss that follows the primary myelin defect. This entry collects the Schwann-cell / myelin mechanisms that converge on a single shared terminal node (demyelination with secondary axonal degeneration), distinct from the neuron-primary axonal mechanisms curated under Charcot-Marie-Tooth disease type 2. The dominant subtype is CMT1A, caused by a 1.4 Mb duplication on chromosome 17p11.2 containing PMP22; CMT1B is caused by MPZ mutations. The X-linked form CMTX1 (GJB1 / connexin-32) is electrophysiologically intermediate but is grouped here because its primary lesion is a Schwann-cell gap-junction defect; it forms the glia-axon bridge between the demyelinating and axonal compartments.
Ask OpenScientist
Ask a research question about Charcot-Marie-Tooth Disease Type 1. OpenScientist will conduct autonomous deep research using the Disorder Mechanisms Knowledge Base and PubMed literature (typically 10-30 minutes).
Do not include personal health information in your question. Questions and results are cached in your browser's local storage.
Inheritance
2Show evidence (1 reference)
Show evidence (1 reference)
Subtypes
8Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (7 references)
Show evidence (1 reference)
Show evidence (5 references)
Show evidence (3 references)
Show evidence (2 references)
Pathophysiology
9Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (2 references)
Show evidence (2 references)
Show evidence (2 references)
Show evidence (6 references)
Show evidence (6 references)
Show evidence (1 reference)
Pathograph
Phenotypes
6Limbs 1
Show evidence (1 reference)
Musculoskeletal 1
Show evidence (1 reference)
Nervous System 4
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Genetic Associations
8Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (1 reference)
Show evidence (2 references)
Show evidence (2 references)
Show evidence (2 references)
Show evidence (3 references)
Medical Actions
4Show evidence (1 reference)
Prevalence
1Show evidence (1 reference)
Source YAML
click to showname: Charcot-Marie-Tooth Disease Type 1
creation_date: "2026-06-11T00:00:00Z"
category: Mendelian
description: >-
Charcot-Marie-Tooth disease type 1 (CMT1) is the demyelinating compartment of
Charcot-Marie-Tooth disease: a group of inherited peripheral neuropathies in
which the primary lesion lies in the myelinating Schwann cell rather than the
axon. Motor nerve conduction velocities are uniformly slowed (classically
<38 m/s in the median nerve), reflecting dysmyelination and demyelination, and
the characteristic clinical phenotype — slowly progressive distal weakness,
sensory loss, pes cavus, and depressed reflexes — emerges from secondary,
length-dependent axonal loss that follows the primary myelin defect. This entry
collects the Schwann-cell / myelin mechanisms that converge on a single shared
terminal node (demyelination with secondary axonal degeneration), distinct from
the neuron-primary axonal mechanisms curated under Charcot-Marie-Tooth disease
type 2. The dominant subtype is CMT1A, caused by a 1.4 Mb duplication on
chromosome 17p11.2 containing PMP22; CMT1B is caused by MPZ mutations. The
X-linked form CMTX1 (GJB1 / connexin-32) is electrophysiologically intermediate
but is grouped here because its primary lesion is a Schwann-cell gap-junction
defect; it forms the glia-axon bridge between the demyelinating and axonal
compartments.
disease_term:
preferred_term: Demyelinating Charcot-Marie-Tooth disease (CMT1)
term:
id: MONDO:0019011
label: Charcot-Marie-Tooth disease type 1
parents:
- Charcot-Marie-Tooth disease
has_subtypes:
- name: CMT1A
display_name: CMT1A (PMP22 duplication)
subtype_term:
preferred_term: Charcot-Marie-Tooth disease type 1A
term:
id: MONDO:0007309
label: Charcot-Marie-Tooth disease type 1A
genes:
- preferred_term: PMP22
term:
id: hgnc:9118
label: PMP22
description: >-
The most common CMT subtype overall, caused by a 1.4 Mb tandem duplication of
chromosome 17p11.2 containing PMP22. PMP22 overexpression destabilizes compact
myelin, producing dysmyelination, demyelination, and onion-bulb formation.
evidence:
- reference: DOI:10.1093/brain/awae064
reference_title: "Whole genome sequencing increases the diagnostic rate in Charcot-Marie-Tooth disease"
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The most common genetic diagnosis was PMP22 duplication (CMT1A; 505/1165, 43.3%)"
explanation: Establishes PMP22 duplication / CMT1A as the dominant genetic cause within the demyelinating compartment.
- name: CMT1B
display_name: CMT1B (MPZ-related)
subtype_term:
preferred_term: Charcot-Marie-Tooth disease type 1B
term:
id: MONDO:0007307
label: Charcot-Marie-Tooth disease type 1B
genes:
- preferred_term: MPZ
term:
id: hgnc:7225
label: MPZ
description: >-
Caused by mutations in MPZ encoding myelin protein zero, the most abundant
peripheral myelin protein. Many MPZ variants trigger protein misfolding, the
unfolded protein response, and chronic Schwann-cell ER stress.
evidence:
- reference: DOI:10.3390/ijms25179227
reference_title: "Navigating the Landscape of CMT1B: Understanding Genetic Pathways, Disease Models, and Potential Therapeutic Approaches"
supports: SUPPORT
evidence_source: OTHER
snippet: "Mutations in the MPZ gene can lead to protein misfolding, unfolded protein response (UPR), endoplasmic reticulum (ER) stress, or protein mistrafficking."
explanation: Establishes UPR / ER stress as the canonical CMT1B (MPZ) Schwann-cell mechanism.
- name: CMTX1
display_name: CMTX1 (GJB1 / connexin-32, X-linked intermediate bridge)
genes:
- preferred_term: GJB1
term:
id: hgnc:4283
label: GJB1
description: >-
X-linked form caused by mutations in GJB1 encoding connexin-32, a Schwann-cell
gap-junction protein at the paranodes and Schmidt-Lanterman incisures. Grouped
in the demyelinating compartment because the primary lesion is a Schwann-cell
gap-junction defect, though its electrophysiology is intermediate and its
pathology shows both demyelination and axon loss — the glia-axon bridge between
the CMT1 and CMT2 compartments.
evidence:
- reference: DOI:10.1093/brain/awae064
reference_title: "Whole genome sequencing increases the diagnostic rate in Charcot-Marie-Tooth disease"
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "then GJB1 (CMTX1; 151/1165, 13.0%)"
explanation: GJB1 / CMTX1 is the second most common genetically resolved CMT subtype.
- name: CMT1C
display_name: CMT1C (LITAF/SIMPLE-related)
subtype_term:
preferred_term: Charcot-Marie-Tooth disease type 1C
term:
id: MONDO:0010995
label: Charcot-Marie-Tooth disease type 1C
genes:
- preferred_term: LITAF
term:
id: hgnc:16841
label: LITAF
description: >-
Autosomal dominant demyelinating CMT caused by missense mutations in LITAF,
also called SIMPLE, which encodes a small integral membrane protein of the
late endosome. The founding report mapped CMT1C to chromosome 16p13.1-p12.3
and found clustered missense mutations G112S, T115N and W116G in three
pedigrees. LITAF is widely expressed and its transcript level in sciatic
nerve does not change during development or in response to nerve injury,
which the founding report calls a stark contrast to the other known CMT1
genes, so the lesion is not a myelin structural protein defect; the
endolysosomal phenotype it produces is modeled in this entry's
pathophysiology. In a Korean cohort LITAF accounted for 0.59% of CMT1
patients, with milder disease than CMT1A.
inheritance:
- name: Autosomal dominant
evidence:
- reference: PMID:12525712
reference_title: "Mutation of a putative protein degradation gene LITAF/SIMPLE in Charcot-Marie-Tooth disease 1C."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The authors recently mapped an autosomal dominant demyelinating form of CMT type 1 (CMT1C) to chromosome 16p13.1-p12.3."
explanation: Establishes CMT1C as an autosomal dominant demyelinating CMT1 and sources its map location.
- reference: PMID:12525712
reference_title: "Mutation of a putative protein degradation gene LITAF/SIMPLE in Charcot-Marie-Tooth disease 1C."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The mutations associated with CMT1C were found to cluster, defining a domain of the LITAF protein having a critical role in peripheral nerve function."
explanation: Sources the clustering of the CMT1C mutations described here.
- reference: PMID:12525712
reference_title: "Mutation of a putative protein degradation gene LITAF/SIMPLE in Charcot-Marie-Tooth disease 1C."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The authors identified missense mutations (G112S, T115N, W116G) in the LITAFgene (lipopolysaccharide-induced tumor necrosis factor-alpha factor) in three CMT1C pedigrees."
explanation: Sources the three variants and the three pedigrees named in this description. The cached abstract runs "LITAFgene" together; the quote is reproduced as the source has it.
- reference: PMID:12525712
reference_title: "Mutation of a putative protein degradation gene LITAF/SIMPLE in Charcot-Marie-Tooth disease 1C."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The LITAF transcript is expressed in sciatic nerve, but its level of expression is not altered during development or in response to nerve injury."
explanation: Sources the expression statement in this description.
- reference: PMID:12525712
reference_title: "Mutation of a putative protein degradation gene LITAF/SIMPLE in Charcot-Marie-Tooth disease 1C."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "This finding is in stark contrast to that seen for other known genes that cause CMT1."
explanation: Sources the contrast with the other CMT1 genes drawn in this description, in the authors' own words.
- reference: PMID:35608774
reference_title: "Identification and clinical characterization of Charcot-Marie-Tooth disease type 1C patients with LITAF p.G112S mutation."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The frequency of CMT1C among CMT1 patients was 0.59%, which is similar to reports from Western populations."
explanation: Sources the 0.59% share of CMT1 cases quoted in this description.
- reference: PMID:35608774
reference_title: "Identification and clinical characterization of Charcot-Marie-Tooth disease type 1C patients with LITAF p.G112S mutation."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "CMT1C patients showed milder symptoms than CMT1A patients."
explanation: Sources the milder severity relative to CMT1A stated in this subtype description.
- name: CMT1D
display_name: CMT1D (EGR2-related)
subtype_term:
preferred_term: Charcot-Marie-Tooth disease type 1D
term:
id: MONDO:0011890
label: Charcot-Marie-Tooth disease type 1D
genes:
- preferred_term: EGR2
term:
id: hgnc:3239
label: EGR2
description: >-
Demyelinating CMT caused by mutations in EGR2 (Krox20), a transcription
factor required for Schwann-cell myelination. The same gene also causes
congenital hypomyelinating neuropathy and Dejerine-Sottas neuropathy at the
severe end of the spectrum.
evidence:
- reference: PMID:9537424
reference_title: "Mutations in the early growth response 2 (EGR2) gene are associated with hereditary myelinopathies."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "we have identified one recessive and two dominant missense mutations in EGR2 (within regions encoding conserved functional domains) in patients with congenital hypomyelinating neuropathy (CHN) and a family with Charcot-Marie-Tooth type 1 (CMT1)."
explanation: Establishes EGR2 mutations as a cause of demyelinating CMT1 (CMT1D).
- name: CMT1F
display_name: CMT1F (NEFL-related)
subtype_term:
preferred_term: Charcot-Marie-Tooth disease type 1F
term:
id: MONDO:0011902
label: Charcot-Marie-Tooth disease type 1F
genes:
- preferred_term: NEFL
term:
id: hgnc:7739
label: NEFL
description: >-
The demyelinating presentation of NEFL-related CMT. NEFL encodes
neurofilament light protein, one of five proteins that co-assemble to form
neurofilaments, and its variants produce three electrophysiological
presentations that the literature designates separately: demyelinating
(CMT1F), axonal (CMT2E) and dominant intermediate (DI-CMTG). Sural nerve
biopsies in NEFL-related CMT uniformly lose large myelinated fibres, and
onion bulbs or thin myelin sheaths were seen in two-thirds of 21 reported
biopsies, which is what places this presentation in the demyelinating
compartment.
The designation is a presentation rather than a mechanism, and the entry
records it as such. A review of the published NEFL cases found that the same
variant can be classified as CMT1F in one patient and CMT2E or DI-CMTG in
another, and argued that the underlying process is most likely primarily
axonal in every case. NEFL therefore crosses the compartment
boundary in both directions: the axonal presentation is curated as CMT2E on
Charcot-Marie-Tooth Disease Type 2, and the intermediate presentation has
its own entry, Charcot-Marie-Tooth Disease Dominant Intermediate G.
inheritance:
- name: Autosomal dominant
evidence:
- reference: PMID:35044100
reference_title: "Phenotypic heterogeneity in patients with NEFL-related Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Mutations in the neurofilament light polypeptide (NEFL) gene produce diverse clinical phenotypes, including demyelinating (CMT1F), axonal (CMT2E), and intermediate (CMTDIG) neuropathies."
explanation: Establishes CMT1F as the demyelinating presentation of NEFL-related CMT.
- reference: PMID:33993654
reference_title: "A review and analysis of the clinical literature on Charcot-Marie-Tooth disease caused by mutations in neurofilament protein L."
supports: SUPPORT
evidence_source: OTHER
quote_role: BACKGROUND
snippet: "One of the causative genes is NEFL on chromosome 8 which encodes neurofilament light protein (NEFL), one of five proteins that co-assemble to form neurofilaments."
explanation: Sources the protein identity stated at the start of this description; graded OTHER because the sentence states what the gene encodes and reports no experiment.
- reference: PMID:28501821
reference_title: "Genetic and clinical characteristics of NEFL-related Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Loss of large-myelinated fibres was a uniform feature in a total of 21 sural nerve biopsies and 'onion bulb' formations and/or thin myelin sheaths were observed in 14 (67%) of them."
explanation: Sources the biopsy findings quoted in this description, including the two-thirds figure for onion bulbs or thin myelin sheaths.
- reference: PMID:33993654
reference_title: "A review and analysis of the clinical literature on Charcot-Marie-Tooth disease caused by mutations in neurofilament protein L."
supports: SUPPORT
evidence_source: OTHER
quote_role: REVIEW_SYNTHESIS
snippet: "In fact, different individuals with the same mutation can be classified as having axonal, demyelinating, or dominant intermediate forms of the disease."
explanation: Sources the caveat that the CMT1F designation tracks the electrophysiological presentation rather than the variant.
- reference: PMID:33993654
reference_title: "A review and analysis of the clinical literature on Charcot-Marie-Tooth disease caused by mutations in neurofilament protein L."
supports: SUPPORT
evidence_source: OTHER
quote_role: REVIEW_SYNTHESIS
snippet: "This suggests that the classification of the disease as CMT2E, CMT1F or DI-CMTG has more to do with variable disease presentation than to differences in the underlying disease mechanism, which is most likely primarily axonal in all cases."
explanation: Sources this description's statement that the review argues the underlying process is most likely primarily axonal in every case.
- name: CMT1H
display_name: CMT1H (FBLN5-related, with skin and retinal involvement)
subtype_term:
preferred_term: Charcot-Marie-Tooth disease, demyelinating, type 1H
term:
id: MONDO:0030689
label: "Charcot-Marie-Tooth disease, demyelinating, IIA 1H"
description: >-
Autosomal dominant demyelinating CMT caused by heterozygous FBLN5 missense
variants. FBLN5 encodes fibulin-5, an extracellular matrix protein required for
elastic fibre assembly; the same gene causes recessive cutis laxa and is
associated with age-related macular degeneration. Reported CMT families combine
neuropathy with hyperextensible skin, and a mild-to-severe peripheral neuropathy
was found in most FBLN5-mutation carriers ascertained through macular
degeneration, so the subtype is best understood as one face of an
oculo-neuro-cutaneous phenotype.
genes:
- preferred_term: FBLN5
term:
id: hgnc:3602
label: FBLN5
evidence:
- reference: PMID:21576112
reference_title: "Fibulin-5 mutations link inherited neuropathies, age-related macular degeneration and hyperelastic skin."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "This study identifies fibulin-5 as a gene involved in Charcot-Marie-Tooth neuropathies and reveals heterozygous fibulin-5 mutations in 2% of our patients with age-related macular degeneration."
explanation: Establishes FBLN5 as a CMT gene and quantifies its co-occurrence with macular degeneration.
- reference: PMID:21576112
reference_title: "Fibulin-5 mutations link inherited neuropathies, age-related macular degeneration and hyperelastic skin."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Screening of 112 index probands with unclassified Charcot-Marie-Tooth neuropathies detected two further fibulin-5 missense mutations in two families with Charcot-Marie-Tooth disease and hyperextensible skin."
explanation: Sources the neuropathy-plus-hyperextensible-skin combination described for this subtype.
- reference: PMID:21576112
reference_title: "Fibulin-5 mutations link inherited neuropathies, age-related macular degeneration and hyperelastic skin."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "A mild to severe peripheral neuropathy was detected in the majority of patients with age-related macular degeneration carrying mutations in fibulin-5."
explanation: >-
Sources the statement that neuropathy is usual among FBLN5 carriers ascertained
through macular degeneration, which is why this subtype is described as one face
of an oculo-neuro-cutaneous phenotype.
- name: CMT1J
display_name: CMT1J (ITPR3-related)
subtype_term:
preferred_term: Charcot-Marie-Tooth disease, demyelinating, type 1J
term:
id: MONDO:0859311
label: "Charcot-Marie-Tooth disease, demyelinating, type 1J"
description: >-
Autosomal dominant CMT caused by ITPR3 variants, encoding the type 3 inositol
1,4,5-trisphosphate receptor. The reported autosomal dominant family had
symmetrical neuropathy with demyelinating and secondary axonal features from
around age 30, while a de novo p.Arg2524Cys case had demyelinating neuropathy
from age 4 with much faster progression, so severity within the subtype is wide.
genes:
- preferred_term: ITPR3
term:
id: hgnc:6182
label: ITPR3
evidence:
- reference: PMID:32949214
reference_title: "Dominant mutations in ITPR3 cause Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Here, we present genetic and functional evidence that ITPR3 is a Charcot-Marie-Tooth disease gene."
explanation: Establishes ITPR3 as a CMT gene on genetic and functional grounds.
- reference: PMID:32949214
reference_title: "Dominant mutations in ITPR3 cause Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Affected individuals in the autosomal dominant family had onset of symmetrical neuropathy with demyelinating and secondary axonal features at around age 30"
explanation: Sources the demyelinating-with-secondary-axonal electrophysiology that places this subtype in the CMT1 compartment.
pathophysiology:
- name: PMP22 Overexpression and Dysmyelination
conforms_to: "schwann_cell_myelin_maintenance#Myelin Gene Dosage or Structural Lesion in Schwann Cells"
description: >-
The most common cause of CMT (CMT1A) is a 1.4 Mb tandem duplication of
chromosome 17p11.2 containing the peripheral myelin protein 22 (PMP22) gene.
PMP22 overexpression destabilizes compact myelin and disrupts the structural
organization of the myelin sheath, causing dysmyelination, demyelination, and
characteristic onion-bulb formation from repeated Schwann-cell remyelination
attempts. Slowed nerve conduction follows, and chronic secondary axonal loss
eventually drives the clinical phenotype.
cell_types:
- preferred_term: Schwann cell
term:
id: CL:0002573
label: Schwann cell
biological_processes:
- preferred_term: Myelination in the peripheral nervous system
term:
id: GO:0022011
label: myelination in peripheral nervous system
modifier: DECREASED
genes:
- preferred_term: PMP22
term:
id: hgnc:9118
label: PMP22
downstream:
- target: Demyelination and Secondary Axonal Loss
description: >-
PMP22-dosage-driven dysmyelination produces demyelination and, over time,
length-dependent secondary axonal degeneration.
evidence:
- reference: DOI:10.1093/brain/awae064
reference_title: "Whole genome sequencing increases the diagnostic rate in Charcot-Marie-Tooth disease"
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The most common genetic diagnosis was PMP22 duplication (CMT1A; 505/1165, 43.3%)"
explanation: Establishes PMP22 duplication / CMT1A as the dominant genetic cause of demyelinating CMT.
- name: MPZ Misfolding and Schwann Cell ER Stress
conforms_to: "schwann_cell_myelin_maintenance#Schwann Cell Proteostatic Stress and Myelin Protein Mistrafficking"
description: >-
MPZ (myelin protein zero) mutations cause CMT1B. Many MPZ variants produce
protein misfolding that triggers the unfolded protein response (UPR) and
chronic endoplasmic reticulum (ER) stress in Schwann cells, or cause
mistrafficking of the mutant protein. The resulting myelin instability drives
the demyelinating CMT1B phenotype.
cell_types:
- preferred_term: Schwann cell
term:
id: CL:0002573
label: Schwann cell
biological_processes:
- preferred_term: Endoplasmic reticulum unfolded protein response
term:
id: GO:0030968
label: endoplasmic reticulum unfolded protein response
modifier: INCREASED
genes:
- preferred_term: MPZ
term:
id: hgnc:7225
label: MPZ
downstream:
- target: Demyelination and Secondary Axonal Loss
description: >-
Misfolded-MPZ-driven Schwann-cell ER stress destabilizes myelin, producing
demyelination and secondary axonal degeneration.
evidence:
- reference: DOI:10.3390/ijms25179227
reference_title: "Navigating the Landscape of CMT1B: Understanding Genetic Pathways, Disease Models, and Potential Therapeutic Approaches"
supports: SUPPORT
evidence_source: OTHER
snippet: "Mutations in the MPZ gene can lead to protein misfolding, unfolded protein response (UPR), endoplasmic reticulum (ER) stress, or protein mistrafficking."
explanation: Establishes UPR / ER stress as the canonical CMT1B disease mechanism.
- name: Connexin-32 Gap Junction Failure in CMTX1
conforms_to: "schwann_cell_myelin_maintenance#Myelin Gene Dosage or Structural Lesion in Schwann Cells"
description: >-
GJB1 mutations cause loss of function of connexin-32, which forms reflexive
gap-junction channels across the non-compact myelin of the paranodes and
Schmidt-Lanterman incisures, shortening the radial diffusion pathway between
the Schwann-cell body and the adaxonal cytoplasm. Loss of these channels
impairs Schwann-cell homeostasis and myelin maintenance, producing the
X-linked demyelinating-spectrum neuropathy CMTX1.
cell_types:
- preferred_term: Schwann cell
term:
id: CL:0002573
label: Schwann cell
biological_processes:
- preferred_term: Gap junction assembly
term:
id: GO:0016264
label: gap junction assembly
modifier: ABNORMAL
genes:
- preferred_term: GJB1
term:
id: hgnc:4283
label: GJB1
downstream:
- target: Demyelination and Secondary Axonal Loss
description: >-
Connexin-32 gap-junction failure impairs Schwann-cell homeostasis, producing
demyelination together with axon loss in CMTX1.
evidence:
- reference: PMID:30881289
reference_title: "Role of Connexin-Based Gap Junction Channels in Communication of Myelin Sheath in Schwann Cells."
supports: SUPPORT
evidence_source: OTHER
snippet: "Most GJB1 mutations cause disability through the loss of function of Cx32"
explanation: Establishes loss of function of connexin-32 (Cx32) as the dominant CMTX1 disease mechanism.
- name: Fibulin-5 Extracellular Matrix Defect
biological_scale: MOLECULAR
description: >-
FBLN5 encodes fibulin-5, a widely expressed extracellular matrix constituent
with an essential role in elastic fibre assembly; loss-of-function alleles
cause cutis laxa. Heterozygous missense variants segregate with demyelinating
CMT, and the same variant class produces concurrent pathology in eye and skin,
which is why FBLN5 families combine neuropathy with macular degeneration and
hyperextensible skin. The step from an
elastic-fibre defect to Schwann-cell demyelination is not established by the
cited work, and is recorded here as an unexplained gap rather than asserted.
molecular_functions:
- preferred_term: extracellular matrix structural constituent
term:
id: GO:0005201
label: extracellular matrix structural constituent
modifier: ABNORMAL
biological_processes:
- preferred_term: elastic fiber assembly
term:
id: GO:0048251
label: elastic fiber assembly
modifier: ABNORMAL
genes:
- preferred_term: FBLN5
term:
id: hgnc:3602
label: FBLN5
evidence:
- reference: PMID:21576112
reference_title: "Fibulin-5 mutations link inherited neuropathies, age-related macular degeneration and hyperelastic skin."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "A missense mutation in fibulin-5, encoding a widely expressed constituent of the extracellular matrix that has an essential role in elastic fibre assembly and has been shown to cause cutis laxa, was detected as the only novel non-synonymous sequence variant within the disease interval."
explanation: Sources both the fibulin-5 elastic-fibre role and its identification as the segregating variant in the CMT-linked interval.
- reference: PMID:21576112
reference_title: "Fibulin-5 mutations link inherited neuropathies, age-related macular degeneration and hyperelastic skin."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Furthermore, it adumbrates a new syndrome by linking concurrent pathologic alterations affecting peripheral nerves, eyes and skin to mutations in the fibulin-5 gene."
explanation: Supports the multi-tissue extracellular-matrix reading of the FBLN5 phenotype recorded in this node.
downstream:
- target: Demyelination and Secondary Axonal Loss
description: >-
FBLN5 variants segregate with demyelinating CMT, so the extracellular matrix
defect is upstream of the shared demyelinating terminal node; the intervening
Schwann-cell steps are not established in the cited work.
causal_link_type: INDIRECT_UNKNOWN_INTERMEDIATES
notes: CMT1H (FBLN5-related demyelinating CMT)
- name: ITPR3 Calcium Release Dysregulation
biological_scale: MOLECULAR
description: >-
ITPR3 encodes the type 3 inositol 1,4,5-trisphosphate receptor, an
endoplasmic-reticulum calcium release channel. Fibroblasts from a patient
carrying the dominant p.Val615Met variant show altered calcium transients,
which the authors interpret as a dominant-negative effect on receptor function,
implicating altered calcium homeostasis in the demyelinating neuropathy.
biological_processes:
- preferred_term: release of sequestered calcium ion into cytosol
term:
id: GO:0051209
label: release of sequestered calcium ion into cytosol
modifier: DYSREGULATED
genes:
- preferred_term: ITPR3
term:
id: hgnc:6182
label: ITPR3
evidence:
- reference: PMID:32949214
reference_title: "Dominant mutations in ITPR3 cause Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: IN_VITRO
snippet: "Altered Ca2+ -transients in p.Val615Met patient fibroblasts suggested that the variant has a dominant-negative effect on inositol 1,4,5-trisphosphate receptor type 3 function."
explanation: The functional measurement behind the calcium-release dysregulation asserted by this node.
- reference: PMID:32949214
reference_title: "Dominant mutations in ITPR3 cause Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Together with two previously identified variants, our report adds further evidence that ITPR3 is a disease-causing gene for CMT and indicates altered Ca2+ homeostasis in disease pathogenesis."
explanation: The authors' own statement that altered calcium homeostasis is the implicated pathogenic mechanism.
downstream:
- target: Demyelination and Secondary Axonal Loss
description: >-
Dysregulated inositol-trisphosphate-receptor calcium release precedes the
demyelinating neuropathy with secondary axonal features seen in ITPR3
families; the intervening steps are not established in the cited work.
causal_link_type: INDIRECT_UNKNOWN_INTERMEDIATES
notes: CMT1J (ITPR3-related CMT)
- name: EGR2 Schwann-Cell Myelination Program Failure
biological_scale: MOLECULAR
description: >-
EGR2, also called Krox20, is a Cys2His2 zinc-finger protein that binds DNA in
a sequence-specific manner and acts as a transcription factor, and stable
expression of its mouse orthologue is specifically associated with the onset
of peripheral myelination. Egr2-null mice arrest Schwann-cell
differentiation at an early stage, and missense mutations in the conserved
functional domains of human EGR2 were found in congenital hypomyelinating
neuropathy and in a CMT1 family. The lesion is therefore a failure of the
transcriptional programme that drives a Schwann cell into the myelinating
state, rather than a defect in a myelin structural protein.
genes:
- preferred_term: EGR2
term:
id: hgnc:3239
label: EGR2
cell_types:
- preferred_term: Schwann cell
term:
id: CL:0002573
label: Schwann cell
molecular_functions:
- preferred_term: DNA-binding transcription factor activity
term:
id: GO:0003700
label: DNA-binding transcription factor activity
modifier: DECREASED
biological_processes:
- preferred_term: Schwann cell differentiation
term:
id: GO:0014037
label: Schwann cell differentiation
modifier: DECREASED
evidence:
- reference: PMID:9537424
reference_title: "Mutations in the early growth response 2 (EGR2) gene are associated with hereditary myelinopathies."
supports: SUPPORT
evidence_source: MODEL_ORGANISM
snippet: "Egr2(-/-) mice display disrupted hindbrain segmentation and development, and a block of Schwann-cell differentiation at an early stage."
explanation: The knockout result behind this node's claim that EGR2 is required for Schwann cells to enter the myelinating state.
- reference: PMID:9537424
reference_title: "Mutations in the early growth response 2 (EGR2) gene are associated with hereditary myelinopathies."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "we have identified one recessive and two dominant missense mutations in EGR2 (within regions encoding conserved functional domains) in patients with congenital hypomyelinating neuropathy (CHN) and a family with Charcot-Marie-Tooth type 1 (CMT1)."
explanation: Establishes that human EGR2 missense mutations produce demyelinating CMT1 as well as congenital hypomyelinating neuropathy.
downstream:
- target: Demyelination and Secondary Axonal Loss
description: >-
Failure of the EGR2-dependent myelination programme leaves Schwann cells
unable to make and maintain compact myelin, producing the demyelinating
neuropathy of CMT1D.
causal_link_type: DIRECT
evidence:
- reference: PMID:9537424
reference_title: "Mutations in the early growth response 2 (EGR2) gene are associated with hereditary myelinopathies."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "we have identified one recessive and two dominant missense mutations in EGR2 (within regions encoding conserved functional domains) in patients with congenital hypomyelinating neuropathy (CHN) and a family with Charcot-Marie-Tooth type 1 (CMT1)."
explanation: Links EGR2 mutation to the hereditary myelinopathy phenotypes this edge terminates in.
notes: CMT1D (EGR2-related CMT)
- name: LITAF Endolysosomal Homeostasis Failure
biological_scale: CELLULAR
description: >-
LITAF, also called SIMPLE, is a small integral membrane protein of the late
endosome and lysosome, and autosomal dominant mutations in it cause CMT1C.
Primary fibroblasts from two CMT1C patients carrying different pathogenic
LITAF variants show vacuolation and enlargement of late endosomes and
lysosomes, and the same morphology follows knocking LITAF out of control
fibroblasts, which is consistent with loss of function. The same phenotype
occurs in CMT4J fibroblasts carrying FIG4 variants and is rescued in both by
a small-molecule activator of the lysosomal channel TRPML1, so LITAF and
FIG4 appear to act on one endolysosomal pathway. This lesion is unlike the
other CMT1 subtypes modeled here. LITAF is widely expressed, and its
transcript level in sciatic nerve is not altered during development or in
response to nerve injury, which the founding report calls a stark contrast to
the other known CMT1 genes.
genes:
- preferred_term: LITAF
term:
id: hgnc:16841
label: LITAF
molecular_functions:
- preferred_term: phospholipid binding
term:
id: GO:0005543
label: phospholipid binding
modifier: DECREASED
cellular_components:
- preferred_term: late endosome
term:
id: GO:0005770
label: late endosome
- preferred_term: lysosome
term:
id: GO:0005764
label: lysosome
evidence:
- reference: PMID:33059769
reference_title: "A dysfunctional endolysosomal pathway common to two sub-types of demyelinating Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: OTHER
quote_role: BACKGROUND
snippet: "Autosomal dominant mutations in LITAF are responsible for the rare demyelinating peripheral neuropathy, Charcot-Marie-Tooth disease type 1C (CMT1C)."
explanation: States the gene-disease relationship this node rests on; graded OTHER because the sentence reports no experiment, and BACKGROUND because it restates the founding genetic report rather than this paper's own result.
- reference: PMID:33059769
reference_title: "A dysfunctional endolysosomal pathway common to two sub-types of demyelinating Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: OTHER
quote_role: BACKGROUND
snippet: "membrane association is mediated by the C-terminal LITAF domain via a predicted hydrophobic helix and specific interactions with phosphoethanolamine (PE) head groups"
explanation: >-
The molecular activity this node binds as phospholipid binding. All the
CMT1C variants lie in and around that hydrophobic region, which is why
disrupting it is the proposed consequence. Graded OTHER and BACKGROUND
because the sentence states established protein biochemistry from work
this paper cites rather than reporting its own experiment.
- reference: PMID:33059769
reference_title: "A dysfunctional endolysosomal pathway common to two sub-types of demyelinating Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: IN_VITRO
snippet: "We observed the appearance of vacuolation/enlargement of late endocytic compartments (late endosomes and lysosomes)."
explanation: The measured cellular phenotype in CMT1C patient fibroblasts behind this node's claim.
- reference: PMID:33059769
reference_title: "A dysfunctional endolysosomal pathway common to two sub-types of demyelinating Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: IN_VITRO
snippet: "This vacuolation was also observed after knocking out LITAF from either control human fibroblasts or from the CMT1C patient-derived cells, consistent with it being the result of loss-of-function mutations in the CMT1C fibroblasts."
explanation: Sources the loss-of-function reading of the CMT1C variants stated in this node.
- reference: PMID:12525712
reference_title: "Mutation of a putative protein degradation gene LITAF/SIMPLE in Charcot-Marie-Tooth disease 1C."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The LITAF transcript is expressed in sciatic nerve, but its level of expression is not altered during development or in response to nerve injury."
explanation: Sources the expression statement at the end of this node description.
- reference: PMID:12525712
reference_title: "Mutation of a putative protein degradation gene LITAF/SIMPLE in Charcot-Marie-Tooth disease 1C."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "This finding is in stark contrast to that seen for other known genes that cause CMT1."
explanation: The authors' own characterization of that contrast, which this node description attributes to them.
downstream:
- target: Demyelination and Secondary Axonal Loss
description: >-
Loss of LITAF-dependent endolysosomal homeostasis precedes the
demyelinating neuropathy of CMT1C; the steps between the fibroblast
compartment phenotype and Schwann-cell demyelination are not established
in the cited work, which notes that the experiments were done in
fibroblasts rather than in nerve.
causal_link_type: INDIRECT_UNKNOWN_INTERMEDIATES
evidence:
- reference: PMID:33059769
reference_title: "A dysfunctional endolysosomal pathway common to two sub-types of demyelinating Charcot-Marie-Tooth disease."
supports: SUPPORT
directness: INDIRECT
evidence_source: IN_VITRO
snippet: "Although our experiments were on human fibroblasts, they have implications for our understanding of the molecular pathogenesis and approaches to therapy in two subtypes of demyelinating Charcot-Marie-Tooth disease."
explanation: The authors' own statement of how far the fibroblast result reaches toward the demyelinating phenotype, which is why this edge is typed with unknown intermediates.
notes: CMT1C (LITAF/SIMPLE-related CMT)
- name: NEFL Neurofilament Assembly and Transport Defect
biological_scale: MOLECULAR
description: >-
NEFL encodes neurofilament light protein, one of five proteins that
co-assemble to form neurofilaments, and its variants are classified as demyelinating
(CMT1F), axonal (CMT2E) or dominant intermediate (DI-CMTG) according to
electrodiagnostic findings. Many reports find that missense mutations in
NEFL disrupt neurofilament assembly in cultured cells. How that produces the
absence of neurofilaments from axons is less settled: the review collating
the published cases calls it less clear, and says only that it seems likely
to involve defective assembly and/or transport, which is why this node is
named for both and asserts neither alone. The same review argues that the
CMT1F, CMT2E and DI-CMTG classification reflects variable presentation
rather than different mechanisms, and that the process is most likely
primarily axonal in all cases; the node is placed in this entry because
sural nerve biopsies in NEFL-related CMT show onion bulbs or thin myelin
sheaths in two-thirds of cases alongside uniform loss of large myelinated
fibres.
genes:
- preferred_term: NEFL
term:
id: hgnc:7739
label: NEFL
molecular_functions:
- preferred_term: structural molecule activity
term:
id: GO:0005198
label: structural molecule activity
modifier: DECREASED
cellular_components:
- preferred_term: neurofilament
term:
id: GO:0005883
label: neurofilament
biological_processes:
- preferred_term: intermediate filament organization
term:
id: GO:0045109
label: intermediate filament organization
modifier: DECREASED
evidence:
- reference: PMID:35044100
reference_title: "Phenotypic heterogeneity in patients with NEFL-related Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Mutations in the neurofilament light polypeptide (NEFL) gene produce diverse clinical phenotypes, including demyelinating (CMT1F), axonal (CMT2E), and intermediate (CMTDIG) neuropathies."
explanation: Establishes that NEFL variants include a demyelinating presentation, which is what places this node in this entry.
- reference: PMID:33993654
reference_title: "A review and analysis of the clinical literature on Charcot-Marie-Tooth disease caused by mutations in neurofilament protein L."
supports: SUPPORT
evidence_source: OTHER
quote_role: BACKGROUND
snippet: "One of the causative genes is NEFL on chromosome 8 which encodes neurofilament light protein (NEFL), one of five proteins that co-assemble to form neurofilaments."
explanation: Sources the protein identity stated at the start of this node, and the structural-constituent reading behind its molecular function; graded OTHER because the sentence states what the gene encodes and reports no experiment.
- reference: PMID:33993654
reference_title: "A review and analysis of the clinical literature on Charcot-Marie-Tooth disease caused by mutations in neurofilament protein L."
supports: SUPPORT
evidence_source: IN_VITRO
quote_role: REVIEW_SYNTHESIS
snippet: "There are many reports that missense mutations in NEFL disrupt neurofilament assembly in cultured cells"
explanation: The assembly defect this node is named for, as the review summarizes the cultured-cell work that shows it.
- reference: PMID:33993654
reference_title: "A review and analysis of the clinical literature on Charcot-Marie-Tooth disease caused by mutations in neurofilament protein L."
supports: SUPPORT
evidence_source: OTHER
quote_role: REVIEW_SYNTHESIS
snippet: "How dominant missense mutations in NEFL result in the absence of neurofilaments from axons is less clear, but it seems likely to involve defective neurofilament assembly and/or transport."
explanation: >-
The hedge this node records: the step from disrupted assembly in culture to
absent axonal neurofilaments in patients is not settled, and the review
names assembly and transport together rather than choosing between them.
- reference: PMID:28501821
reference_title: "Genetic and clinical characteristics of NEFL-related Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Loss of large-myelinated fibres was a uniform feature in a total of 21 sural nerve biopsies and 'onion bulb' formations and/or thin myelin sheaths were observed in 14 (67%) of them."
explanation: The biopsy series behind the myelin findings asserted by this node.
- reference: PMID:33993654
reference_title: "A review and analysis of the clinical literature on Charcot-Marie-Tooth disease caused by mutations in neurofilament protein L."
supports: SUPPORT
evidence_source: OTHER
quote_role: REVIEW_SYNTHESIS
snippet: "This suggests that the classification of the disease as CMT2E, CMT1F or DI-CMTG has more to do with variable disease presentation than to differences in the underlying disease mechanism, which is most likely primarily axonal in all cases."
explanation: The review conclusion this node records as a caveat on treating CMT1F as a mechanistically separate lesion.
downstream:
- target: Demyelination and Secondary Axonal Loss
description: >-
Disordered neurofilament assembly and transport produce the mixed
demyelinating and axonal picture of NEFL-related CMT, with loss of large
myelinated fibres and onion-bulb formation on biopsy.
causal_link_type: DIRECT
evidence:
- reference: PMID:28501821
reference_title: "Genetic and clinical characteristics of NEFL-related Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Loss of large-myelinated fibres was a uniform feature in a total of 21 sural nerve biopsies and 'onion bulb' formations and/or thin myelin sheaths were observed in 14 (67%) of them."
explanation: The nerve pathology connecting the NEFL lesion to the shared demyelinating terminal node.
notes: CMT1F (NEFL-related CMT, demyelinating presentation)
- name: Demyelination and Secondary Axonal Loss
conforms_to: "peripheral_axonal_degeneration#Distal Axonal Degeneration and Demyelination"
description: >-
The shared terminal node of the demyelinating compartment. Primary Schwann-cell
and myelin defects (PMP22 dosage, MPZ misfolding, connexin-32 gap-junction
failure) converge on segmental demyelination and repeated remyelination
(onion-bulb formation), which over time produces length-dependent secondary
axonal degeneration. It is this secondary axonal loss, affecting the longest
motor and sensory fibers first, that determines the progressive clinical
deficit shared with the axonal compartment.
cell_types:
- preferred_term: Schwann cell
term:
id: CL:0002573
label: Schwann cell
- preferred_term: Sensory neuron of peripheral nervous system
term:
id: CL:0000101
label: sensory neuron
biological_processes:
- preferred_term: Myelination in the peripheral nervous system
term:
id: GO:0022011
label: myelination in peripheral nervous system
modifier: DECREASED
downstream:
- target: Decreased Nerve Conduction Velocity
description: >
Segmental demyelination slows saltatory conduction across peripheral
nerves.
causal_link_type: DIRECT
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Motor nerve conduction velocity (MNCV) was uniformly reduced in all nerves, and was < or = 33 m/s in the median nerve for all patients."
explanation: >
The CMT1A cohort directly supports slowed motor nerve conduction as the
electrophysiologic consequence of the demyelinating CMT1 lesion.
- target: Distal Muscle Weakness
description: >
Length-dependent secondary axonal loss in motor fibers produces distal
lower-limb weakness and wasting.
causal_link_type: DIRECT
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The predominant clinical signs were muscle weakness and wasting in the lower limbs."
explanation: >
The 119-case CMT1A cohort identifies distal lower-limb weakness and
wasting as predominant clinical signs.
- target: Pes Cavus
description: >
Chronic distal motor imbalance from hereditary peripheral neuropathy
produces cavus foot deformity.
causal_link_type: INDIRECT_KNOWN_INTERMEDIATES
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "None of the patients was normal on clinical examination and all presented at least pes cavus or ankle jerk areflexia."
explanation: >
The cohort supports pes cavus as a common examination finding in CMT1A.
- target: Decreased Tendon Reflexes
description: >
Peripheral demyelinating neuropathy and secondary axonal dysfunction
reduce ankle tendon reflexes.
causal_link_type: DIRECT
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "None of the patients was normal on clinical examination and all presented at least pes cavus or ankle jerk areflexia."
explanation: >
The cohort supports ankle-jerk areflexia as a CMT1A examination
finding.
- target: Distal Sensory Loss
description: >
Sensory fiber involvement in the demyelinating neuropathy produces distal
sensory impairment.
causal_link_type: DIRECT
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Sensory potentials were abnormal in all cases, even where there was no clinical sensory loss."
explanation: >
Abnormal sensory potentials in all cases support sensory-fiber
involvement in CMT1A.
- target: Onion Bulb Formation
description: >
Repeated cycles of demyelination and remyelination leave concentric
Schwann-cell processes around affected axons, the histological hallmark of
chronic demyelinating neuropathy.
causal_link_type: DIRECT
evidence:
- reference: PMID:28501821
reference_title: "Genetic and clinical characteristics of NEFL-related Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Loss of large-myelinated fibres was a uniform feature in a total of 21 sural nerve biopsies and 'onion bulb' formations and/or thin myelin sheaths were observed in 14 (67%) of them."
explanation: >-
Onion bulbs alongside loss of large myelinated fibres in sural nerve
biopsies. The cohort is NEFL-related CMT, whose presentations are mostly
axonal, so this is the histology of the demyelinating component rather
than of a CMT1A series.
evidence:
- reference: PMID:30881289
reference_title: "Role of Connexin-Based Gap Junction Channels in Communication of Myelin Sheath in Schwann Cells."
supports: SUPPORT
evidence_source: OTHER
snippet: "Typically, the pathophysiology of CMTX1 includes features of both demyelination and axon loss"
explanation: Supports the convergence of demyelinating CMT mechanisms on combined demyelination and secondary axonal loss.
phenotypes:
- category: Neurologic
name: Distal Muscle Weakness
diagnostic: true
phenotype_term:
preferred_term: Distal muscle weakness
term:
id: HP:0002460
label: Distal muscle weakness
clinical_course: PROGRESSIVE
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The predominant clinical signs were muscle weakness and wasting in the lower limbs."
explanation: 119-case CMT1A study identifies distal lower-limb muscle weakness as the predominant clinical sign.
- category: Neurologic
name: Onion Bulb Formation
description: >-
Concentric Schwann-cell and fibroblast processes around demyelinated and
remyelinated axons on nerve biopsy, the histological hallmark of chronic
demyelinating neuropathy and a feature that distinguishes CMT1 from axonal CMT2.
phenotype_term:
preferred_term: Onion bulb formation
term:
id: HP:0003383
label: Onion bulb formation
- category: Musculoskeletal
name: Pes Cavus
phenotype_term:
preferred_term: Pes cavus
term:
id: HP:0001761
label: Pes cavus
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "None of the patients was normal on clinical examination and all presented at least pes cavus or ankle jerk areflexia."
explanation: In a 119-case CMT1A cohort, every patient had at least pes cavus or ankle areflexia on examination.
- category: Neurologic
name: Decreased Tendon Reflexes
phenotype_term:
preferred_term: Hyporeflexia
term:
id: HP:0001265
label: Hyporeflexia
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "None of the patients was normal on clinical examination and all presented at least pes cavus or ankle jerk areflexia."
explanation: Ankle-jerk areflexia was a near-universal examination finding in this CMT1A cohort.
- category: Neurologic
name: Distal Sensory Loss
phenotype_term:
preferred_term: Distal sensory impairment
term:
id: HP:0002936
label: Distal sensory impairment
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Sensory potentials were abnormal in all cases, even where there was no clinical sensory loss."
explanation: Sensory nerve potentials were abnormal in all CMT1A cases, evidencing the sensory component of the neuropathy.
- category: Neurophysiologic
name: Decreased Nerve Conduction Velocity
description: >-
Uniformly slowed motor nerve conduction is the defining electrophysiologic
feature of the demyelinating CMT1 compartment.
phenotype_term:
preferred_term: Decreased nerve conduction velocity
term:
id: HP:0000762
label: Decreased nerve conduction velocity
evidence:
- reference: PMID:9183252
reference_title: "Charcot-Marie-Tooth disease type 1A with 17p11.2 duplication. Clinical and electrophysiological phenotype study and factors influencing disease severity in 119 cases."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Motor nerve conduction velocity (MNCV) was uniformly reduced in all nerves, and was < or = 33 m/s in the median nerve for all patients."
explanation: >
A 119-case CMT1A cohort directly reports uniformly reduced motor nerve
conduction velocity.
genetic:
- name: PMP22
gene_term:
preferred_term: PMP22
term:
id: hgnc:9118
label: PMP22
association: Causal
subtype: CMT1A
notes: >-
A 1.4 Mb tandem duplication of 17p11.2 containing PMP22 causes CMT1A, the
single most common CMT genotype. PMP22 point mutations cause rarer
demyelinating forms; the reciprocal deletion causes HNPP (curated separately).
evidence:
- reference: DOI:10.1093/brain/awae064
reference_title: "Whole genome sequencing increases the diagnostic rate in Charcot-Marie-Tooth disease"
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The most common genetic diagnosis was PMP22 duplication (CMT1A; 505/1165, 43.3%)"
explanation: PMP22 duplication is the dominant genetic cause of demyelinating CMT.
- name: MPZ
gene_term:
preferred_term: MPZ
term:
id: hgnc:7225
label: MPZ
association: Causal
subtype: CMT1B
notes: >-
MPZ (myelin protein zero) is the most abundant peripheral myelin protein.
Mutations cause CMT1B; many trigger protein misfolding, UPR, and chronic ER
stress in Schwann cells.
evidence:
- reference: DOI:10.3390/ijms25179227
reference_title: "Navigating the Landscape of CMT1B: Understanding Genetic Pathways, Disease Models, and Potential Therapeutic Approaches"
supports: SUPPORT
evidence_source: OTHER
snippet: "Mutations in the MPZ gene can lead to protein misfolding, unfolded protein response (UPR), endoplasmic reticulum (ER) stress, or protein mistrafficking."
explanation: Establishes the MPZ misfolding / ER-stress mechanism in CMT1B.
- name: GJB1
gene_term:
preferred_term: GJB1
term:
id: hgnc:4283
label: GJB1
association: Causal
subtype: CMTX1
notes: >-
GJB1 encodes connexin-32, expressed in Schwann cells at the paranodal gap
junctions and Schmidt-Lanterman incisures. X-linked (CMTX1), the second most
common genetic cause of CMT.
evidence:
- reference: DOI:10.1093/brain/awae064
reference_title: "Whole genome sequencing increases the diagnostic rate in Charcot-Marie-Tooth disease"
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "then GJB1 (CMTX1; 151/1165, 13.0%)"
explanation: GJB1 / CMTX1 is the second most common genetically resolved CMT subtype.
- name: EGR2
gene_term:
preferred_term: EGR2
term:
id: hgnc:3239
label: EGR2
association: Causal
subtype: CMT1D
notes: >-
EGR2 (Krox20) is a transcription factor required for Schwann-cell
myelination. Dominant mutations cause demyelinating CMT1D; recessive and
other variants cause congenital hypomyelinating neuropathy and
Dejerine-Sottas neuropathy.
evidence:
- reference: PMID:9537424
reference_title: "Mutations in the early growth response 2 (EGR2) gene are associated with hereditary myelinopathies."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Stable expression of Egr2 is specifically associated with the onset of myelination in the peripheral nervous system (PNS)."
explanation: Establishes EGR2 (Krox20) as a Schwann-cell transcription factor controlling PNS myelination, the process disrupted in demyelinating CMT1D.
- name: LITAF
gene_term:
preferred_term: LITAF
term:
id: hgnc:16841
label: LITAF
association: Causal
relationship_type: CAUSATIVE
subtype: CMT1C
notes: >-
LITAF, also called SIMPLE, encodes a small integral membrane protein of the
late endosome and lysosome. The founding report identified the clustered
missense mutations G112S, T115N and W116G in three CMT1C pedigrees after
mapping the locus to 16p13.1-p12.3. A search of the approved symbol LITAF in
the committed ClinGen Gene-Disease Validity cache (the 718 CGGV_*.md records
in references_cache) returns no row, so no expert panel has classified this
relationship in the records available here.
case_fractions:
- population: Korean CMT1 patients within a cohort of 1,143 unrelated CMT families
case_fraction_percent: 0.59
notes: >-
Ten CMT1C patients from three unrelated families, all carrying LITAF
p.G112S. The denominator is the CMT1 patients within the cohort, which the
report does not state as a count.
evidence:
- reference: PMID:35608774
reference_title: "Identification and clinical characterization of Charcot-Marie-Tooth disease type 1C patients with LITAF p.G112S mutation."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The frequency of CMT1C among CMT1 patients was 0.59%, which is similar to reports from Western populations."
explanation: Gives the share of CMT1 cases attributable to LITAF in this cohort.
evidence:
- reference: PMID:12525712
reference_title: "Mutation of a putative protein degradation gene LITAF/SIMPLE in Charcot-Marie-Tooth disease 1C."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The authors recently mapped an autosomal dominant demyelinating form of CMT type 1 (CMT1C) to chromosome 16p13.1-p12.3."
explanation: Establishes CMT1C as a dominant demyelinating CMT1 locus, which the same report then resolves to LITAF.
- reference: PMID:35608774
reference_title: "Identification and clinical characterization of Charcot-Marie-Tooth disease type 1C patients with LITAF p.G112S mutation."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "We identified 10 CMT1C patients from three unrelated families with p.G112S mutation in LITAF."
explanation: Independent cohort confirmation of LITAF as the CMT1C gene.
- name: NEFL
gene_term:
preferred_term: NEFL
term:
id: hgnc:7739
label: NEFL
association: Causal
relationship_type: CAUSATIVE
subtype: CMT1F
notes: >-
NEFL encodes neurofilament light chain. Its variants are classified as
CMT1F, CMT2E or DI-CMTG by electrodiagnostic findings rather than by
genotype, and a review of the published cases found the same variant
classified differently in different patients. The CMT2E presentation is
curated on Charcot-Marie-Tooth Disease Type 2 and the intermediate
presentation has its own entry, Charcot-Marie-Tooth Disease Dominant
Intermediate G. ClinGen's Charcot-Marie-Tooth
Disease Gene Curation Expert Panel has two NEFL rows in the committed cache,
Definitive for Charcot-Marie-Tooth disease (MONDO:0015626, autosomal
dominant) and Definitive for Charcot-Marie-Tooth disease type 2
(MONDO:0018993, autosomal recessive); neither is scored against CMT1F, so
the demyelinating designation is not separately graded.
evidence:
- reference: PMID:35044100
reference_title: "Phenotypic heterogeneity in patients with NEFL-related Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Mutations in the neurofilament light polypeptide (NEFL) gene produce diverse clinical phenotypes, including demyelinating (CMT1F), axonal (CMT2E), and intermediate (CMTDIG) neuropathies."
explanation: Establishes NEFL as the CMT1F gene and names the three presentations its variants produce.
- reference: CGGV:assertion_57ec533a-b1cb-4d1d-b12a-61ee6ac6ab07-2023-01-10T170000.000Z
reference_title: "NEFL / Charcot-Marie-Tooth disease (Definitive)"
supports: SUPPORT
evidence_source: OTHER
snippet: "NEFL | HGNC:7739 | Charcot-Marie-Tooth disease | MONDO:0015626 | AD | Definitive"
explanation: >-
ClinGen classifies the NEFL relationship with autosomal dominant
Charcot-Marie-Tooth disease as Definitive. The assertion is scored against
the generic CMT class rather than against CMT1F, which is the limit these
notes record.
- name: FBLN5
gene_term:
preferred_term: FBLN5
term:
id: hgnc:3602
label: FBLN5
association: Causal
relationship_type: CAUSATIVE
subtype: CMT1H
notes: >-
Heterozygous FBLN5 missense variants cause demyelinating CMT (CMT1H). The
relationship was established by mapping a dominant CMT1 family to chromosome
14q32 and resequencing the interval, then finding two further missense variants
among 112 unclassified CMT probands. ClinGen's Charcot-Marie-Tooth Disease Gene
Curation Expert Panel classifies FBLN5 as Moderate for demyelinating hereditary
motor and sensory neuropathy, so this is a supported but not definitively
established gene-disease relationship.
evidence:
- reference: PMID:21576112
reference_title: "Fibulin-5 mutations link inherited neuropathies, age-related macular degeneration and hyperelastic skin."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "This study identifies fibulin-5 as a gene involved in Charcot-Marie-Tooth neuropathies and reveals heterozygous fibulin-5 mutations in 2% of our patients with age-related macular degeneration."
explanation: Establishes FBLN5 as a CMT gene.
- reference: CGGV:assertion_a863341a-9dcf-4a4f-a82d-7edb5e63fe92-2023-11-28T170000.000Z
reference_title: "FBLN5 / demyelinating hereditary motor and sensory neuropathy (Moderate)"
supports: SUPPORT
evidence_source: OTHER
snippet: "FBLN5 | HGNC:3602 | demyelinating hereditary motor and sensory neuropathy | MONDO:0018776 | AD | Moderate"
explanation: >-
ClinGen classifies the FBLN5 demyelinating-neuropathy relationship as Moderate
with autosomal dominant inheritance, the strength recorded in these notes.
- name: ITPR3
gene_term:
preferred_term: ITPR3
term:
id: hgnc:6182
label: ITPR3
association: Causal
relationship_type: CAUSATIVE
subtype: CMT1J
notes: >-
Autosomal dominant ITPR3 variants cause CMT1J. The gene-disease relationship
rests on a segregating p.Val615Met variant in a four-affected dominant family,
a de novo p.Arg2524Cys variant in an isolated case, two previously identified
variants, and a dominant-negative calcium-transient phenotype in patient
fibroblasts. A search of the approved symbol ITPR3 in the ClinGen Gene-Disease
Validity CSV (snapshot 2026-08-13) returns no row, so no expert panel has yet
classified this relationship.
evidence:
- reference: PMID:32949214
reference_title: "Dominant mutations in ITPR3 cause Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Exome sequencing identified a heterozygous ITPR3 p.Val615Met variant segregating with the disease."
explanation: The segregating variant in the dominant family behind this gene-disease relationship.
- reference: PMID:32949214
reference_title: "Dominant mutations in ITPR3 cause Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Trio exome sequencing identified a de novo ITPR3 variant p.Arg2524Cys."
explanation: The independent de novo variant that supports the relationship beyond the single family.
- reference: PMID:32949214
reference_title: "Dominant mutations in ITPR3 cause Charcot-Marie-Tooth disease."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "The individual who was the only affected in his family had disease onset at age 4 with demyelinating neuropathy."
explanation: Sources the much earlier onset of the de novo case recorded in this subtype's description.
inheritance:
- name: Autosomal Dominant
description: >-
The majority of CMT1 subtypes — CMT1A (PMP22 duplication), CMT1B (MPZ),
and CMT1D (EGR2) — are inherited in an autosomal dominant manner. A single
pathogenic variant is sufficient to cause disease, and affected individuals
have a 50% chance of passing the variant to offspring.
inheritance_term:
preferred_term: Autosomal dominant inheritance
term:
id: HP:0000006
label: Autosomal dominant inheritance
evidence:
- reference: PMID:9537424
reference_title: "Mutations in the early growth response 2 (EGR2) gene are associated with hereditary myelinopathies."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "we have identified one recessive and two dominant missense mutations in EGR2 (within regions encoding conserved functional domains) in patients with congenital hypomyelinating neuropathy (CHN) and a family with Charcot-Marie-Tooth type 1 (CMT1)."
explanation: >-
Establishes that dominant mutations in EGR2 cause CMT1D, documenting autosomal
dominant inheritance as one of the primary modes of CMT1.
- name: X-linked
description: >-
The CMTX1 subtype is caused by mutations in GJB1 (connexin-32) on chromosome
Xq13.1 and is inherited in an X-linked manner. Males are more severely affected
than carrier females, and electrophysiology is intermediate between CMT1 and CMT2.
CMTX1 is the second most common form of CMT overall, accounting for 7–12% of
all CMT cases.
inheritance_term:
preferred_term: X-linked dominant inheritance
term:
id: HP:0001423
label: X-linked dominant inheritance
evidence:
- reference: PMID:30881289
reference_title: "Role of Connexin-Based Gap Junction Channels in Communication of Myelin Sheath in Schwann Cells."
supports: SUPPORT
evidence_source: OTHER
snippet: "CMTX1, the X-linked dominant form of CMT, is the second most common form of CMT and the first X-linked form of CMT, with 7% to 12%, and 50% of all CMT cases and X-linked cases, respectively"
explanation: >-
Establishes X-linked inheritance for CMTX1, documenting it as the second most
common CMT genotype and accounting for 7–12% of all CMT cases.
treatments:
- name: Physical and Occupational Therapy
description: Mainstay of supportive care to maintain mobility and function.
therapeutic_modality: BEHAVIORAL
treatment_term:
preferred_term: physical therapy
term:
id: NCIT:C15302
label: Physical Therapy
- name: Orthotic Bracing
description: Ankle-foot orthoses to compensate for foot drop and improve gait.
treatment_term:
preferred_term: supportive care
term:
id: NCIT:C15747
label: Supportive Care
- name: Genetic Counseling
description: Counseling for affected individuals and families.
treatment_term:
preferred_term: Genetic Counseling
term:
id: NCIT:C15240
label: Genetic Counseling
- name: PXT3003
description: >-
Oral fixed-dose combination of low-dose baclofen, naltrexone, and sorbitol
designed to lower PMP22 expression and improve axonal function in CMT1A.
Phase III trials (PLEO-CMT NCT02579759 completed, PREMIER NCT04762758).
treatment_term:
preferred_term: Pharmacotherapy
term:
id: NCIT:C15986
label: Pharmacotherapy
therapeutic_agent:
- preferred_term: baclofen
term:
id: CHEBI:2972
label: baclofen
- preferred_term: naltrexone
term:
id: CHEBI:7465
label: naltrexone
target_mechanisms:
- target: PMP22 Overexpression and Dysmyelination
description: >-
PXT3003 is designed to lower PMP22 expression, targeting the primary
dysmyelinating lesion of CMT1A.
evidence:
- reference: DOI:10.3390/genes14071391
reference_title: "The Current State of Charcot–Marie–Tooth Disease Treatment"
supports: SUPPORT
evidence_source: OTHER
snippet: "Compounds such as PXT3003, which are being clinically and preclinically investigated, and a broad array of therapeutic agents and their corresponding mechanisms are discussed."
explanation: Establishes PXT3003 as an active clinical/preclinical therapeutic candidate for CMT1A.
prevalence:
- population: Auckland region, New Zealand (population-based multi-source ascertainment, 2016)
measure_type: POINT_PREVALENCE
prevalence_class: BAND_1_9_PER_100000
rate_per_100000: 6.9
rate_low: 5.6
rate_high: 8.4
notes: >-
CMT1A (PMP22 duplication) subtype-specific age-standardised point prevalence from
the Theadom et al. 2019 Auckland population-based study. CMT1A is the single most
common CMT1 subtype (~43% of genetically resolved CMT), so this figure represents
a lower bound for the prevalence of the demyelinating CMT1 compartment as a whole.
evidence:
- reference: PMID:31203252
reference_title: "Prevalence of Charcot-Marie-Tooth disease across the lifespan: a population-based epidemiological study."
supports: SUPPORT
evidence_source: HUMAN_CLINICAL
snippet: "Prevalence of CMT1A was 6.9 per 100 000 (95% CI 5.6 to 8.4)."
explanation: >-
Population-based Auckland cohort (Theadom et al. 2019) provides age-standardised
point prevalence of 6.9/100,000 for CMT1A (PMP22 duplication), the dominant
CMT1 subtype, using multiple ascertainment sources.
references:
- reference: PMID:20301532
title: "Charcot-Marie-Tooth Hereditary Neuropathy Overview."
tags:
- GeneReviews
findings: []
datasets: []
notes: >-
Routing of the CMT1 series. MONDO:0019011, this entry's disease_term, has six
children: MONDO:0007309 CMT1A, MONDO:0007307 CMT1B, MONDO:0010995 CMT1C,
MONDO:0011890 CMT1D, MONDO:0007311 CMT1E and MONDO:0011902 CMT1F. Five of them
are has_subtypes rows here with their MONDO terms and causal genes bound.
CMT1E is deliberately not a row: it is curated as the standalone entry
kb/disorders/Charcot-Marie-Tooth_Disease_Type_1E.yaml, which binds
MONDO:0007311 as its own disease_term and models the PMP22 point-mutation
lesion as a proteostatic and cholesterol-trafficking defect distinct from the
CMT1A dosage lesion, with the therapeutic consequence that a CMT1A-directed
treatment does not transfer to it.
Two rows here bind MONDO classes that sit outside MONDO:0019011. MONDO:0030689
(CMT1H, FBLN5) and MONDO:0859311 (CMT1J, ITPR3) are both filed by MONDO under
MONDO:0015626 Charcot-Marie-Tooth disease rather than under MONDO:0019011,
even though MONDO:0859311's own label is "Charcot-Marie-Tooth disease,
demyelinating, type 1J" and CMT1H is one of MONDO:0030689's synonyms. The rows
are kept because the entry groups by electrophysiological compartment and both
are reported as demyelinating; the mismatch is a fact about where MONDO files
them. The CMTX1 row binds no MONDO term at all, because the X-linked form is
curated as kb/disorders/Charcot-Marie-Tooth_Disease_Type_X.yaml against
MONDO:0018994, which is likewise a child of MONDO:0015626; CMTX1 is grouped
here on mechanistic grounds, as a Schwann-cell gap-junction defect, and its row
carries the gene without claiming the class. CMT1G is a third sibling under
MONDO:0015626, curated as
kb/disorders/Charcot-Marie-Tooth_Disease_Demyelinating_Type_1G.yaml.
References & Deep Research
References
1Deep Research
1Deep research results are used as seeds for research; they do not undergo the same validation as the main records and may contain errors. How we use deep research.
Question: You are an expert researcher providing comprehensive, well-cited information.
Provide detailed information focusing on: 1. Key concepts and definitions with current understanding 2. Recent developments and latest research (prioritize 2023-2024 sources) 3. Current applications and real-world implementations 4. Expert opinions and analysis from authoritative sources 5. Relevant statistics and data from recent studies
Format as a comprehensive research report with proper citations. Include URLs and publication dates where available. Always prioritize recent, authoritative sources and provide specific citations for all major claims.
Disease Characteristics Research Template
Target Disease
- Disease Name: Charcot-Marie-Tooth Disease Type 1
- MONDO ID: MONDO:0019011 (if available)
- Category: Mendelian
Research Objectives
Please provide a comprehensive research report on Charcot-Marie-Tooth Disease Type 1 covering all of the disease characteristics listed below. This report will be used to populate a disease knowledge base entry. Be thorough and cite primary literature (PMID preferred) for all claims.
For each section, suggested databases/resources are listed. These are the first places you should search for information on each topic.
1. Disease Information
Search first: OMIM, Orphanet, ICD-10/ICD-11, MeSH, PubMed
- What is the disease? Provide a concise overview.
- What are the key identifiers? (OMIM, Orphanet, ICD-10/ICD-11, MeSH, Mondo)
- What are the common synonyms and alternative names?
- Is the information derived from individual patients (e.g., EHR) or aggregated disease-level resources?
2. Etiology
- Disease Causal Factors: What are the primary causes? (genetic, environmental, infectious, mechanistic)
- Risk Factors:
Search first: PubMed, Cochrane Library, UpToDate, clinical guidelines, ClinVar, ClinGen, GWAS Catalog, PheGenI, CTD, CDC, WHO, epidemiological databases
- Genetic risk factors (causal variants, susceptibility loci, modifier genes)
- Environmental risk factors (toxins, lifestyle, occupational exposures, age, sex, family history)
- Protective Factors:
Search first: PubMed, Cochrane Library, clinical trial databases, GWAS Catalog, gnomAD, WHO, CDC, nutrition databases
- Genetic protective factors (protective variants, modifier alleles)
- Environmental protective factors (diet, lifestyle, exposures that reduce risk)
- Gene-Environment Interactions: How do genetic and environmental factors interact to influence disease?
Search first: CTD, PubMed, PheGenI, GxE databases
3. Phenotypes
Search first: HPO (Human Phenotype Ontology), OMIM, Orphanet, PubMed, clinicaltrials.gov, MedDRA, SNOMED CT, DECIPHER, LOINC
For each phenotype, provide: - Phenotype type: symptoms, clinical signs, physical manifestations, behavioral changes, or laboratory abnormalities
For symptoms/signs: HPO, OMIM, Orphanet, PubMed For behavioral changes: HPO, DSM, RDoC (Research Domain Criteria), PubMed For laboratory abnormalities: LOINC, SNOMED CT, LabTests Online, PubMed - Phenotype characteristics: Search first: OMIM, Orphanet, HPO, PubMed - Age of symptom onset (neonatal, childhood, adult-onset, late-onset) - Symptom severity (mild, moderate, severe, variable) - Symptom progression (stable, progressive, episodic, fluctuating) - Frequency among affected individuals (percentage or qualitative) - Quality of life impact: Effects on daily functioning and well-being (per-phenotype when possible) Search first: EQ-5D database, SF-36, WHO QOL databases, PubMed - Suggest HPO (Human Phenotype Ontology) terms for each phenotype
4. Genetic/Molecular Information
- Causal Genes: Gene mutations or chromosomal abnormalities responsible for disease (gene symbols, OMIM IDs)
Search first: OMIM, ClinVar, HGMD, Ensembl, NCBI Gene
- Pathogenic Variants:
- Affected genes (gene symbols, HGNC IDs) > Search first: OMIM, NCBI Gene, Ensembl, HGNC, UniProt, GeneCards
- Variant classification (pathogenic, likely pathogenic, VUS per ACMG/AMP guidelines) > Search first: ClinVar, ClinGen, ACMG/AMP guidelines, VarSome
- Variant type/class (missense, frameshift, nonsense, splice-site, structural)
- Allele frequency in population databases > Search first: gnomAD, 1000 Genomes, ExAC, TOPMed, dbSNP
- Somatic vs germline origin > Search first: COSMIC (somatic), ClinVar, ICGC, TCGA
- Functional consequences (loss of function, gain of function, dominant negative)
- Modifier Genes: Genes that modify disease severity or expression
- Epigenetic Information: DNA methylation, histone modifications, chromatin changes affecting disease
Search first: ENCODE, Roadmap Epigenomics, MethBase, DiseaseMeth
- Chromosomal Abnormalities: Large-scale genetic changes (aneuploidy, translocations, inversions)
Search first: DECIPHER, ClinVar, ECARUCA, UCSC Genome Browser
5. Environmental Information
- Environmental Factors: Non-genetic contributing factors (toxins, radiation, pollution, occupational exposure)
Search first: CTD (Comparative Toxicogenomics Database), TOXNET, PubMed, EPA databases
- Lifestyle Factors: Behavioral factors (smoking, diet, exercise, alcohol consumption)
Search first: CDC databases, WHO, PubMed, NHANES
- Infectious Agents: If applicable, pathogens causing or triggering disease (bacteria, viruses, fungi, parasites)
Search first: NCBI Taxonomy, ViPR, BV-BRC, MicrobeDB, GIDEON
6. Mechanism / Pathophysiology
- Molecular Pathways: Specific signaling cascades or biochemical pathways involved (Wnt, MAPK, mTOR, PI3K-AKT, etc.)
Search first: KEGG, Reactome, WikiPathways, PathBank, BioCyc
- Cellular Processes: Cell-level mechanisms (apoptosis, autophagy, cell cycle dysregulation, inflammation, etc.)
Search first: Gene Ontology (GO), Reactome, KEGG, PubMed
- Protein Dysfunction: How protein structure or function is altered (misfolding, aggregation, loss of function, gain of function)
Search first: UniProt, PDB (Protein Data Bank), InterPro, Pfam, AlphaFold
- Metabolic Changes: Alterations in metabolic processes (energy metabolism, lipid metabolism, amino acid metabolism)
Search first: KEGG, BioCyc, HMDB (Human Metabolome Database), BRENDA
- Immune System Involvement: Role of immune response (autoimmunity, immunodeficiency, chronic inflammation)
Search first: ImmPort, Immunome Database, IEDB, Gene Ontology
- Tissue Damage Mechanisms: How tissues/ are injured (oxidative stress, ischemia, fibrosis, necrosis)
Search first: PubMed, Gene Ontology, Reactome
- Biochemical Abnormalities: Specific molecular defects (enzyme deficiencies, receptor dysfunction, ion channel defects)
Search first: BRENDA, UniProt, KEGG, OMIM, PubMed
- Epigenetic Changes: DNA methylation, histone modifications affecting gene expression in disease
Search first: ENCODE, Roadmap Epigenomics, MethBase, DiseaseMeth
- Molecular Profiling (if available):
- Transcriptomics/gene expression changes > Search first: GEO (Gene Expression Omnibus), ArrayExpress, GTEx, Human Cell Atlas, SRA
- Proteomics findings > Search first: PRIDE, ProteomeXchange, Human Protein Atlas, STRING, BioGRID
- Metabolomics signatures > Search first: MetaboLights, Metabolomics Workbench, HMDB, METLIN
- Lipidomics alterations > Search first: LIPID MAPS, SwissLipids, LipidHome, Metabolomics Workbench
- Genomic structural features > Search first: UCSC Genome Browser, Ensembl, NCBI, dbVar, DGV
- Advanced Technologies (if applicable):
- Single-cell analysis findings (cell-type specific mechanisms, cellular heterogeneity) > Search first: Human Cell Atlas, Single Cell Portal, GEO, CELLxGENE
- Spatial transcriptomics findings > Search first: GEO, Spatial Research, Vizgen, 10x Genomics data
- Multi-omics integration results > Search first: TCGA, ICGC, cBioPortal, LinkedOmics, PubMed
- Functional genomics screens (CRISPR, RNAi) > Search first: DepMap, GenomeRNAi, PubMed, BioGRID ORCS
For each mechanism, describe: - The causal chain from initial trigger to clinical manifestation - Which mechanisms are upstream vs downstream - What cell types and biological processes are involved - Suggest GO terms for biological processes and CL terms for cell types
7. Anatomical Structures Affected
- Organ Level:
- Primary organs directly affected
- Secondary organ involvement (complications, secondary effects)
- Body systems involved (cardiovascular, nervous, digestive, respiratory, endocrine, etc.)
Search first: Uberon, FMA (Foundational Model of Anatomy), OMIM, HPO, ICD-11, MeSH, SNOMED CT
- Tissue and Cell Level:
- Specific tissue types affected (epithelial, connective, muscle, nervous)
- Specific cell populations targeted (with Cell Ontology terms)
Search first: Uberon, Human Protein Atlas, Cell Ontology, Human Cell Atlas, CellMarker, PanglaoDB
- Subcellular Level:
- Cellular compartments involved (mitochondria, nucleus, ER, lysosomes) (with GO Cellular Component terms)
Search first: Gene Ontology (Cellular Component), UniProt, Human Protein Atlas
- Localization:
- Specific anatomical sites (with UBERON terms) > Search first: FMA, Uberon, NeuroNames (for brain), SNOMED CT
- Lateralization (unilateral, bilateral, asymmetric) > Search first: HPO, clinical literature, imaging databases
8. Temporal Development
- Onset:
- Typical age of onset (congenital, pediatric, adult, geriatric)
- Onset pattern (acute, subacute, chronic, insidious)
Search first: OMIM, Orphanet, HPO, PubMed
- Progression:
- Disease stages (early, intermediate, advanced, end-stage) > Search first: Cancer Staging Manual (AJCC), WHO classifications, PubMed
- Progression rate (rapid, slow, variable)
- Disease course pattern (episodic, relapsing-remitting, progressive, stable)
- Disease duration (self-limited, chronic lifelong)
Search first: Disease registries, longitudinal cohort databases, natural history studies, PubMed, Orphanet, OMIM
- Patterns:
- Remission patterns (spontaneous, treatment-induced) > Search first: Clinical trial databases, disease registries, PubMed
- Critical periods (time windows of vulnerability or opportunity for intervention) > Search first: PubMed, developmental biology databases, clinical guidelines
9. Inheritance and Population
- Epidemiology:
- Prevalence (cases per 100,000 at given time)
- Incidence (new cases per 100,000 per year)
Search first: Orphanet, CDC, WHO, GBD (Global Burden of Disease), national registries, SEER, disease registries
- For Genetic Etiology:
- Inheritance pattern (AD, AR, X-linked, mitochondrial, multifactorial, polygenic) > Search first: OMIM, Orphanet, ClinVar, GTR (Genetic Testing Registry)
- Penetrance (complete, incomplete, age-dependent) > Search first: ClinVar, OMIM, PubMed, ClinGen
- Expressivity (variable, consistent) > Search first: OMIM, ClinVar, PubMed
- Genetic anticipation (increasing severity in successive generations) > Search first: OMIM, PubMed (especially for repeat expansion disorders)
- Germline mosaicism > Search first: ClinVar, OMIM, genetic counseling literature, PubMed
- Founder effects (population-specific mutations) > Search first: gnomAD, population genetics databases, PubMed
- Consanguinity role > Search first: OMIM, population studies, genetic counseling resources
- Carrier frequency > Search first: gnomAD, carrier screening databases, GeneReviews, GTR
- Population Demographics:
- Affected populations (ethnic or demographic groups with higher prevalence) > Search first: gnomAD, 1000 Genomes, PAGE Study, PubMed, population registries
- Geographic distribution (endemic areas, regional variation) > Search first: WHO, CDC, GBD, Orphanet, geographic epidemiology databases
- Geographic distribution of specific variants
- Sex ratio (male:female) > Search first: Disease registries, OMIM, PubMed, epidemiological databases
- Age distribution of affected individuals > Search first: CDC, disease registries, SEER, Orphanet
10. Diagnostics
- Clinical Tests:
- Laboratory tests (blood, urine, tissue chemistry, specific enzyme assays) > Search first: LOINC, LabTests Online, PubMed
- Biomarkers (proteins, metabolites, genetic markers, circulating biomarkers) > Search first: FDA Biomarker List, BEST (Biomarkers, EndpointS, and other Tools), PubMed
- Imaging studies (X-ray, CT, MRI, PET, ultrasound) > Search first: RadLex, DICOM, Radiopaedia, imaging databases
- Functional tests (pulmonary function, cardiac stress tests) > Search first: LOINC, clinical guidelines, PubMed
- Electrophysiology (EEG, EMG, ECG, nerve conduction studies) > Search first: LOINC, clinical neurophysiology databases, PubMed
- Biopsy findings (histopathology, immunohistochemistry) > Search first: SNOMED CT, College of American Pathologists resources, PubMed
- Pathology findings (microscopic examination) > Search first: SNOMED CT, Digital Pathology databases, PubMed
- Genetic Testing:
Search first: GTR (Genetic Testing Registry), GeneReviews, ClinGen
- Overview of recommended genetic testing approach
- Whole genome sequencing (WGS) utility > Search first: GTR, ClinVar, GEL (Genomics England), gnomAD
- Whole exome sequencing (WES) utility > Search first: GTR, ClinVar, OMIM, GeneMatcher
- Gene panels (which panels, which genes) > Search first: GTR, ClinVar, laboratory-specific databases
- Single gene testing > Search first: GTR, ClinVar, OMIM, GeneReviews
- Chromosomal microarray (CMA) > Search first: DECIPHER, ClinVar, dbVar, ECARUCA
- Karyotyping > Search first: Chromosome Abnormality Database, ClinVar, cytogenetics resources
- FISH > Search first: ClinVar, cytogenetics databases, PubMed
- Mitochondrial DNA testing > Search first: MITOMAP, MSeqDR, ClinVar, GTR
- Repeat expansion testing > Search first: GTR, ClinVar, repeat expansion databases, PubMed
- Omics-Based Diagnostics (if applicable):
- RNA sequencing / transcriptomics > Search first: GEO, ArrayExpress, GTEx, RNA-seq databases
- Proteomics > Search first: PRIDE, ProteomeXchange, FDA Biomarker database
- Metabolomics > Search first: MetaboLights, Metabolomics Workbench, HMDB
- Epigenomics > Search first: GEO, ENCODE, Roadmap Epigenomics, MethBase
- Liquid biopsy > Search first: COSMIC, ClinVar, liquid biopsy databases, PubMed
- Clinical Criteria:
- Standardized diagnostic criteria (DSM, ICD, society guidelines) > Search first: DSM-5, ICD-11, clinical society guidelines, UpToDate
- Differential diagnosis (other conditions to rule out, with distinguishing features) > Search first: DynaMed, UpToDate, clinical decision support systems
- Screening:
- Screening methods for asymptomatic individuals (newborn screening, carrier screening, cascade screening) > Search first: ACMG recommendations, CDC newborn screening, GTR
11. Outcome/Prognosis
- Survival and Mortality:
- Survival rate (5-year, 10-year, overall) > Search first: SEER, cancer registries, disease-specific registries, PubMed
- Life expectancy (with and without treatment if applicable) > Search first: Orphanet, disease registries, actuarial databases, PubMed
- Mortality rate > Search first: CDC, WHO, GBD, national mortality databases
- Disease-specific mortality (deaths directly attributable to disease) > Search first: Disease registries, CDC Wonder, GBD, PubMed
- Morbidity and Function:
- Morbidity (disease-related disability and health impacts) > Search first: GBD, WHO, disability databases, PubMed
- Disability outcomes (long-term functional impairments) > Search first: ICF (International Classification of Functioning), disability registries
- Quality of life measures (EQ-5D, SF-36, PROMIS, disease-specific tools) > Search first: EQ-5D database, SF-36, PROMIS, PubMed
- Disease Course:
- Complications (secondary problems: infections, organ failure, etc.) > Search first: ICD codes, disease registries, clinical databases, PubMed
- Recovery potential (likelihood and extent of recovery, with vs without treatment) > Search first: Natural history studies, rehabilitation databases, PubMed
- Prediction:
- Prognostic factors (age, disease severity, biomarkers, treatment response) > Search first: Prognostic models databases, clinical calculators, PubMed
- Prognostic biomarkers (molecular markers predicting disease course) > Search first: FDA Biomarker database, PubMed, cancer prognostic databases
12. Treatment
- Pharmacotherapy:
- Pharmacological treatments (drug names, drug classes, mechanisms of action) > Search first: DrugBank, RxNorm, ATC classification, DailyMed, FDA databases
- Pharmacogenomics (how genetic variants affect drug metabolism, efficacy, toxicity) > Search first: PharmGKB, CPIC (Clinical Pharmacogenetics), FDA Table of PGx Biomarkers
- Advanced Therapeutics:
- Gene therapy (viral vectors, CRISPR, gene replacement, gene editing) > Search first: ClinicalTrials.gov, FDA gene therapy database, ASGCT resources
- Cell therapy (stem cell transplant, CAR-T, cellular therapeutics) > Search first: ClinicalTrials.gov, FDA cell therapy database, FACT standards
- RNA-based therapies (ASOs, siRNA, mRNA therapies) > Search first: ClinicalTrials.gov, FDA approvals, PubMed
- Targeted therapies (treatments directed at specific molecular targets) > Search first: My Cancer Genome, OncoKB, ClinicalTrials.gov, FDA approvals
- Immunotherapies (checkpoint inhibitors, monoclonal antibodies) > Search first: Cancer Immunotherapy Database, FDA approvals, ClinicalTrials.gov
- Surgical and Interventional:
- Surgical interventions (types of surgery, timing, outcomes) > Search first: CPT codes, surgical registries, clinical guidelines, PubMed
- Supportive and Rehabilitative:
- Supportive care (symptom management, pain control, nutrition) > Search first: Clinical guidelines, Cochrane Library, PubMed
- Rehabilitation (physical therapy, occupational therapy, speech therapy) > Search first: Rehabilitation medicine databases, clinical guidelines, PubMed
- Experimental:
- Experimental treatments in clinical trials (with NCT identifiers if available) > Search first: ClinicalTrials.gov, EU Clinical Trials Register, WHO ICTRP
- Treatment Outcomes:
- Treatment response rates > Search first: Clinical trial databases, FDA reviews, systematic reviews, PubMed
- Side effects and adverse events > Search first: FDA Adverse Event Reporting System (FAERS), MedWatch, PubMed
- Treatment Strategy:
- Treatment algorithms (clinical pathways, decision trees) > Search first: Clinical practice guidelines, NCCN Guidelines, UpToDate
- Combination therapies > Search first: ClinicalTrials.gov, treatment guidelines, PubMed
- Personalized medicine approaches (genotype-guided treatment) > Search first: My Cancer Genome, CIViC, PharmGKB, precision medicine databases
For each treatment, suggest MAXO (Medical Action Ontology) terms where applicable.
13. Prevention
- Prevention Levels:
- Primary prevention (preventing disease occurrence: vaccination, risk factor modification) > Search first: CDC, WHO, USPSTF recommendations, Cochrane Library
- Secondary prevention (early detection and treatment: screening programs, early intervention) > Search first: USPSTF, CDC screening guidelines, WHO
- Tertiary prevention (preventing complications in those with disease) > Search first: Clinical guidelines, disease management protocols, PubMed
- Immunization: Vaccine strategies (if applicable)
Search first: CDC vaccine schedules, WHO immunization, FDA vaccine database
- Screening and Early Detection:
- Screening programs (population-based: newborn screening, cancer screening) > Search first: CDC screening programs, USPSTF, cancer screening databases
- Genetic screening (carrier screening, preimplantation genetic diagnosis, prenatal testing) > Search first: ACMG recommendations, ACOG guidelines, GTR
- Risk stratification (identifying high-risk individuals for targeted prevention) > Search first: Risk prediction models, clinical calculators, PubMed
- Behavioral Interventions: Lifestyle modifications to reduce risk
Search first: CDC, WHO, behavioral intervention databases, Cochrane Library
- Counseling: Genetic counseling (risk assessment, family planning guidance)
Search first: NSGC resources, ACMG guidelines, GeneReviews
- Public Health:
- Public health interventions (sanitation, vector control, health education) > Search first: CDC, WHO, public health databases, PubMed
- Environmental interventions (reducing environmental risk factors) > Search first: EPA databases, WHO environmental health, PubMed
- Prophylaxis: Preventive medications or procedures
Search first: Clinical guidelines, FDA approvals, PubMed
14. Other Species / Natural Disease
- Taxonomy: Species affected (with NCBI Taxon identifiers)
Search first: NCBI Taxonomy
- Breed: Specific breeds affected (with VBO identifiers if applicable)
Search first: VBO (Vertebrate Breed Ontology)
- Gene: Orthologous genes in other species (with NCBI Gene IDs)
Search first: NCBI Gene
- Natural Disease:
- Naturally occurring disease in other species (companion animals, wildlife) > Search first: OMIA (Online Mendelian Inheritance in Animals), VetCompass, PubMed
- Veterinary relevance and importance in animal health > Search first: OMIA, veterinary databases, PubMed
- Comparative Biology:
- Comparative pathology (similarities and differences across species) > Search first: OMIA, comparative pathology databases, PubMed
- Evolutionary conservation of disease mechanisms > Search first: HomoloGene, OrthoMCL, Alliance of Genome Resources
- Transmission (if applicable):
- Zoonotic potential > Search first: CDC zoonotic diseases, WHO zoonoses, GIDEON
- Cross-species susceptibility > Search first: NCBI Taxonomy, veterinary databases, PubMed
15. Model Organisms
- Model Types:
- Model organism type (mammalian, invertebrate, cellular, in vitro) > Search first: Alliance of Genome Resources, model organism databases
- Specific model systems (mouse, rat, zebrafish, Drosophila, C. elegans, yeast, cell lines, organoids, iPSCs) > Search first: MGI, RGD, ZFIN, FlyBase, WormBase, SGD, ATCC, Cellosaurus
- Induced models (drug treatment, surgical intervention, environmental manipulation) > Search first: MGI, model organism databases, PubMed
- Genetic Models:
- Types available (knockout, knock-in, transgenic, conditional, humanized) > Search first: MGI, IMPC, KOMP, EuMMCR, IMSR
- Model Characteristics:
- Phenotype recapitulation (how well model reproduces human disease features) > Search first: Model organism databases, comparative studies, PubMed
- Model limitations (aspects of human disease not captured) > Search first: Model organism databases, PubMed, review articles
- Applications:
- Research applications (what aspects of disease can be studied) > Search first: Model organism databases, PubMed
- Resources:
- Model databases > Search first: MGI, RGD, ZFIN, FlyBase, WormBase, IMSR, EMMA, MMRRC
Citation Requirements
- Cite primary literature (PMID preferred) for all mechanistic and clinical claims
- Prioritize recent reviews and landmark papers
- Include direct quotes from abstracts where possible to support key statements
- Distinguish evidence source types: human clinical, model organism, in vitro, computational
Output Format
Structure your response as a comprehensive narrative organized by the sections above. For each section, provide: - Factual content with specific details (numbers, percentages, gene names, variant nomenclature) - Ontology term suggestions (HPO, GO, CL, UBERON, CHEBI, MAXO, MONDO) where applicable - Evidence citations with PMIDs - Direct quotes from abstracts to support key claims - Clear indication when information is not available or not applicable for this disease
This report will be used to populate a disease knowledge base entry with: - Pathophysiology descriptions with causal chains - Gene/protein annotations (HGNC, GO terms) - Phenotype associations (HP terms) with frequencies - Cell type involvement (CL terms) - Anatomical locations (UBERON terms) - Chemical entities (CHEBI terms) - Treatment annotations (MAXO terms) - Evidence items with PMIDs and exact abstract quotes - Epidemiology, prognosis, diagnostic, and prevention information - Animal model descriptions with phenotype recapitulation details
Comprehensive Research Report: Charcot–Marie–Tooth Disease Type 1 (CMT1)
Scope and evidence note
This report synthesizes information retrieved from peer‑reviewed reviews and cohort studies (2022–2024 prioritized), ClinicalTrials.gov registry records for ongoing/completed interventional studies, and Open Targets disease–gene association data. Some identifier fields (OMIM, Orphanet, ICD-10/ICD-11, MeSH) were not directly present in the retrieved full texts; these gaps are explicitly labeled as “not retrieved in tool context” rather than inferred.
| Item | Evidence-backed statement/data | Source (first author, journal, year) | PMID/DOI/URL | Notes for ontology mapping |
|---|---|---|---|---|
| Disease definition | CMT1 is the demyelinating form of Charcot-Marie-Tooth disease, an inherited peripheral neuropathy affecting peripheral nerves/Schwann cells with slowly progressive distal weakness, sensory loss, and foot deformities (okamoto2023thecurrentstate pages 1-2, dong2024currenttreatmentmethods pages 1-2) | Okamoto, Genes, 2023; Dong, Biomolecules, 2024 | DOI: 10.3390/genes14071391; https://doi.org/10.3390/genes14071391; DOI: 10.3390/biom14091138; https://doi.org/10.3390/biom14091138 | MONDO:0019011; UBERON:0000010 peripheral nervous system; CL:0002573 myelinating Schwann cell; HPO: HP:0003401 distal muscle weakness, HP:0009836 peripheral neuropathy |
| Electrophysiologic classification | In one recent treatment review, demyelinating CMT1 is defined by upper-limb MNCV <38 m/s, axonal CMT2 by >38 m/s, and intermediate forms by 25–45 m/s (okamoto2023thecurrentstate pages 1-2, estevezarias2022geneticapproachesand pages 1-3) | Okamoto, Genes, 2023; Estévez-Arias, J Transl Genet Genom, 2022 | DOI: 10.3390/genes14071391; https://doi.org/10.3390/genes14071391; DOI: 10.20517/jtgg.2022.04; https://doi.org/10.20517/jtgg.2022.04 | HPO support: HP:0003448 reduced nerve conduction velocity |
| Electrophysiologic subclassification | Another 2024 review gives forearm ulnar motor NCV ranges: very slow <15 m/s; slow 15–35 m/s; intermediate 35–45 m/s; normal >45 m/s (dong2024currenttreatmentmethods pages 1-2) | Dong, Biomolecules, 2024 | DOI: 10.3390/biom14091138; https://doi.org/10.3390/biom14091138 | Useful for phenotype annotation and diagnostic rule representation |
| Cohort-specific strict CMT1 cutoff | In the large UK diagnostic cohort, CMT1 was operationally defined as demyelinating neuropathy with upper-limb MNCV <25 m/s (record2024wholegenomesequencing pages 2-3, record2024wholegenomesequencing pages 1-2) | Record, Brain, 2024 | DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | Note cohort definition differs from broader review cutoffs; encode as study-specific diagnostic criterion |
| Prevalence estimate | Recent reviews report CMT prevalence ranging from 1 in 2,500 to 1 in 10,000 individuals (record2024wholegenomesequencing pages 1-2) | Record, Brain, 2024 | DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | Disease-level epidemiology; aggregated resource, not individual EHR-derived |
| General prevalence estimate | Other recent reviews summarize CMT prevalence as approximately 1:2,500 (estevezarias2022geneticapproachesand pages 1-3, dong2024currenttreatmentmethods pages 1-2) | Estévez-Arias, J Transl Genet Genom, 2022; Dong, Biomolecules, 2024 | DOI: 10.20517/jtgg.2022.04; https://doi.org/10.20517/jtgg.2022.04; DOI: 10.3390/biom14091138; https://doi.org/10.3390/biom14091138 | Supports common “most prevalent inherited neuropathy” statement |
| Major causal architecture | CMT1A is caused by a recurrent chromosome 17 duplication containing PMP22; the canonical lesion is described as a 1.4 Mbp duplication in recent literature (estevezarias2022geneticapproachesand pages 3-5, record2024wholegenomesequencing pages 2-3) | Estévez-Arias, J Transl Genet Genom, 2022; Record, Brain, 2024 | DOI: 10.20517/jtgg.2022.04; https://doi.org/10.20517/jtgg.2022.04; DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | MONDO:0007309 CMT1A; gene: PMP22; structural variant/CNV annotation |
| PMP22 share of all CMT | PMP22 duplication/CMT1A accounts for about 50% of all CMT cases in one review (estevezarias2022geneticapproachesand pages 3-5) | Estévez-Arias, J Transl Genet Genom, 2022 | DOI: 10.20517/jtgg.2022.04; https://doi.org/10.20517/jtgg.2022.04 | Genetic epidemiology fact; useful for testing prioritization |
| PMP22 share of demyelinating CMT | The same review states PMP22 duplication accounts for about 70.7% of demyelinating CMT (estevezarias2022geneticapproachesand pages 3-5) | Estévez-Arias, J Transl Genet Genom, 2022 | DOI: 10.20517/jtgg.2022.04; https://doi.org/10.20517/jtgg.2022.04 | Apply specifically to CMT1/demyelinating subgroup |
| PMP22 share of solved cases | In the UK specialist cohort, PMP22 duplication = 505/1165 solved cases (43.3%) (record2024wholegenomesequencing pages 1-2) | Record, Brain, 2024 | DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | High-value disease-gene frequency datum |
| PMP22 share within CMT1 | In the same cohort, 505/621 CMT1 cases (82.3%) had PMP22 duplication; among solved CMT1, this was 84.0% (record2024wholegenomesequencing pages 3-5) | Record, Brain, 2024 | DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | Supports first-line PMP22 CNV testing in CMT1 phenotype |
| CMT1 diagnostic rate | In the large UK cohort, genetic diagnosis was achieved in 601/621 CMT1 cases (96.8%) (record2024wholegenomesequencing pages 3-5, record2024wholegenomesequencing pages 1-2) | Record, Brain, 2024 | DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | Disease subclass-specific diagnostic performance metric |
| Overall diagnostic yield | Across 1,515 patients with CMT/related disorders, overall genetic diagnosis was 76.9% (1165/1515) (record2024wholegenomesequencing pages 2-3, record2024wholegenomesequencing pages 1-2) | Record, Brain, 2024 | DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | Real-world implementation metric for specialist inherited neuropathy service |
| Preferred first-line CNV test | The 2024 Brain cohort paper states MLPA remains the preferred test for CMT1A (record2024wholegenomesequencing pages 2-3) | Record, Brain, 2024 | DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | Diagnostic ontology note: CNV assay; consider MAXO-like testing action mapping externally |
| WGS diagnostic uplift | In the UK cohort, WGS provided an overall diagnostic uplift of 3.5% across the whole cohort (record2024wholegenomesequencing pages 1-2) | Record, Brain, 2024 | DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | Implementation metric for genome sequencing in unsolved neuropathy |
| WGS yield in 100KGP subset | In the UK 100,000 Genomes subset, the “true” WGS diagnostic rate was 19.7% (46/233) after excluding diagnoses obtained by other means (record2024wholegenomesequencing pages 1-2) | Record, Brain, 2024 | DOI: 10.1093/brain/awae064; https://doi.org/10.1093/brain/awae064 | Useful for expectations after prior routine testing |
| PMP22 overexpression mechanism | PMP22 overexpression in CMT1A leads to protein aggregates, reduced proteasome activity, accumulation of insoluble ubiquitinated substrates, and Schwann-cell apoptosis (dong2024currenttreatmentmethods pages 2-4) | Dong, Biomolecules, 2024 | DOI: 10.3390/biom14091138; https://doi.org/10.3390/biom14091138 | GO: protein aggregation, proteasome-mediated ubiquitin-dependent protein catabolic process, apoptotic process; CL: myelinating Schwann cell |
| MPZ/UPR mechanism | For CMT1B, MPZ mutations can cause ER retention, activation of the unfolded protein response (UPR), and disruption of myelin compaction (dong2024currenttreatmentmethods pages 2-4) | Dong, Biomolecules, 2024 | DOI: 10.3390/biom14091138; https://doi.org/10.3390/biom14091138 | GO: response to endoplasmic reticulum stress, unfolded protein response, myelination; UBERON: peripheral nerve |
| Pathobiology theme | Recent mechanistic reviews emphasize Schwann-cell/myelin dysfunction as central to demyelinating CMT, linking dysfunctional myelin to secondary axonal damage and disability (okamoto2023thecurrentstate pages 1-2, estevezarias2022geneticapproachesand pages 3-5) | Okamoto, Genes, 2023; Estévez-Arias, J Transl Genet Genom, 2022 | DOI: 10.3390/genes14071391; https://doi.org/10.3390/genes14071391; DOI: 10.20517/jtgg.2022.04; https://doi.org/10.20517/jtgg.2022.04 | GO: myelination, axon ensheathment; CL: Schwann cell; UBERON: peripheral nerve |
| Outcome measure validation sample | The validated CMT-FOM was tested in 214 adults with CMT1A, ages 18–75, 58% female, across US/UK/Italy sites (mandarakas2024multicentervalidationof pages 1-2) | Mandarakas, Neurology, 2024 | DOI: 10.1212/WNL.0000000000207963; https://doi.org/10.1212/wnl.0000000000207963 | Clinical outcome assessment for trials; supportive of endpoint ontology mapping |
| CMT-FOM structure | The CMT-FOM was validated as a 12-item unidimensional interval scale with a 0–100 scoring system covering strength, upper/lower limb function, balance, and mobility (mandarakas2024multicentervalidationof pages 1-2) | Mandarakas, Neurology, 2024 | DOI: 10.1212/WNL.0000000000207963; https://doi.org/10.1212/wnl.0000000000207963 | Functional phenotype capture: gait/balance/hand weakness/falls |
| CMT-FOM psychometric correlation 1 | CMT-FOM correlated with the CMT Examination Score at r = 0.643; p < 0.001 (mandarakas2024multicentervalidationof pages 1-2) | Mandarakas, Neurology, 2024 | DOI: 10.1212/WNL.0000000000207963; https://doi.org/10.1212/wnl.0000000000207963 | Trial-readiness metric |
| CMT-FOM psychometric correlation 2 | CMT-FOM correlated with the Overall Neuropathy Limitation Scale at r = 0.516; p < 0.001 (mandarakas2024multicentervalidationof pages 1-2) | Mandarakas, Neurology, 2024 | DOI: 10.1212/WNL.0000000000207963; https://doi.org/10.1212/wnl.0000000000207963 | Endpoint harmonization with prior CMT trials |
| PXT3003 Phase III design (PLEO-CMT) | NCT02579759 enrolled 323 patients in a randomized, double-blind, placebo-controlled phase III trial; primary endpoint was ONLS total score averaged from months 12 and 15 (NCT02579759 chunk 1) | ClinicalTrials.gov NCT02579759, 2015 registration | https://clinicaltrials.gov/study/NCT02579759 | MAXO suggestion: combination pharmacotherapy; disease-modifying investigational treatment |
| PXT3003 Phase III secondary endpoints (PLEO-CMT) | PLEO-CMT key secondary endpoints included 10MWT, CMTNS-v2 sensory/exam scores, 9-HPT, plus safety outcomes (TEAEs, withdrawals, SAEs) (NCT02579759 chunk 1) | ClinicalTrials.gov NCT02579759, 2015 registration | https://clinicaltrials.gov/study/NCT02579759 | Endpoint catalog for trial knowledge base |
| PLEO-CMT notable event | In PLEO-CMT, the high-dose arm was prematurely discontinued on 18 Sep 2017 because of a product quality/stability issue; the DSMC had not identified safety concerns (NCT02579759 chunk 1) | ClinicalTrials.gov NCT02579759, 2015 registration | https://clinicaltrials.gov/study/NCT02579759 | Important for interpreting phase III efficacy evidence |
| PXT3003 Phase III design (PREMIER) | NCT04762758 is a multicenter randomized placebo-controlled phase III study planning about 350 subjects, with mONLS and 10-Meter Walk Test as primary outcomes at Month 15 (NCT04762758 chunk 1) | ClinicalTrials.gov NCT04762758, 2021 registration | https://clinicaltrials.gov/study/NCT04762758 | MAXO suggestion: oral combination drug therapy |
| PXT3003 Phase III dosing (PREMIER) | In PREMIER, PXT3003 is given 10 mL twice daily for 15 months after a 2-week half-dose titration (5 mL BID) (NCT04762758 chunk 1) | ClinicalTrials.gov NCT04762758, 2021 registration | https://clinicaltrials.gov/study/NCT04762758 | Administration detail for intervention annotation |
| PXT3003 phase III status | PREMIER was reported as ACTIVE_NOT_RECRUITING at last update in the registry excerpt (NCT04762758 chunk 1) | ClinicalTrials.gov NCT04762758, 2021 registration | https://clinicaltrials.gov/study/NCT04762758 | Current implementation status; check registry for latest changes |
| Additional phase III registry | A separate phase III PXT3003 study, NCT05092841, is listed in trial search results as completed with 176 participants (OpenTargets Search: Charcot-Marie-Tooth disease type 1,Charcot-Marie-Tooth disease type 1A,Charcot-Marie-Tooth disease type 1B) | ClinicalTrials.gov search results, 2024 retrieval | https://clinicaltrials.gov/study/NCT05092841 | Registry-level fact only from retrieved trial metadata |
| Visual diagnostic aid | A recent review contains a figure showing typical CMT phenotypes (claw hands, pes cavus) and a table classifying demyelinating/intermediate/axonal CMT by NCV thresholds (dong2024currenttreatmentmethods media 041cb15e) | Dong, Biomolecules, 2024 | DOI: 10.3390/biom14091138; https://doi.org/10.3390/biom14091138 | HPO: HP:0001761 pes cavus, HP:0001159 syndactyl? not applicable; prioritize HP:0001765 hammer toe, HP:0009467 claw hand if used in KB |
Table: This table compiles compact, citation-backed facts on Charcot-Marie-Tooth disease type 1 and CMT1A for knowledge-base use, spanning classification, epidemiology, genetics, mechanisms, outcomes, and current phase III therapeutic trials.
1. Disease Information
Definition and overview. Charcot–Marie–Tooth disease (CMT) comprises inherited peripheral neuropathies; CMT1 refers to demyelinating forms, with typical clinical findings of slowly progressive distal weakness/atrophy, reduced reflexes, distal sensory loss, and foot deformities such as pes cavus. (okamoto2023thecurrentstate pages 1-2, dong2024currenttreatmentmethods pages 1-2)
Classification by electrophysiology. A widely used scheme distinguishes demyelinating CMT1 versus axonal CMT2 using upper-limb motor nerve conduction velocities (MNCV). A recent 2023 review states <38 m/s is consistent with demyelinating CMT1 and >38 m/s with axonal CMT2, with intermediate ranges (e.g., 25–45 m/s) in some subtypes such as CMTX1. (okamoto2023thecurrentstate pages 1-2, estevezarias2022geneticapproachesand pages 1-3)
Study‑specific definition used in a large diagnostic cohort. A 2024 Brain specialist-center cohort operationalized CMT1 as upper-limb MNCV <25 m/s, CMT2 as >45 m/s, and intermediate CMT as 25–45 m/s, illustrating that thresholds vary by study/clinic and should be stored as provenance‑linked criteria. (record2024wholegenomesequencing pages 2-3, record2024wholegenomesequencing pages 3-5)
Key identifiers. - MONDO: MONDO:0019011 (Charcot–Marie–Tooth disease type 1) is supported in Open Targets disease–gene association outputs. (OpenTargets Search: Charcot-Marie-Tooth disease type 1,Charcot-Marie-Tooth disease type 1A,Charcot-Marie-Tooth disease type 1B) - OMIM/Orphanet/ICD/MeSH: not retrieved in the current tool context.
Common synonyms/alternative names. “Charcot–Marie–Tooth disease” is also used interchangeably with “hereditary motor and sensory neuropathy” (HMSN) in the reviewed literature. (estevezarias2022geneticapproachesand pages 3-5)
Evidence source type. The information above is primarily from aggregated disease-level resources (reviews/cohorts) rather than individual EHR records. (okamoto2023thecurrentstate pages 1-2, record2024wholegenomesequencing pages 3-5)
2. Etiology
Primary causal factors (genetic). CMT1 is a Mendelian disorder family dominated by pathogenic variation in genes essential for peripheral myelin structure/function. Reviews emphasize PMP22, MPZ, and GJB1 as major causes of demyelinating/dysmyelinating CMT forms, with CMT1A caused by PMP22 copy‑number gain. (estevezarias2022geneticapproachesand pages 3-5, jacob2023mechanismsandtreatment pages 1-2)
CMT1A (major subtype). CMT1A arises from a recurrent tandem duplication spanning ~1.4–1.5 Mb containing PMP22, causing PMP22 overexpression (gene-dosage). (record2024wholegenomesequencing pages 2-3, jacob2023mechanismsandtreatment pages 1-2)
Inheritance. Many CMT1 subtypes (including CMT1A) are typically autosomal dominant in clinical descriptions of major demyelinating forms; pathogenic CNVs and dominant missense/truncating variants are recurrently discussed in the literature base. (estevezarias2022geneticapproachesand pages 3-5, jacob2023mechanismsandtreatment pages 1-2)
Risk factors / protective factors. For CMT1 (Mendelian), the principal “risk factor” is carrying the causal germline variant/CNV. Environmental protective factors or variant-defined “protective alleles” were not identified in the retrieved texts.
Gene–environment interactions. Not specifically addressed in the retrieved sources.
3. Phenotypes (clinical spectrum)
Core clinical features (symptoms/signs). Reviews describe length‑dependent, slowly progressive distal muscle atrophy/weakness (often feet/ankles first), sensory loss, diminished reflexes, and characteristic foot/hand deformities (e.g., pes cavus; claw hands). (okamoto2023thecurrentstate pages 1-2, dong2024currenttreatmentmethods pages 1-2)
Visual evidence of phenotype. A 2024 review includes a figure depicting typical manifestations such as claw hands and pes cavus/hammer toes; and a table classifying CMT by nerve conduction velocities. (dong2024currenttreatmentmethods media 041cb15e, dong2024currenttreatmentmethods media 8b0c7523)
Onset and progression. Reviews commonly place CMT onset in childhood through early adulthood (first to third decade) with slow progression. (estevezarias2022geneticapproachesand pages 1-3)
Phenotype frequencies / patient-reported burdens. In an Italian registry study on sleep metrics across CMT (mixed genotypes), poor sleep quality (PSQI >5) occurred in 56% and abnormal daytime somnolence (ESS >10) in 23%; poor sleep quality correlated with fatigue/anxiety/depression and with higher disease severity by CMTES. (cesaroni2025pmp22relatedneuropathiesa pages 12-13)
Suggested HPO terms (examples). - Peripheral neuropathy (HP:0009830) - Pes cavus (HP:0001761) - Hammer toe (HP:0001765) - Distal muscle weakness (HP:0003401) - Areflexia / decreased deep tendon reflexes (HP:0001284) - Reduced nerve conduction velocity (HP:0003448) - Foot drop (HP:0001760)
4. Genetic/Molecular Information
Causal genes (CMT1 focus). Open Targets and reviews support strong disease–gene associations for PMP22, MPZ, and EGR2 in CMT1; additional curated associations include SH3TC2 and others depending on subtype definition and curation source. (OpenTargets Search: Charcot-Marie-Tooth disease type 1,Charcot-Marie-Tooth disease type 1A,Charcot-Marie-Tooth disease type 1B)
Variant classes and functional consequences. - PMP22 duplication (CNV): gene-dosage gain causing overexpression in Schwann cells; dominant demyelinating neuropathy. (jacob2023mechanismsandtreatment pages 1-2) - MPZ variants: can cause ER retention and activation of the unfolded protein response (UPR), disrupting myelin compaction. (dong2024currenttreatmentmethods pages 2-4)
Allele frequencies / population database frequencies. Not retrieved in the current tool context.
Modifier genes. Not explicitly identified in retrieved texts.
Epigenetic information. Not retrieved.
Chromosomal abnormalities. The principal structural abnormality for CMT1A is the recurrent ~1.4–1.5 Mb duplication on chromosome 17p containing PMP22. (record2024wholegenomesequencing pages 2-3)
5. Environmental Information
No CMT1‑specific toxins, lifestyle exposures, or infectious triggers were identified in the retrieved sources as causal contributors.
6. Mechanism / Pathophysiology
Causal chain (CMT1A, gene dosage). PMP22 copy-number gain → PMP22 overexpression in myelinating Schwann cells → destabilized myelin structure leading to demyelination/dysmyelination → secondary axonal loss → distal weakness/sensory loss and disability. (jacob2023mechanismsandtreatment pages 1-2)
Protein homeostasis and cell stress mechanisms. A 2024 review describes PMP22 overexpression leading to protein aggregates, reduced proteasome activity, accumulation of ubiquitinated substrates, and apoptosis in Schwann cells. (dong2024currenttreatmentmethods pages 2-4)
ER stress/UPR. Mechanistic review text reports PMP22 aggregates in ER/cytoplasm/lysosomes and links these to ER stress and activation of UPR pathways in CMT1A models; MPZ mutations (CMT1B) are also tied to ER retention and UPR activation. (jacob2023mechanismsandtreatment pages 1-2, dong2024currenttreatmentmethods pages 2-4)
Dysregulated signaling (axon–glia). In CMT1A rodent models, altered axon–Schwann signaling (NRG1/ErbB2/3) and downstream PI3K/AKT reduction with MEK/ERK hyperactivation are described as correlates of impaired Schwann differentiation and abnormal myelination. (jacob2023mechanismsandtreatment pages 1-2)
Inflammation as a possible modifier/comorbidity. A 2024 perspective review argues inflammation can coexist with hereditary neuropathy and that some CMT patients have shown responses to anti‑inflammatory therapy, challenging strict separation of inherited vs inflammatory neuropathies. (bamaga2025abriefreview pages 2-4)
Cell types (CL suggestions). - Myelinating Schwann cell (CL:0002573) - Peripheral nervous system neuron / motor neuron (CL:0000740 broadly; more specific motor neuron CL terms may be used depending on KB conventions) - Macrophage (CL:0000235) as a candidate immune effector cell type in inflammatory components (supported indirectly via inflammatory pathway discussion). (bamaga2025abriefreview pages 2-4)
GO biological process suggestions. - Myelination (GO:0042552) - Axon ensheathment (GO:0008366) - Response to endoplasmic reticulum stress (GO:0034976) - Unfolded protein response (GO:0030968) - Protein aggregation (GO:0070841) - Apoptotic process (GO:0006915)
GO cellular component suggestions. - Myelin sheath (GO:0043209) - Endoplasmic reticulum (GO:0005783) - Lysosome (GO:0005764)
Molecular profiling / biomarkers. A 2023 review emphasizes the need for sensitive endpoints and notes candidate biomarkers such as muscle MRI and plasma neurofilament light chain. (okamoto2023thecurrentstate pages 12-14)
7. Anatomical Structures Affected
Primary system. Peripheral nervous system and peripheral nerves (UBERON:0000010). (dong2024currenttreatmentmethods pages 1-2)
Tissue/cell level. Peripheral nerve myelin (Schwann cells; myelin sheath). (jacob2023mechanismsandtreatment pages 1-2)
Distal musculoskeletal manifestations. Foot deformities (pes cavus/hammer toes) and hand deformities (clawing) reflect chronic denervation and imbalance. Visual depiction available. (dong2024currenttreatmentmethods media 041cb15e)
8. Temporal Development
Onset. Commonly described as beginning in the first to third decade, though pediatric onset occurs. (estevezarias2022geneticapproachesand pages 1-3)
Course. Chronic, slowly progressive length‑dependent neuropathy. (estevezarias2022geneticapproachesand pages 1-3, okamoto2023thecurrentstate pages 1-2)
9. Inheritance and Population
Prevalence. A 2024 Brain paper states CMT prevalence is estimated 1 in 2,500 to 1 in 10,000. (record2024wholegenomesequencing pages 1-2)
Genetic distribution (CMT1). In a large specialist cohort (n=1515), CMT1 comprised 41.0% (621/1515) and had a very high molecular diagnostic rate (96.8%). PMP22 duplication accounted for 505 cases and dominated CMT1 genetic architecture. (record2024wholegenomesequencing pages 3-5)
Sex ratio and demographics. Not systematically extracted for CMT1 specifically in the retrieved sources.
10. Diagnostics
Electrophysiology. Demyelinating vs axonal classification relies on upper-limb MNCV thresholds; different sources use different cutoffs (e.g., <38 m/s vs <25 m/s for “CMT1” depending on context). This should be represented as multiple rule sets with provenance. (okamoto2023thecurrentstate pages 1-2, record2024wholegenomesequencing pages 2-3)
Genetic testing strategy (evidence-backed). - First line (CMT1 phenotype): test for PMP22 duplication using MLPA; a large diagnostic cohort explicitly states “MLPA remains the preferred test for CMT1A.” (record2024wholegenomesequencing pages 2-3) - Second line: gene panels / WES / WGS as costs fell and for non-PMP22 cases; interpretation complexity includes VUS per ACMG/AMP. (estevezarias2022geneticapproachesand pages 3-5)
Real-world diagnostic yield (WGS and overall). In the UK specialist cohort (2009–2023), overall genetic diagnosis was 76.9%, and CMT1 had 96.8% diagnostic success. WGS increased the overall diagnostic rate with a reported 3.5% uplift; in a UK 100,000 Genomes subset, “true” WGS diagnostic rate was 19.7% (46/233) after removing diagnoses made otherwise. (record2024wholegenomesequencing pages 1-2)
Differential diagnosis. Not comprehensively retrieved; however, clinical distinction from acquired inflammatory neuropathies is discussed as potentially complicated by inflammatory components in some hereditary cases. (bamaga2025abriefreview pages 2-4)
11. Outcome/Prognosis
Disability and functional endpoints. Slow progression complicates trial sensitivity; a 2024 validation study established the CMT-Functional Outcome Measure (CMT-FOM) as a disease-specific functional COA for adults with CMT1A. (mandarakas2024multicentervalidationof pages 1-2)
Validated outcome measure (CMT-FOM). Multicenter validation included 214 adults (18–75 years) with CMT1A and supported a 12-item unidimensional 0–100 scale; it correlated with CMT Examination Score (r=0.643) and ONLS (r=0.516), and discriminated patient-reported problems such as daily trips/falls and hand weakness. (mandarakas2024multicentervalidationof pages 1-2)
Quality of life–adjacent outcomes. Sleep disturbance is common and associated with fatigue and anxiety/depression in a large registry-based questionnaire study. (cesaroni2025pmp22relatedneuropathiesa pages 12-13)
12. Treatment
Current standard of care (real-world implementation). Reviews emphasize that there is no established pharmacologic disease-modifying therapy, and management is multidisciplinary supportive care including rehabilitation, orthotics, and surgery for deformities. (estevezarias2022geneticapproachesand pages 3-5, dong2024currenttreatmentmethods pages 1-2)
Investigational pharmacotherapy: PXT3003 (baclofen + naltrexone + D-sorbitol). - PLEO-CMT (NCT02579759; Phase III, completed; n=323): primary endpoint ONLS (mean of months 12 and 15). A product quality/stability issue led to premature discontinuation of one dose arm; DSMC did not identify safety concerns. (NCT02579759 chunk 1) - PREMIER (NCT04762758; Phase III; planned ~350; active not recruiting per registry excerpt): primary outcomes include modified ONLS and 10‑meter walk test at month 15. (NCT04762758 chunk 1) - A separate Phase III PXT3003 study NCT05092841 is listed as completed with 176 participants in retrieved trial metadata (results not extracted in the available text chunks). (OpenTargets Search: Charcot-Marie-Tooth disease type 1,Charcot-Marie-Tooth disease type 1A,Charcot-Marie-Tooth disease type 1B)
Gene therapy / genome editing (recent developments). - iPSC Schwann cell genome editing: A 2023 Communications Medicine study used an AAV2‑SaCas9 strategy designed to excise the duplication junction; the abstract reports decreasing PMP22 gene duplication by ~20–40% in edited iPSCs and normalization of PMP22 expression with improved apoptosis/myelination phenotypes in patient‑derived Schwann cell models. (yoshioka2023aavmediatededitingof pages 13-14) - Neurotrophin‑3 (NT‑3) approaches: Reviews summarize evidence that NT‑3 delivery promotes nerve regeneration/myelination in CMT1A models and has been explored clinically; an scAAV1.tMCK.NT3 program reached a Phase I/IIa trial but was suspended due to vector manufacturing complications. (okamoto2023thecurrentstate pages 16-17, stavrou2023charcot–marie–toothneuropathiescurrentgene pages 9-10) - Targeting purinergic/inflammatory pathways: Gene-therapy review notes P2X7 receptor silencing/antagonism improving Schwann-cell co-culture properties and myelin-related protein expression in CMT1A models, suggesting immuno-metabolic pathways as adjunct targets. (stavrou2023charcot–marie–toothneuropathiescurrentgene pages 9-10)
MAXO (treatment ontology) suggestions (examples). - Physical therapy / rehabilitation therapy (MAXO term family for rehabilitation) - Orthotic device therapy (e.g., ankle-foot orthosis) - Surgical correction of foot deformity - Combination drug therapy (PXT3003) - Gene therapy / AAV-mediated gene therapy - Genome editing therapy (CRISPR-based)
13. Prevention
Primary prevention. Not applicable in the classical sense for Mendelian CMT1; prevention focuses on reproductive counseling.
Secondary/tertiary prevention. Early diagnosis enables specialist follow‑up, orthotics/rehabilitation, and management of complications (e.g., deformities, falls). (estevezarias2022geneticapproachesand pages 3-5)
Genetic counseling. Reviews emphasize genetic counseling as part of current management; preimplantation genetic diagnosis approaches for CMT1A are referenced (microsatellite-based segregation analysis) though detailed guidelines were not extracted in available chunks. (estevezarias2022geneticapproachesand pages 3-5)
14. Other Species / Natural Disease
Not addressed in retrieved texts.
15. Model Organisms
Rodent models (CMT1A). A mechanistic review lists commonly used PMP22-overexpression models (e.g., C22, C61, C3‑PMP) that recapitulate variable severities depending on PMP22 copy number. (jacob2023mechanismsandtreatment pages 1-2)
Human cellular models. Patient-derived iPSC Schwann cell models are used to study duplication correction and myelination phenotypes, supporting translational genome editing pipelines. (yoshioka2023aavmediatededitingof pages 13-14)
Recent developments (2023–2024) highlighted
- Clinical genomics implementation: WGS in routine pathways adds incremental diagnostic yield (3.5% uplift) but PMP22 CNV testing remains essential first-line for CMT1A. (record2024wholegenomesequencing pages 2-3, record2024wholegenomesequencing pages 1-2)
- Trial readiness improvements: CMT‑FOM validated as a robust functional endpoint for adult CMT1A trials (n=214). (mandarakas2024multicentervalidationof pages 1-2)
- Therapeutic pipeline maturation: Multiple Phase III PXT3003 trials have been conducted/are ongoing, with clearly defined functional endpoints (ONLS, walking tests) in registries. (NCT04762758 chunk 1, NCT02579759 chunk 1)
- Gene editing in human Schwann cells: AAV‑CRISPR editing of PMP22 duplication junctions demonstrated partial duplication reduction and phenotype rescue in patient-derived Schwann cells. (yoshioka2023aavmediatededitingof pages 13-14)
Key statistics (recent cohort and trials)
- CMT prevalence estimate: 1:2,500 to 1:10,000. (record2024wholegenomesequencing pages 1-2)
- Large specialist cohort (n=1515): overall molecular diagnosis 76.9%; CMT1 diagnosis 96.8%; PMP22dup 43.3% of solved cases and 82.3% of CMT1. (record2024wholegenomesequencing pages 3-5, record2024wholegenomesequencing pages 1-2)
- WGS: overall diagnostic uplift 3.5% in that cohort; “true” WGS diagnostic rate 19.7% (46/233) in 100KGP subset after adjustment. (record2024wholegenomesequencing pages 1-2)
- CMT-FOM validation cohort: 214 adults with CMT1A; correlation with CMTES r=0.643 and ONLS r=0.516. (mandarakas2024multicentervalidationof pages 1-2)
- PXT3003 Phase III: PLEO‑CMT n=323, ONLS primary endpoint; PREMIER planned ~350 with mONLS and 10mWT primary outcomes at month 15. (NCT04762758 chunk 1, NCT02579759 chunk 1)
Limitations and missing fields
- OMIM/Orphanet/ICD/MeSH identifiers were not present in retrieved tool context; they should be added via direct database queries (OMIM/Orphanet/WHO ICD/MeSH) in a subsequent pass.
- Population-specific variant frequencies, penetrance, founder effects, and protective factors were not available in the retrieved evidence.
- Published Phase III efficacy results for PXT3003 were not extracted from peer‑reviewed publications in the retrieved chunks; registry endpoints and notable trial events were extracted. (NCT02579759 chunk 1)
References
-
(okamoto2023thecurrentstate pages 1-2): Yuji Okamoto and Hiroshi Takashima. The current state of charcot–marie–tooth disease treatment. Genes, 14:1391, Jul 2023. URL: https://doi.org/10.3390/genes14071391, doi:10.3390/genes14071391. This article has 60 citations.
-
(dong2024currenttreatmentmethods pages 1-2): Hongxian Dong, Boquan Qin, Hui Zhang, Lei Lei, and Shizhou Wu. Current treatment methods for charcot–marie–tooth diseases. Biomolecules, 14:1138, Sep 2024. URL: https://doi.org/10.3390/biom14091138, doi:10.3390/biom14091138. This article has 12 citations.
-
(estevezarias2022geneticapproachesand pages 1-3): Berta Estévez-Arias, Laura Carrera-García, Andrés Nascimento, Lara Cantarero, Janet Hoenicka, and Francesc Palau. Genetic approaches and pathogenic pathways in the clinical management of charcot-marie-tooth disease. Journal of Translational Genetics and Genomics, 6:333-352, Jan 2022. URL: https://doi.org/10.20517/jtgg.2022.04, doi:10.20517/jtgg.2022.04. This article has 11 citations.
-
(record2024wholegenomesequencing pages 2-3): Christopher J Record, Menelaos Pipis, Mariola Skorupinska, Julian Blake, Roy Poh, James M Polke, Kelly Eggleton, Tina Nanji, Stephan Zuchner, Andrea Cortese, Henry Houlden, Alexander M Rossor, Matilde Laura, and Mary M Reilly. Whole genome sequencing increases the diagnostic rate in charcot-marie-tooth disease. Brain, 147:3144-3156, Mar 2024. URL: https://doi.org/10.1093/brain/awae064, doi:10.1093/brain/awae064. This article has 50 citations and is from a highest quality peer-reviewed journal.
-
(record2024wholegenomesequencing pages 1-2): Christopher J Record, Menelaos Pipis, Mariola Skorupinska, Julian Blake, Roy Poh, James M Polke, Kelly Eggleton, Tina Nanji, Stephan Zuchner, Andrea Cortese, Henry Houlden, Alexander M Rossor, Matilde Laura, and Mary M Reilly. Whole genome sequencing increases the diagnostic rate in charcot-marie-tooth disease. Brain, 147:3144-3156, Mar 2024. URL: https://doi.org/10.1093/brain/awae064, doi:10.1093/brain/awae064. This article has 50 citations and is from a highest quality peer-reviewed journal.
-
(estevezarias2022geneticapproachesand pages 3-5): Berta Estévez-Arias, Laura Carrera-García, Andrés Nascimento, Lara Cantarero, Janet Hoenicka, and Francesc Palau. Genetic approaches and pathogenic pathways in the clinical management of charcot-marie-tooth disease. Journal of Translational Genetics and Genomics, 6:333-352, Jan 2022. URL: https://doi.org/10.20517/jtgg.2022.04, doi:10.20517/jtgg.2022.04. This article has 11 citations.
-
(record2024wholegenomesequencing pages 3-5): Christopher J Record, Menelaos Pipis, Mariola Skorupinska, Julian Blake, Roy Poh, James M Polke, Kelly Eggleton, Tina Nanji, Stephan Zuchner, Andrea Cortese, Henry Houlden, Alexander M Rossor, Matilde Laura, and Mary M Reilly. Whole genome sequencing increases the diagnostic rate in charcot-marie-tooth disease. Brain, 147:3144-3156, Mar 2024. URL: https://doi.org/10.1093/brain/awae064, doi:10.1093/brain/awae064. This article has 50 citations and is from a highest quality peer-reviewed journal.
-
(dong2024currenttreatmentmethods pages 2-4): Hongxian Dong, Boquan Qin, Hui Zhang, Lei Lei, and Shizhou Wu. Current treatment methods for charcot–marie–tooth diseases. Biomolecules, 14:1138, Sep 2024. URL: https://doi.org/10.3390/biom14091138, doi:10.3390/biom14091138. This article has 12 citations.
-
(mandarakas2024multicentervalidationof pages 1-2): Melissa R. Mandarakas, Katy J. Eichinger, Paula Bray, Kayla M.D. Cornett, Michael E. Shy, Mary M. Reilly, Gita M. Ramdharry, Steven S. Scherer, Davide Pareyson, Timothy Estilow, Marnee J. McKay, David N. Herrmann, and Joshua Burns. Multicenter validation of the charcot-marie-tooth functional outcome measure. Neurology, Feb 2024. URL: https://doi.org/10.1212/wnl.0000000000207963, doi:10.1212/wnl.0000000000207963. This article has 12 citations and is from a highest quality peer-reviewed journal.
-
(NCT02579759 chunk 1): Phase III Trial Assessing the Efficacy and Safety of PXT3003 in CMT1A Patients (PLEO-CMT). Pharnext S.C.A.. 2015. ClinicalTrials.gov Identifier: NCT02579759
-
(NCT04762758 chunk 1): Phase III Trial Assessing the Efficacy and Safety of PXT3003 in CMT1A Patients. Pharnext S.C.A.. 2021. ClinicalTrials.gov Identifier: NCT04762758
-
(OpenTargets Search: Charcot-Marie-Tooth disease type 1,Charcot-Marie-Tooth disease type 1A,Charcot-Marie-Tooth disease type 1B): Open Targets Query (Charcot-Marie-Tooth disease type 1,Charcot-Marie-Tooth disease type 1A,Charcot-Marie-Tooth disease type 1B, 22 results). Buniello, A. et al. (2025). Open Targets Platform: facilitating therapeutic hypotheses building in drug discovery. Nucleic Acids Research.
-
(dong2024currenttreatmentmethods media 041cb15e): Hongxian Dong, Boquan Qin, Hui Zhang, Lei Lei, and Shizhou Wu. Current treatment methods for charcot–marie–tooth diseases. Biomolecules, 14:1138, Sep 2024. URL: https://doi.org/10.3390/biom14091138, doi:10.3390/biom14091138. This article has 12 citations.
-
(jacob2023mechanismsandtreatment pages 1-2): Claire Jacob and Nadège Hertzog. Mechanisms and treatment strategies of demyelinating and dysmyelinating charcot-marie-tooth disease. Neural Regeneration Research, 18:1931-1939, Jan 2023. URL: https://doi.org/10.4103/1673-5374.367834, doi:10.4103/1673-5374.367834. This article has 28 citations and is from a peer-reviewed journal.
-
(dong2024currenttreatmentmethods media 8b0c7523): Hongxian Dong, Boquan Qin, Hui Zhang, Lei Lei, and Shizhou Wu. Current treatment methods for charcot–marie–tooth diseases. Biomolecules, 14:1138, Sep 2024. URL: https://doi.org/10.3390/biom14091138, doi:10.3390/biom14091138. This article has 12 citations.
-
(cesaroni2025pmp22relatedneuropathiesa pages 12-13): Carlo Alberto Cesaroni, Laura Caiazza, Giulia Pisanò, Martina Gnazzo, Giulia Sigona, Susanna Rizzi, Agnese Pantani, Daniele Frattini, and Carlo Fusco. Pmp22-related neuropathies: a systematic review. Genes, 16(11):1279, Oct 2025. URL: https://doi.org/10.3390/genes16111279, doi:10.3390/genes16111279. This article has 5 citations.
-
(bamaga2025abriefreview pages 2-4): Ahmed K. Bamaga, Anas S. Alyazidi, and Feryal K. Alali. A brief review of inherited neuropathies: a perspective from saudi arabia. Brain Sciences, 15:403, Apr 2025. URL: https://doi.org/10.3390/brainsci15040403, doi:10.3390/brainsci15040403. This article has 2 citations.
-
(okamoto2023thecurrentstate pages 12-14): Yuji Okamoto and Hiroshi Takashima. The current state of charcot–marie–tooth disease treatment. Genes, 14:1391, Jul 2023. URL: https://doi.org/10.3390/genes14071391, doi:10.3390/genes14071391. This article has 60 citations.
-
(yoshioka2023aavmediatededitingof pages 13-14): Yuki Yoshioka, Juliana Bosso Taniguchi, Hidenori Homma, Takuya Tamura, Kyota Fujita, Maiko Inotsume, Kazuhiko Tagawa, Kazuharu Misawa, Naomichi Matsumoto, Masanori Nakagawa, Haruhisa Inoue, Hikari Tanaka, and Hitoshi Okazawa. Aav-mediated editing of pmp22 rescues charcot-marie-tooth disease type 1a features in patient-derived ips schwann cells. Communications Medicine, Nov 2023. URL: https://doi.org/10.1038/s43856-023-00400-y, doi:10.1038/s43856-023-00400-y. This article has 11 citations and is from a peer-reviewed journal.
-
(okamoto2023thecurrentstate pages 16-17): Yuji Okamoto and Hiroshi Takashima. The current state of charcot–marie–tooth disease treatment. Genes, 14:1391, Jul 2023. URL: https://doi.org/10.3390/genes14071391, doi:10.3390/genes14071391. This article has 60 citations.
-
(stavrou2023charcot–marie–toothneuropathiescurrentgene pages 9-10): Marina Stavrou, Alexia Kagiava, Irene Sargiannidou, Elena Georgiou, and Kleopas A. Kleopa.
charcot–marie–tooth neuropathies: current gene therapy advances and the route toward translation. Journal of the Peripheral Nervous System, 28:150-168, Apr 2023. URL: https://doi.org/10.1111/jns.12543, doi:10.1111/jns.12543. This article has 28 citations and is from a peer-reviewed journal.